Related Experiment Video
Updated: Oct 1, 2026
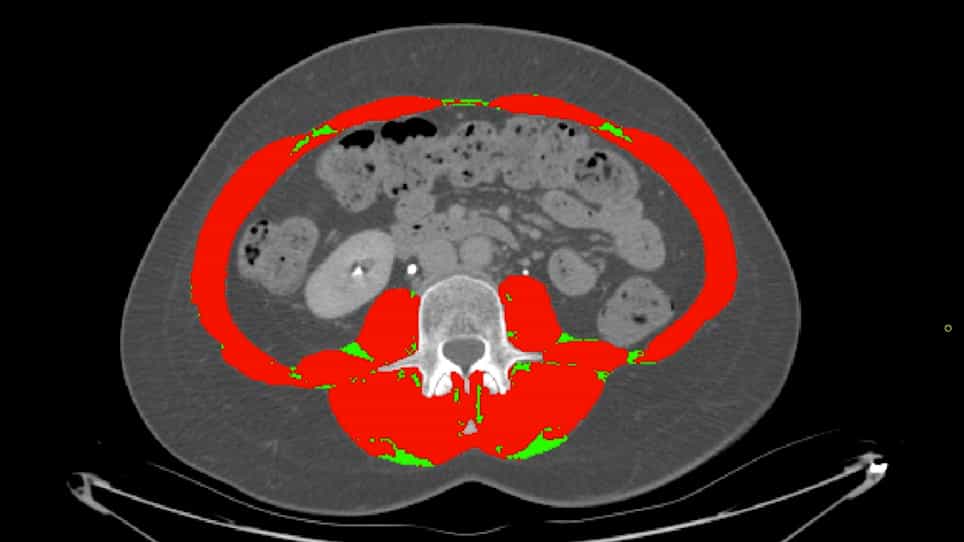

Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
Radiologic Sarcopenia and Charlson Comorbidity Index in the Head and Neck Free Flap Population
Alexandra Vacaru1, Roy W Qu2, Jacob Hauser1
1Loma Linda University School of Medicine Loma Linda California USA.

Objective:
Determining operative risk in patients undergoing head and neck free flap surgery has traditionally been difficult. Psoas muscle mass, a proven frailty marker in abdominal surgery, has not been evaluated in this population. This study demonstrates that radiologic sarcopenia and comorbidity burden may identify patients at higher risk for non-home discharge.
Methods:
A retrospective review was performed on 308 patients who underwent head and neck free flap surgery and had preoperative abdominal CT scans between 2014 and 2024. Inverse Psoas Muscle Index (PMI) and Charlson Comorbidity Index (CCI) were analyzed to assess the impact of radiologic sarcopenia and comorbidity on discharge disposition.
Results:
Higher inverse PMI had increased odds of discharge non-home (OR 1.37, 95% CI 1.05-1.77, p = 0.019). Non-home discharge varied across CCI groups (p < 0.05), occurring in 7.4% of patients with mild comorbidity, 39.5% with moderate comorbidity, and 55.7% with high comorbidity. Higher CCI increased odds of discharge non-home (OR 1.30, 95% CI 1.13-1.49, p < 0.001). Highest PMI quartile and mild comorbidity resulted in a 100% PPV for discharge home, corresponding to a 0% non-home discharge rate.
Conclusion:
Lower psoas muscle mass, reflected by higher inverse PMI, independently predicts non-home discharge, supporting its role as a frailty marker in head and neck free flap patients. Patients with higher comorbidity burden, as measured by CCI, have higher odds of non-home discharge. Combining radiologic muscle assessment (inverse PMI) with comorbidity indices demonstrates strong predictive potential for non-home discharge.