Related Experiment Video
Updated: Oct 1, 2026


A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
Adrenocortical Carcinoma with Suspected Dual Cortisol and Aldosterone Secretion: A Case Report
Ciara Fatima Jaime1, Florence Rochelle Gan1
1Section of Endocrinology, Diabetes and Metabolism, Department of Internal Medicine, Chinese General Hospital and Medical Center, Manila, Philippines.

Abstract:
Adrenocortical carcinoma (ACC) is a rare malignancy, accounting for 0.05-2% of all malignant tumors. Most cases are sporadic and asymptomatic, often discovered incidentally via imaging. However, 50-60% present with autonomous hormonal secretion, with 45% producing excess cortisol, and only 1% exhibiting mineralocorticoid excess. We report a 43-year-old Filipino female with a 6-month history of abdominal bloating, proximal muscle weakness, edema, and hypertension. Laboratory tests showed hypokalemia (serum potassium 2.5-3.05 mmol/L; normal 3.3-5.0 mmol/L). Imaging revealed a neoplastic right suprarenal mass (adrenal origin vs confluent lymphadenopathy) described as an incidental, lipid-poor right adrenal mass measuring 4.7 x 3.6 x 6.1 cm, with contrast-enhanced Hounsfield units of 40, along with periportal and paraaortic lymphadenopathies. Biochemical evaluation indicated an intermediate probability of primary aldosteronism: suppressed plasma renin at 0.97 ug/L/hr (0.97 ng/mL/hr), normal plasma aldosterone 599.46 pmol/L (21.61 ng/dl), and aldosterone-renin ratio of 618 (pmol/L)/(ng/L/hr) (22.27 ng/dl/ng/mL/hr). Ideally, confirmatory testing with an aldosterone suppression test prior to imaging and adrenal vein sampling (AVS) should be performed to lateralize the lesion before surgery; however, the patient opted to proceed with surgery. The patient also had overt hypercortisolism, with non-suppressed serum cortisol of 31.88 µg/dL (reference <1.8 µg/dL) on a low-dose dexamethasone suppression test, suppressed ACTH at 2.81 pg/mL (reference 7.7-63.6 pg/mL) (Table 1), and clinical features of Cushing syndrome, including facial plethora, and proximal muscle weakness. While these findings support the diagnosis of an ACTH-independent hypercortisolism, current guidelines recommend confirmatory testing, including 24-hour urinary free cortisol or late-night salivary cortisol, before definitive evaluation to distinguish ACTH-dependent from ACTH-independent disease. Concomitant catecholamine and androgen excess were excluded with normal 24-hour urine metanephrines and serum DHEAS. Surgical removal via open adrenalectomy was performed. Histopathology confirmed ACC, supported by immunohistochemistry. Postoperative treatment included radiotherapy and planned adjuvant mitotane therapy. During follow-up, the patient's blood glucose and blood pressure worsened, requiring medication adjustments. Unfortunately, the patient succumbed to the disease seven months post-surgery. This case highlights the difficulties in assessing adrenal tumors that concurrently secrete cortisol and aldosterone, especially when biochemical results are inconclusive, emphasizing the need for careful assessment and prompt intervention in this rare coexistence.

Related Concept Videos
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:19
Cushing Syndrome II: Pathophysiology
 01:26
Cushing Syndrome I: Introduction
 01:31
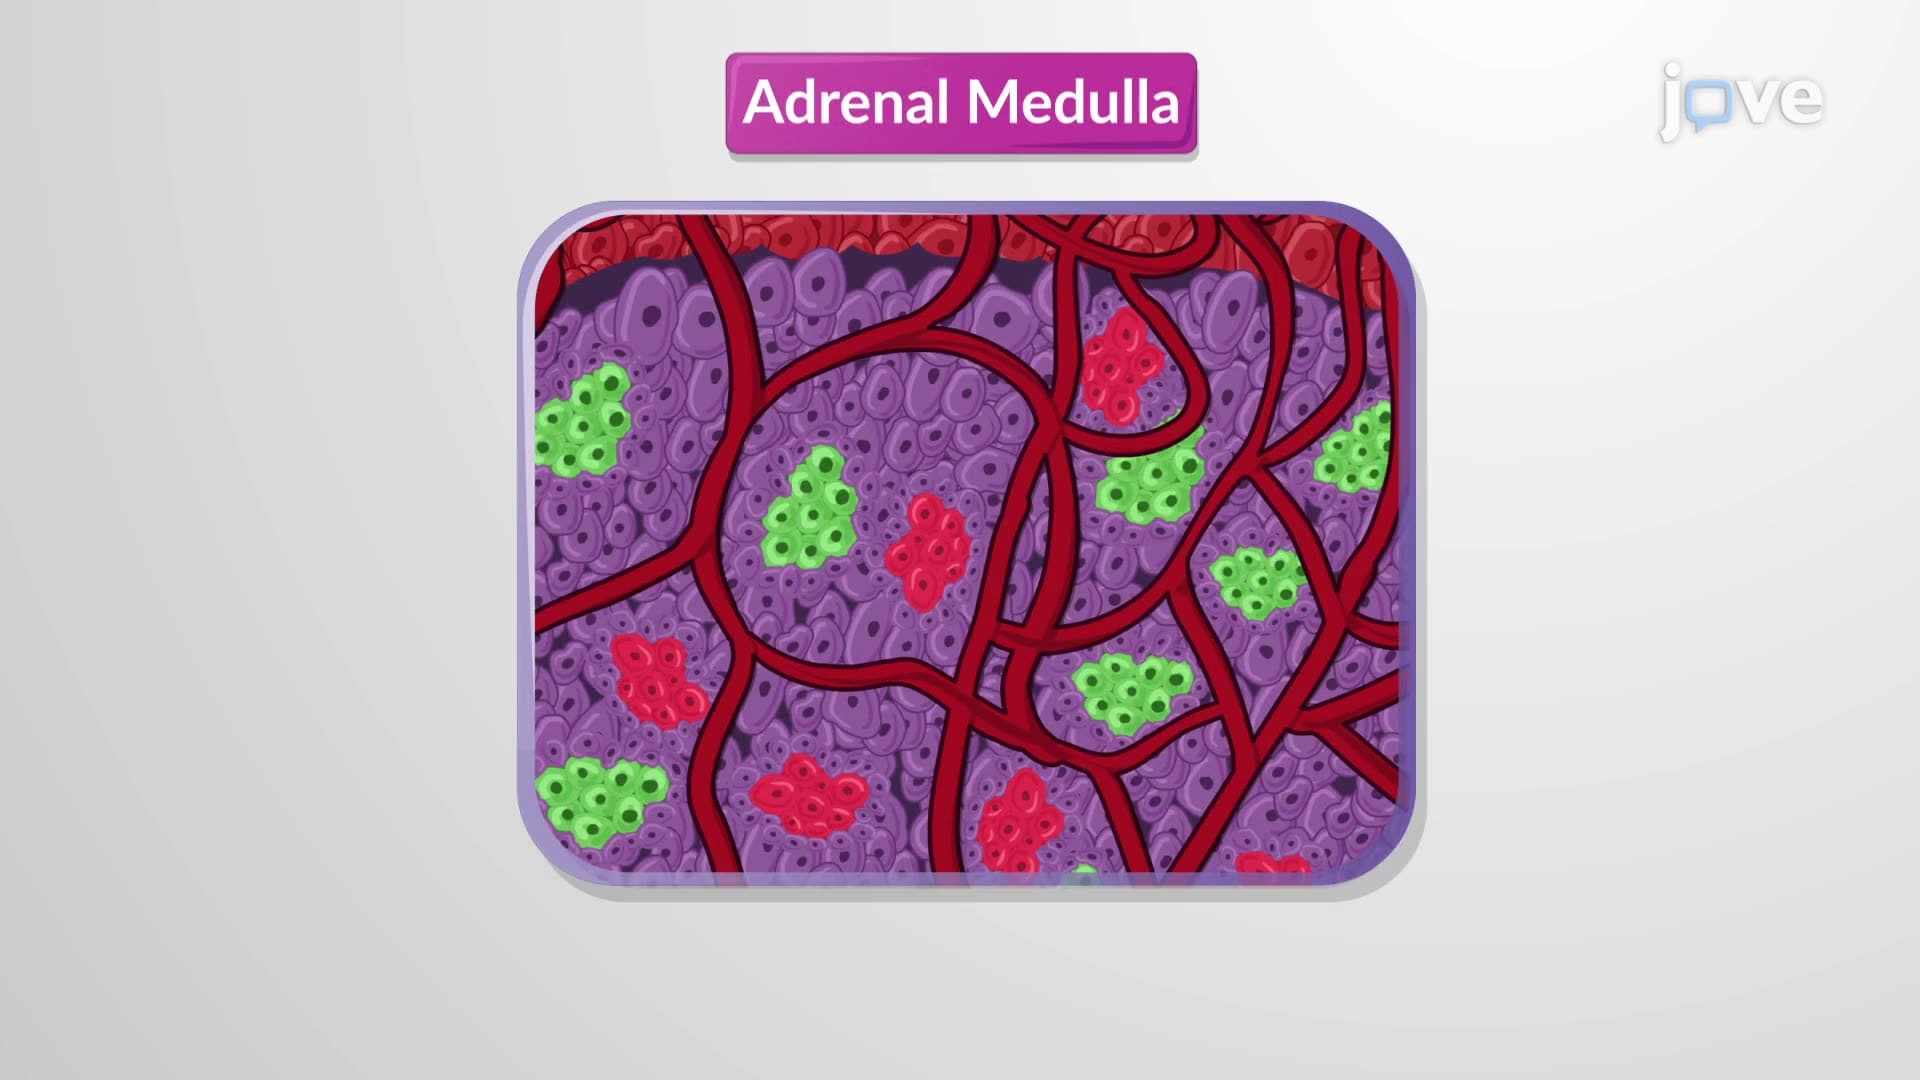
Hormones of the Adrenal Glands
The adrenal cortex, a powerhouse of hormone synthesis, generates over two dozen corticosteroid hormones. The zona glomerulosa produces mineralocorticoids, exemplified by aldosterone, influencing the electrolyte composition of body fluids. The synthesis of glucocorticoids such as cortisol and corticosterone...
 01:17
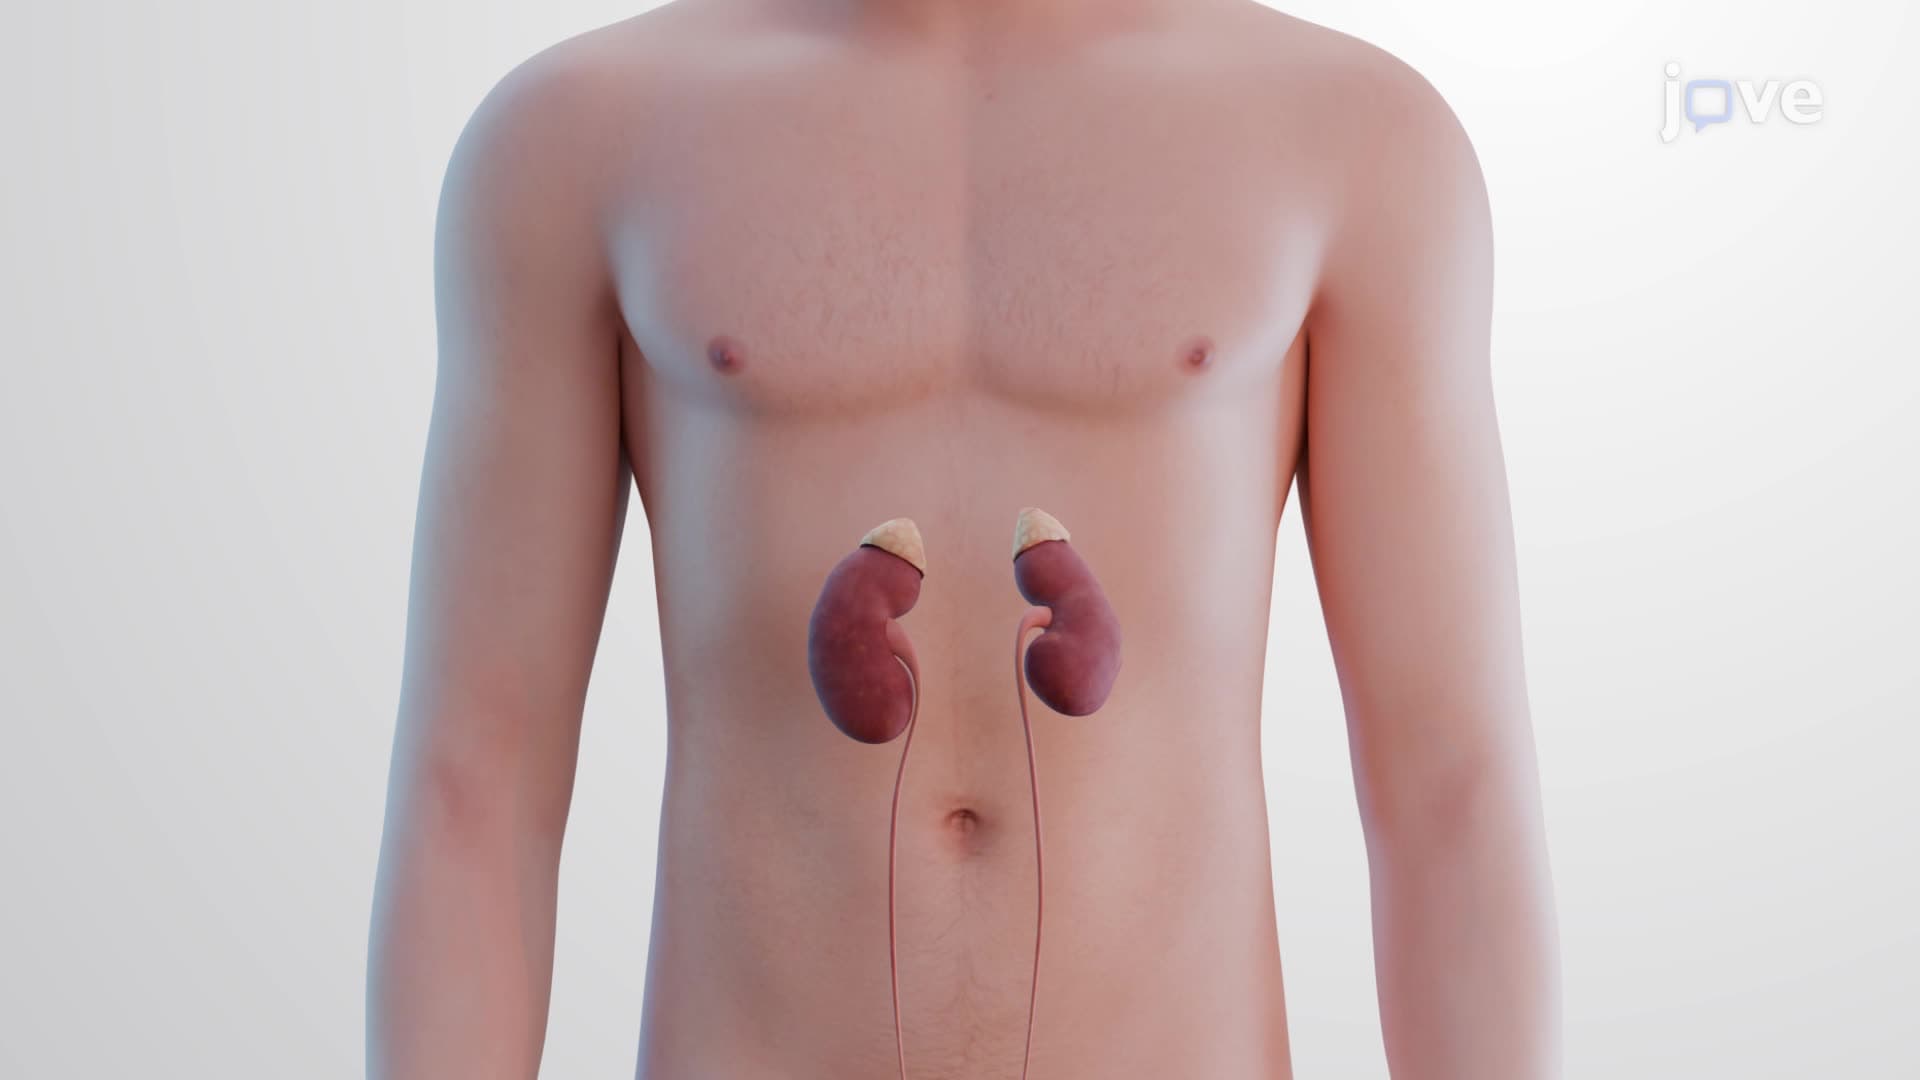
Anatomy of the Adrenal Glands
These glands possess a distinctive yellow tinge due to the stored cholesterol and fatty acids required for hormone synthesis. They are encased in a fibrous capsule and cushioned by fat.
The adrenal gland comprises two distinct regions...
 01:37
Hypothalamic-Pituitary Axis