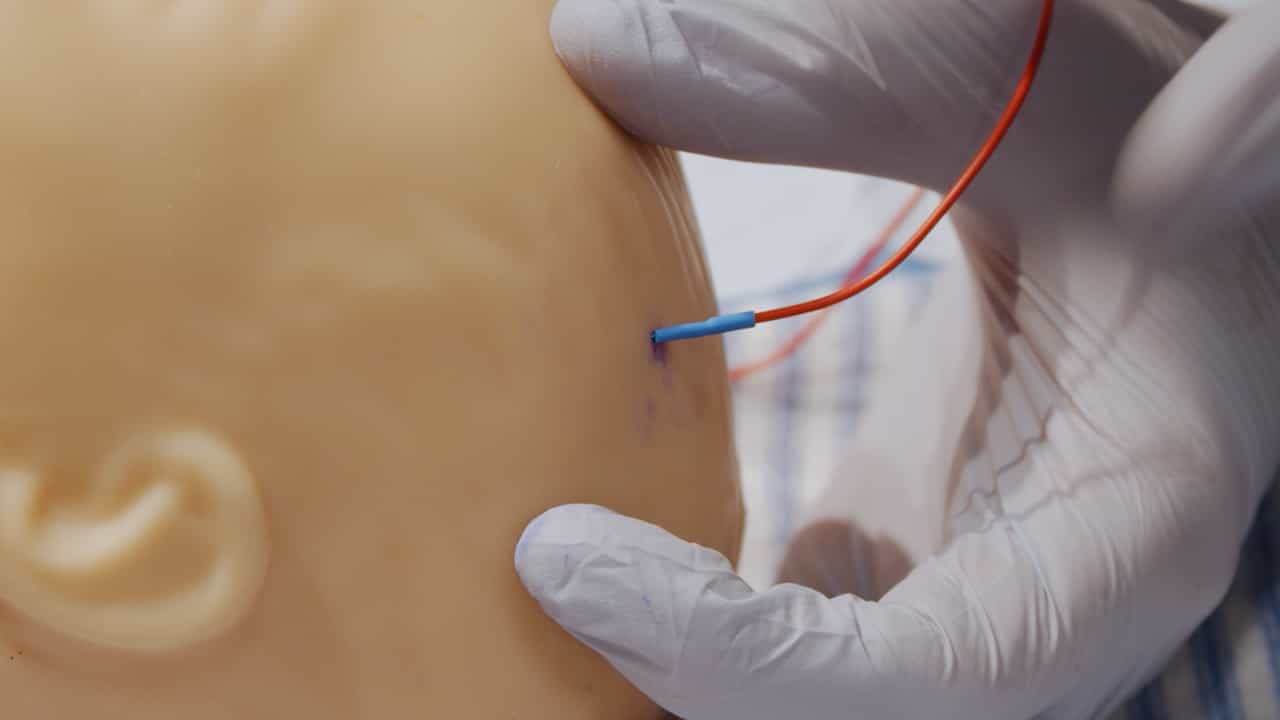

Current approaches and challenges in pediatric neuromuscular blockade monitoring: A scoping review
Nicky van der Leeden1, Steve Coppens2, Geertrui Dewinter2
1Department of Anesthesiology, University Hospitals Leuven, Herestraat 49, 3000 Leuven, Belgium.

Background:
Neuromuscular blocking agents (NMBAs) are a fundamental component of balanced anesthesia and are widely used in pediatric perioperative and intensive care settings. Despite their benefits, NMBA administration carries the risk of postoperative residual curarization (PORC), which may lead to respiratory complications, particularly in small infants. Developmental differences in physiology, pharmacokinetics, and pharmacodynamics further complicate NMBA management in this population, making accurate neuromuscular blockade monitoring (NMBM) essential to ensure efficacy and safety.
Methods:
A scoping review was conducted to evaluate NMBM in neonates, infants, and children younger than two years. A systematic search of seven electronic databases was performed covering publications from the past fifty years. Studies describing the usage of monitoring modalities, technical considerations, complications or limitations of monitoring in the pediatric population encompassing children under 2 years of age were eligible. Data were charted and synthesized following standard scoping review methodology.
Results:
After screening and selection according to predefined inclusion criteria, seventy-six studies were included in the final analysis. Earlier investigations predominantly relied on mechanomyography (MMG). In more recent years, there has been a shift towards the use of electromyography (EMG) and acceleromyography (AMG). Quantitative neuromuscular monitoring in neonates and small infants is best performed using pediatric-specific EMG devices or tri-axial AMG at the ulnar nerve. When available, nerve-mapping probes may facilitate accurate nerve localization and optimal electrode positioning.
Conclusion:
Reliable NMBM depends on adequate preparation, correct installation and appropriate calibration. Automatic determination of the supramaximal stimulating current is feasible with most devices but may need to be performed manually in small infants if automatic measurement fails. Train-of-Four ratio thresholds should be interpreted according to the patients' developmental characteristics. NMBM should continue until complete recovery has been objectively confirmed.
Related Concept Videos
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:17
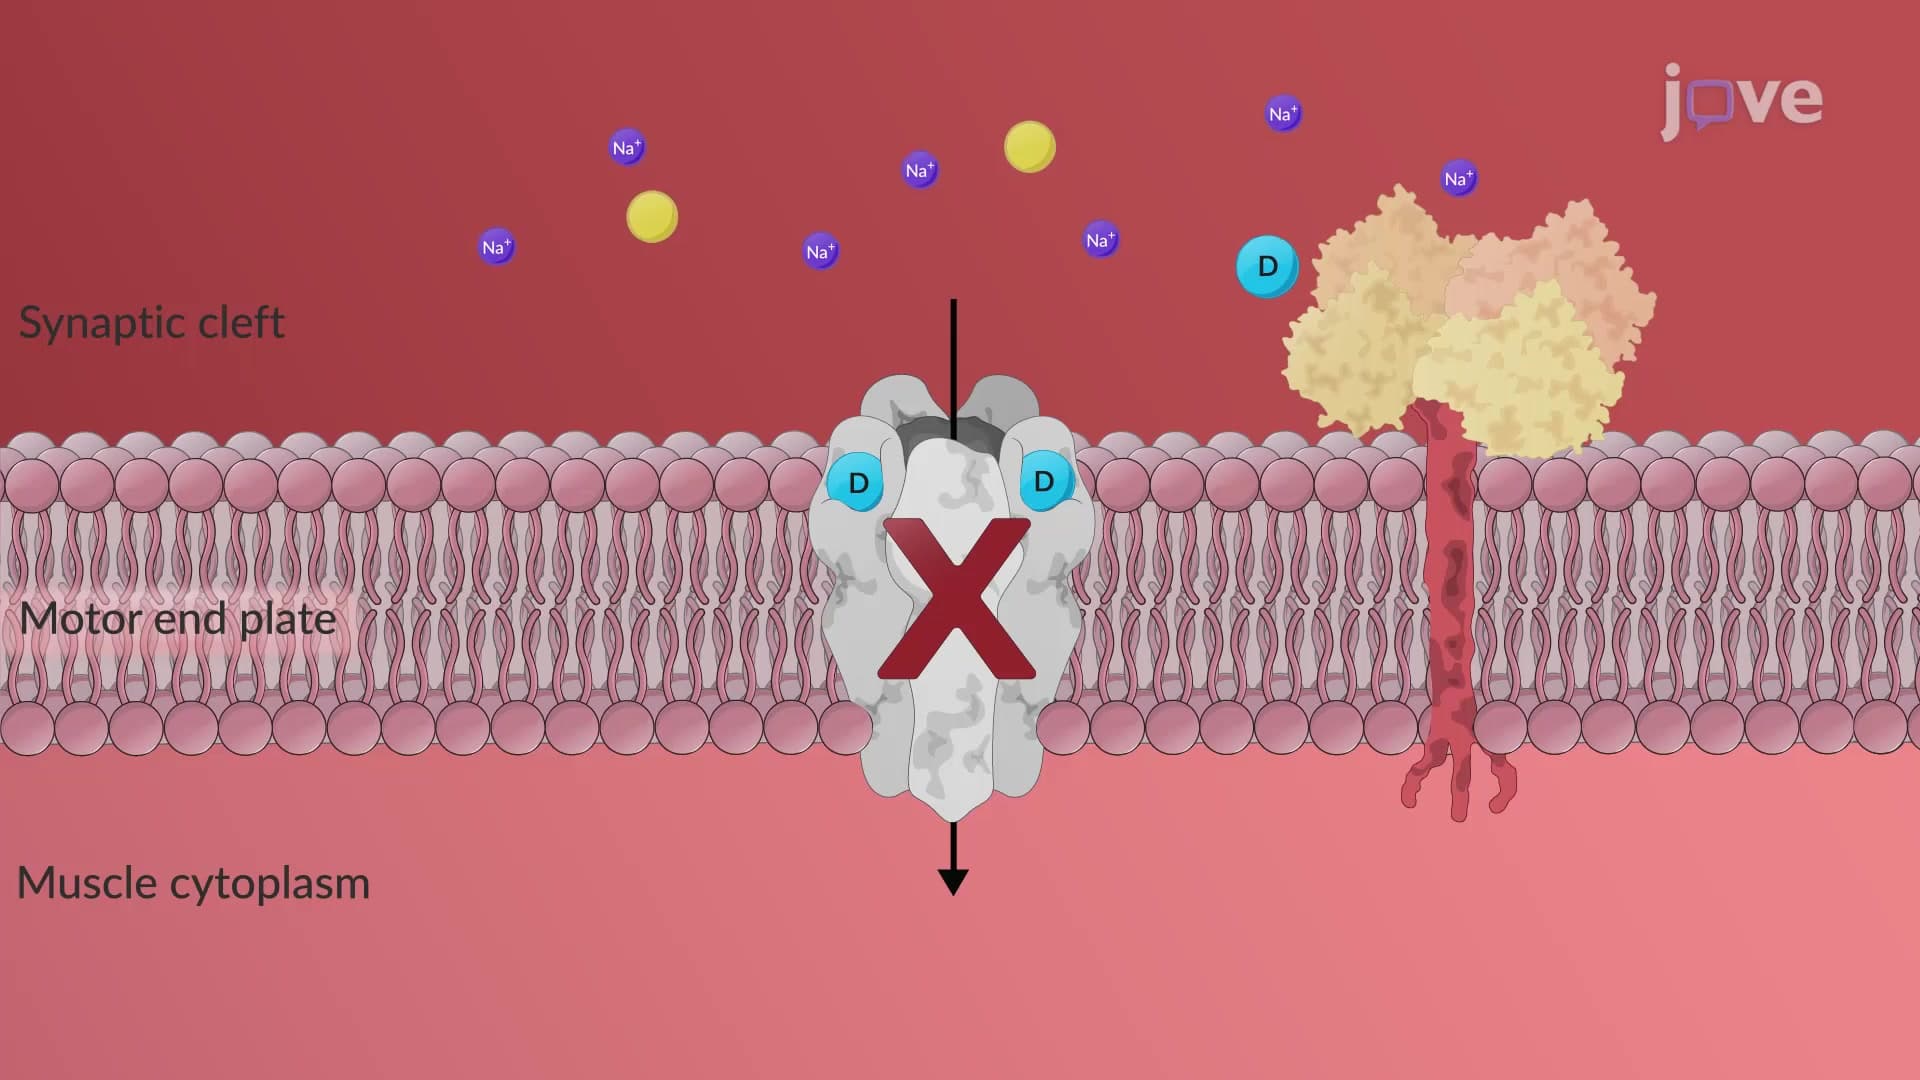
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:29
Neuromuscular Junction And Blockade
 01:19
Depolarizing Blockers: Pharmocokinetics