Related Experiment Video
Updated: Oct 2, 2026
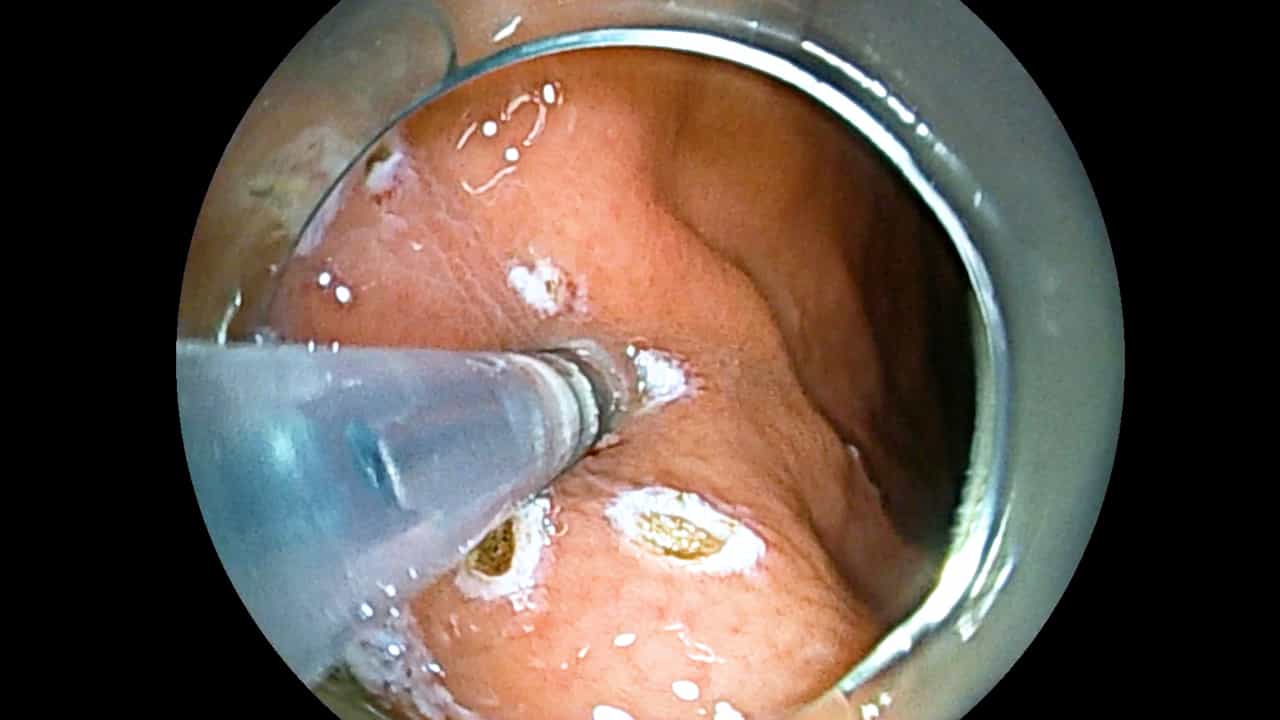

Evaluation of the Effectiveness of Longitudinal Incision for Endoscopic Submucosal Excavation of Gastric Subepithelial Lesions
Published on: April 28, 2026
Postgastric endoscopic submucosal dissection defect management: should we close, shield, or leave open?
Kanwal Bains1, Arjun Dhir2, Neil R Sharma3
1Banner University Medical Center Tucson, Tucson.

Purpose Of Review:
Postprocedural defect management following gastric endoscopic submucosal dissection (ESD) remains controversial. Asian practice has traditionally favored meticulous prophylactic hemostasis without routine closure, supported by routine post-ESD hospitalization, whereas Western centers increasingly use endoscopic suturing, closure, and shielding to prevent delayed bleeding, perforation, and hospitalization. This review evaluates contemporary evidence on defect closure and shielding, emphasizing risk stratification and evolving practice patterns.
Recent Findings:
Durable mechanical closure may reduce delayed bleeding in selected high-risk patients, particularly those receiving antithrombotic therapy or with elevated BEST-J scores. Emerging techniques, including the reopenable clip-over-the-line method (ROLM), endoscopic hand suturing (EHS), endoscopic suturing platforms, and dedicated closure devices, demonstrate high technical success and favorable safety. Evidence quality remains limited, comprising retrospective studies, propensity-matched cohorts, and a single underpowered randomized controlled trial, with substantial heterogeneity in closure technique, patient populations, lesion characteristics, and baseline bleeding risk. Meticulous vessel identification, coagulation, and selective clipping still achieve favorable outcomes in expert centers without routine closure. Shielding with polyglycolic acid (PGA) sheets, fibrin glue, and polymer-based barriers offers an intermediate option when durable closure is impractical.
Summary:
Current evidence does not support universal closure of all gastric ESD defects. Management should instead be selective, risk-stratified, and technique-conscious integrating bleeding risk, lesion characteristics, procedural setting, and local closure expertise. Low-risk defects may be safely managed with meticulous hemostasis alone, whereas durable closure appears most beneficial in carefully selected high-risk patients. Prospective comparative studies are needed to define which methods provide clinically meaningful, scalable benefit.

Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...