Related Experiment Video
Updated: Oct 2, 2026


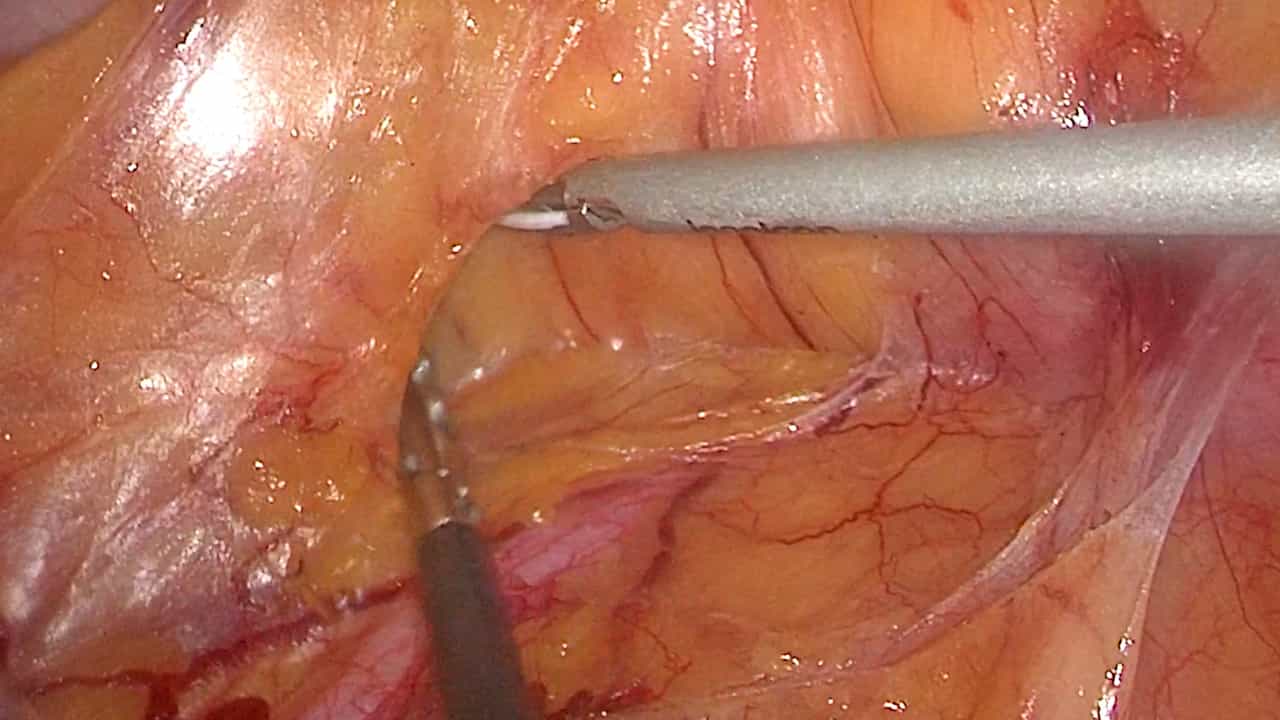
Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Local fat, local risk: mesorectal fat volume outperforms BMI in predicting rectal cancer surgery outcomes
Tingting Liu1, Liqiang Chang2, Junrui Zhao3
1Department of Colorectal Surgery, Tianjin Union Medical Center, The First Affiliated Hospital of Nankai University, Tianjin, China.

Background:
Accurate pre-operative assessment of surgical difficulty and post-operative risk in rectal cancer remains challenging. Conventional indices such as body mass index (BMI) fail to adequately reflect the pelvic surgical anatomy due to their systemic nature. Mesorectal fat volume-an imaging-derived, site-specific parameter-may better represent the operative field and associated risks, while also serving as a marker of regional adiposity relevant to nutritional and metabolic status.
Methods:
This single-center retrospective cohort study (2018-2026) analyzed 450 consecutive patients undergoing elective rectal cancer surgery with total mesorectal excision. Mesorectal fat volume was quantified using pre-operative computed tomography or magnetic resonance imaging with semi-automated segmentation. Patients were categorized into quartiles based on mesorectal fat volume. Operative outcomes and 30-day post-operative complications were compared across quartiles. Multivariable linear and logistic regression analyses were performed to identify independent predictors. Receiver operating characteristic (ROC) curve analysis was used to evaluate the discriminative performance of mesorectal fat volume, BMI, and pelvic index.
Results:
A total of 450 patients were stratified into quartiles according to mesorectal fat volume (MFV). Patients in the highest MFV quartile had significantly longer operative times (182.26 ± 9.28 vs. 163.03 ± 9.67 min, P < 0.001), greater intraoperative blood loss (169.63 ± 39.00 vs. 94.55 ± 40.08 mL, P < 0.001), higher conversion-to-open surgery rates (27.68% vs. 5.17%, P < 0.001), and higher 30-day post-operative complication rates (63.39% vs. 29.31%, P < 0.001) than those in the lowest MFV quartile. In multivariable analyses, MFV remained an independent predictor of post-operative complications (OR = 1.37, 95% CI: 1.21-1.55, P < 0.001), whereas BMI and pelvic index were not independently associated with complications. The multivariable prediction model demonstrated moderate discriminative ability (AUC = 0.683). Among the individual anthropometric measures, MFV demonstrated moderate discriminative ability (AUC = 0.655; 95% CI, 0.605-0.705), outperforming BMI (AUC = 0.552; 95% CI, 0.499-0.606) and pelvic index (AUC = 0.468; 95% CI, 0.415-0.522).
Conclusion:
CT-derived mesorectal fat volume is independently associated with increased operative difficulty and a higher risk of post-operative complications following total mesorectal excision. Compared with BMI and pelvic index, MFV provides better, although moderate, discrimination for predicting post-operative complications and may serve as a useful imaging biomarker for pre-operative risk stratification. Incorporation of MFV into multivariable prediction models may improve individualized surgical planning and perioperative risk assessment.