Related Experiment Video
Updated: Oct 3, 2026

Surgical Protocols for Deep Cervical Lymphovenous Anastomosis in a Rat Model: Lymph Node and Lymphatic Vessel Anastomoses
Published on: November 14, 2025
Complex venous access in superior vena cava syndrome secondary to gray zone lymphoma, case report
Martin Razus1,2,3, Maros Kunderlik4,5, Michal Marko3
1Institute of Medical Biology, Genetics and Clinical Genetics, Faculty of Medicine, Comenius University, Bratislava, Slovakia.

Introduction:
Mediastinal gray zone lymphoma (MGZL) is a rare and biologically complex lymphoma with overlapping features of primary mediastinal B-cell lymphoma and classical Hodgkin lymphoma. Bulky mediastinal disease frequently complicates central venous access, particularly in the presence of superior vena cava (SVC) syndrome. Reports addressing optimal vascular access strategies in this setting remain limited.
Case Presentation:
A 41-year-old man presented with newly diagnosed MGZL and a large mediastinal mass causing clinically significant SVC obstruction. The patient required urgent initiation of intensive systemic treatment; however, standard central venous access was contraindicated due to altered thoracic venous anatomy. A tunneled femoral catheter was therefore inserted to allow treatment initiation with rituximab plus dose-adjusted etoposide, doxorubicin, vincristine, cyclophosphamide, and prednisone (R-DA-EPOCH). The clinical course was complicated by catheter-related bloodstream infections caused by multidrug-resistant pathogens, septic shock, and pulmonary embolism, necessitating intensive care management. Following partial tumor response and anatomical decompression, duplex ultrasound-guided evaluation enabled successful implantation of a chest port via the left internal jugular vein, during which a duplicated superior vena cava was identified. Subsequent catheter-tip thrombosis was managed with low-molecular-weight heparin. Through coordinated multidisciplinary care, full-intensity R-DA-EPOCH was completed up to dose level 4, resulting in complete metabolic remission.
Conclusion:
This case highlights the critical importance of individualized venous access strategies in patients with mediastinal lymphoma complicated by SVC syndrome. Imaging-guided vascular assessment, multidisciplinary coordination, and adherence to international and national guidelines can enable safe delivery of curative-intent intensive chemotherapy, even in the setting of severe anatomical distortion and life-threatening complications. The case offers a visually documented, practical framework for managing venous access in complex anatomical conditions associated with superior vena cava syndrome.
Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:19
Veins of Head and Neck
On the other hand, the vertebral veins, unlike their arterial counterparts, are not primarily responsible for brain drainage. Instead, they drain the cervical vertebrae, spinal cord, and some small...
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management
 01:19
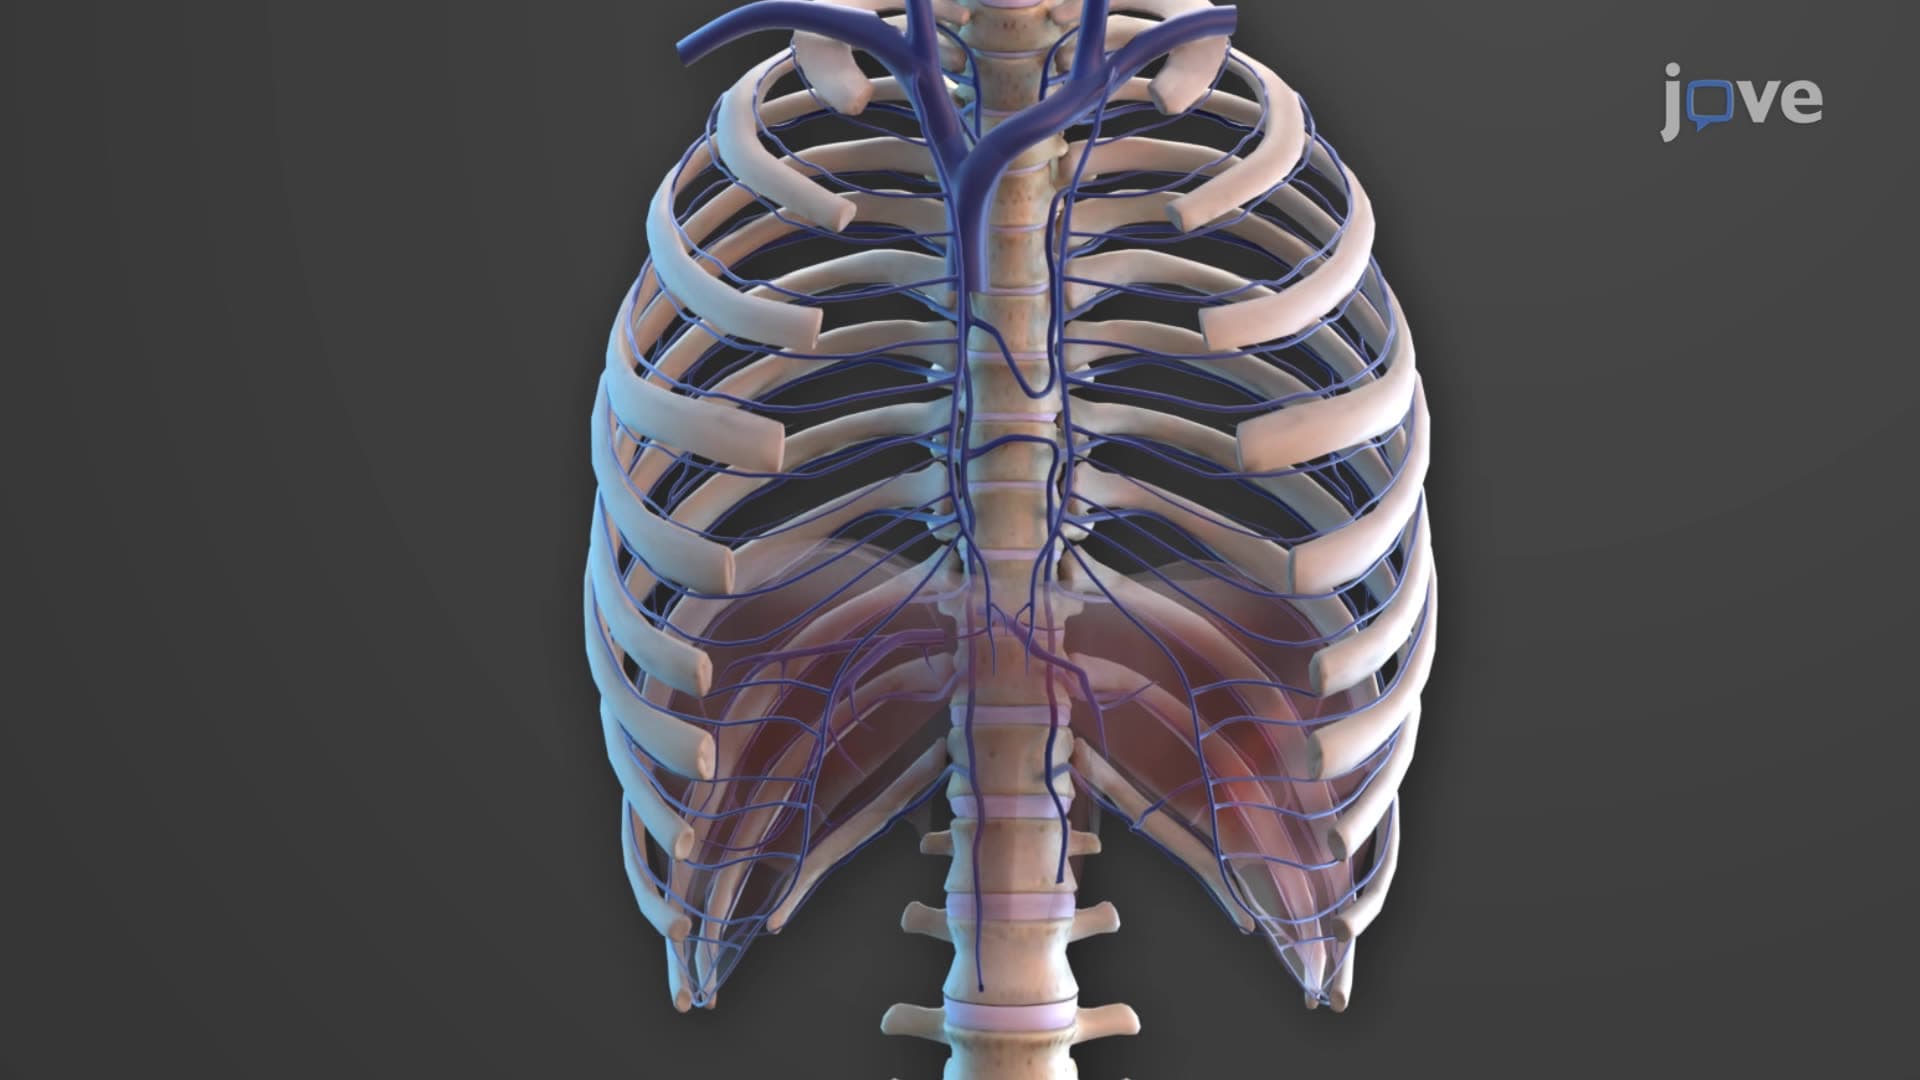
Veins of Thorax
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...