Related Experiment Video
Updated: Oct 3, 2026
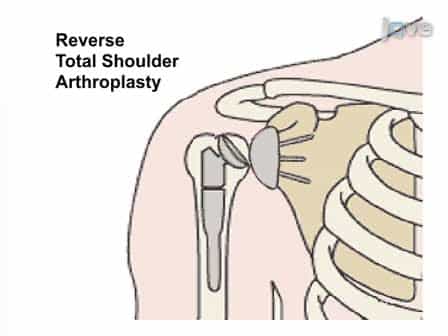

Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Midterm Observational Study Results After Glenohumeral Arthrodesis With a Locking Compression Plate in Paralytic
Jorge G Boretto1, Noelia Montenegro Puigdengolas1, Gerardo L Gallucci1
1Hand and Upper Extremity Surgery Unit, "Prof. Dr. Carlos Ottolenghi's Institute", Orthopaedic and Traumatology Department, Hospital Italiano de Buenos Aires, Buenos Aires, Argentina.

Purpose:
To evaluate bone union, hardware removal, complications, and functional outcomes after glenohumeral arthrodesis using a locking compression plate positioned beneath the acromion in patients with paralytic shoulder.
Methods:
A retrospective observational study was performed at a tertiary referral center. Patients who underwent glenohumeral arthrodesis with a locking compression plate between 2011 and 2025 were included. Demographic data, etiology of paralysis, prior treatments, complications, and need for secondary surgery were recorded. Radiographic union was assessed during follow-up. Postoperative active shoulder abduction and active flexion were measured, and hand-to-mouth ability was documented. Patient-reported outcomes were evaluated using the Quick Disabilities of the Arm, Shoulder, and Hand questionnaire. The association between scapulohumeral fusion angle and postoperative shoulder motion was analyzed.
Results:
Seventeen patients met the inclusion criteria, with a mean follow-up of 4.8 years. No patient required plate removal due to hardware intolerance. Glenohumeral fusion was achieved in all cases. One patient required early reoperation due to symptomatic screw prominence, and two patients sustained peri-implant humeral fractures, one of which required surgical fixation. Mean postoperative shoulder active range of motion was 56° in abduction and 58° in flexion. Twelve patients achieved hand-to-mouth. The mean Quick Disabilities of the Arm, Shoulder, and Hand score was 28. A significant positive correlation was found between the scapulohumeral fusion angle and postoperative active shoulder abduction and flexion.
Conclusions:
In this cohort, glenohumeral arthrodesis using a subacromial locking compression plate provided reliable bone union and a low complication rate. No patient required plate removal due to intolerance at the midterm follow-up. Scapulohumeral fusion angle was positively associated with postoperative active shoulder motion. This technique represents a useful option in selected patients with shoulder paralysis.
Type Of Study/Level Of Evidence:
Therapeutic IV.
