Related Experiment Video
Updated: Oct 3, 2026
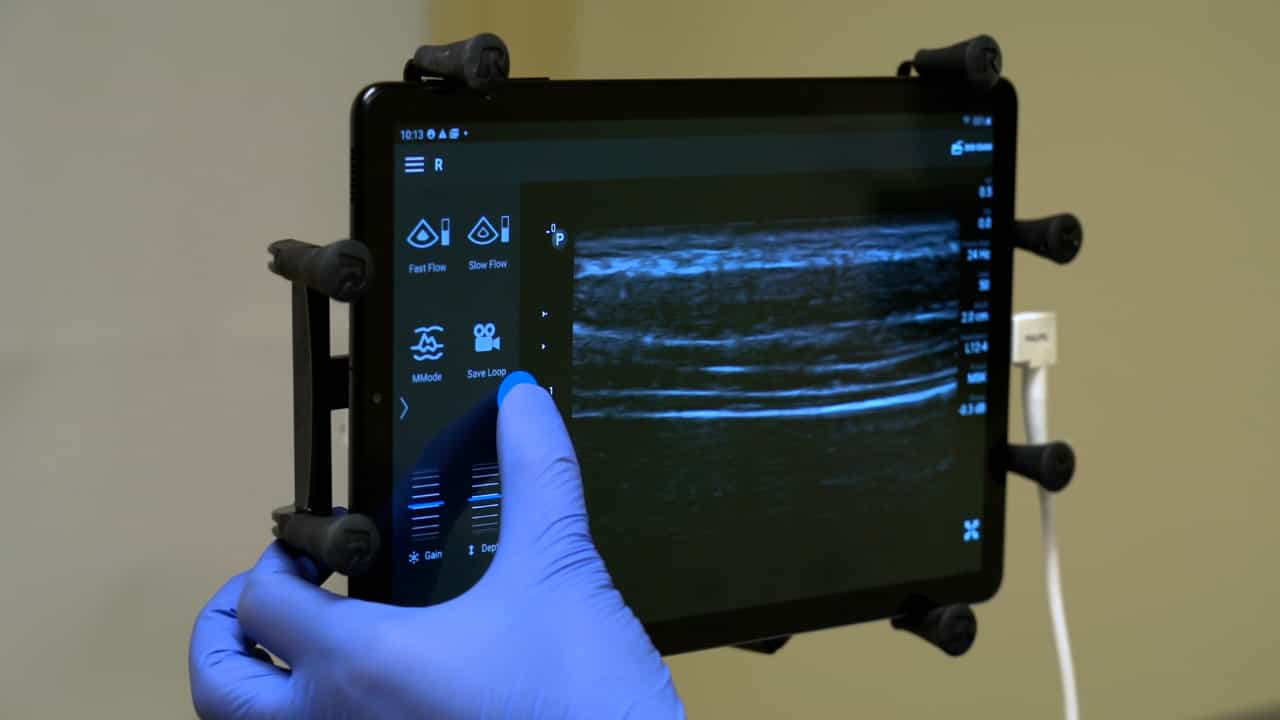

Measuring Diaphragm Thickness and Function Using Point-of-Care Ultrasound
Published on: November 3, 2023
Evolution of diaphragmatic thickness and function in preterm infants on non-invasive neurally adjusted ventilatory
Julie Lefevere1, Hanne Vermeulen2, Lissa De Potter3
1Neonatology, UZ Brussel, Laarbeeklaan 101, 1090, Jette, Belgium. Julie.lefevere@uzbrussel.be.

Abstract:
Non-invasive neurally Adjusted Ventilatory Assist (NIV-NAVA) is respiratory support that is synchronized with the Electrical activity of the Diaphragm (Edi) and uses the Edi to proportionally assist breathing by unloading the diaphragm. The aim of the study was to evaluate the effect of this diaphragm-triggered ventilation on the diaphragmatic structure and function. This observational cohort study aimed to track changes in diaphragm thickness (DT), measured with ultrasound, and function in preterm infants receiving NIV-NAVA. Diaphragmatic ultrasound was performed to determine diaphragm inspiratory (DTI) and expiratory thickness (DTE) and diaphragmatic thickening fraction (DTF) during and after NIV-NAVA. Lung ultrasound aeration score was assessed and Edi was recorded. Thirty-six preterm infants were included: 20 had primary and 16 post-extubation NIV-NAVA. Mean Gestational age at Birth and birth weight were 27.4 weeks and 1004 g. DTI remained stable during the study period, whereas DTE increased after stopping NIV-NAVA. Edi remained stable during and after NIV-NAVA. DTF was highly variable and did not change. Ultrasound-derived neuromechanical efficiency (= DTF/Edipeak) did not change over time on or after NIV-NAVA. LUS decreased gradually during the study period. No significant differences were found between infants on primary or post-extubation support except for DTF at inclusion.
Conclusion:
In preterm infants supported with NIV-NAVA, DT and diaphragm function remained stable during the study period, after stopping DT increased. No differences between primary and post-extubation NIV-NAVA were found.
What Is Known:
• The diaphragm is the main respiratory muscle and can be assessed reliably through diaphragmatic ultrasound in preterm infants. • Non-invasive neurally adjusted ventilatory assist (NIV-NAVA) relies on the function of the diaphragm for delivering synchronized and proportional respiratory support.
What Is New:
• Diaphragmatic thickness did not change during NIV-NAVA but increased after stopping. • Diaphragmatic function remained stable during and after NIV-NAVA.
Related Concept Videos
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:10
Atelectasis II: Pathophysiology
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...