Related Experiment Video
Updated: Oct 3, 2026
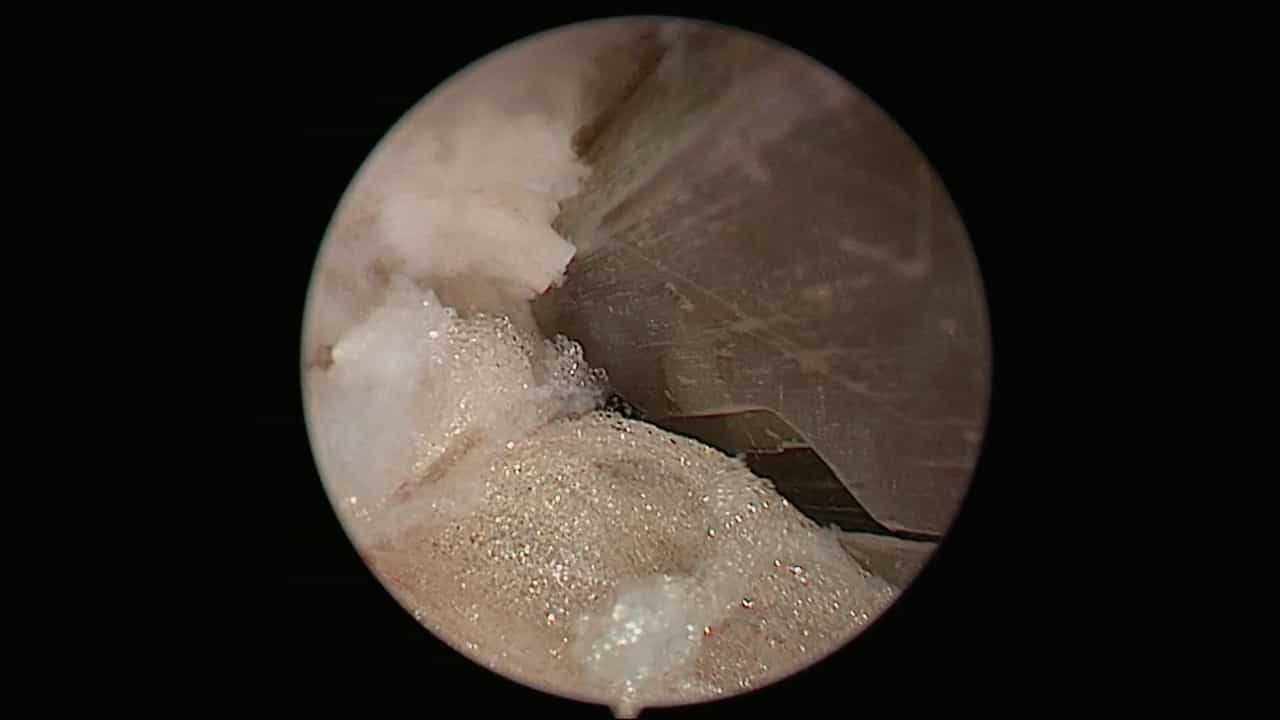

The Third Channel-Assisted Unilateral Biportal Endoscopic Technique for Lumbar Spinal Stenosis Combined with Contralateral Disc Herniation
Published on: November 17, 2023
Cost-effectiveness of full-endoscopic, unilateral biportal endoscopic, and microscopic decompression for single-level

Objective:
The aim of this study was to compare the clinical outcomes and healthcare costs of full-endoscopic decompression (FED), unilateral biportal endoscopic (UBE) decompression, and microscopic decompression (MD) for single-level lumbar spinal stenosis over a 2-year follow-up period.
Methods:
The authors retrospectively reviewed 395 patients (FED, n = 200; UBE, n = 93; MD, n = 102) who underwent single-level decompression between May 2020 and April 2022. Clinical outcomes were assessed using the visual analog scale (VAS) and Oswestry Disability Index (ODI). Economic evaluation included direct costs (surgery, hospitalization, and follow-up care) and indirect costs (productivity loss for both employed and unemployed patients) from a societal perspective. FED and UBE were additionally pooled as endoscopic decompression (ED) for incremental cost-effectiveness ratio (ICER) analysis. Cost-effectiveness was analyzed using quality-adjusted life years (QALYs) and the ICER.
Results:
Clinical improvements in VAS and ODI were comparable across the three groups at 2 years (p > 0.05). However, the MD group had a significantly longer hospital stay (mean 5.4 days) compared with the FED (mean 3.2 days) and UBE (mean 3.6 days, p < 0.001) groups. Total healthcare costs were significantly higher in the MD group (mean $6586) compared with the FED (mean $5502) and UBE (mean $5515, p < 0.001) groups. Indirect costs were also highest in the MD group due to delayed resumption of household activities and longer hospitalization (p = 0.012). Mean QALY gains were comparable among groups (FED, 0.197; UBE, 0.198; MD, 0.180; p > 0.05), whereas the mean cost per QALY was significantly higher in the MD group ($47,290) than in the FED ($39,060) and UBE ($34,822) groups (p = 0.04). The ICER for ED versus MD was -$60,510 per QALY, indicating that endoscopic techniques were more cost-effective.
Conclusions:
In single-level lumbar spinal stenosis, both FED and UBE decompression achieved clinical outcomes comparable with that of MD while demonstrating lower societal costs and more favorable cost-effectiveness profiles. The economic advantage of ED in this study was driven primarily by shorter hospitalization and earlier recovery.