Related Experiment Video
Updated: Oct 3, 2026
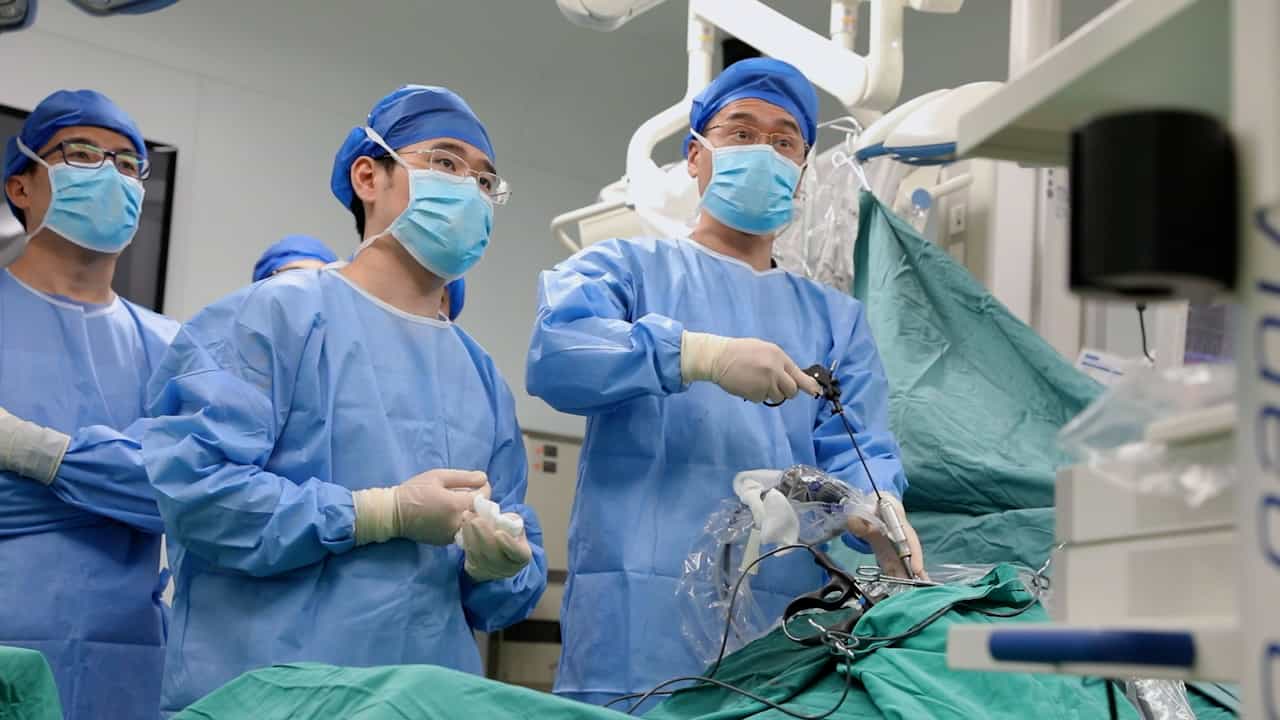

Percutaneous Endoscopic Unilateral-Approach Bilateral Decompression for Lumbar Spinal Stenosis
Published on: February 9, 2024
Revision status and patient-reported outcomes in thoracolumbar endoscopic spine surgery: a multicenter cohort study
Gregory Glauser1, Shaarada Srivatsa1, Arpan A Patel1,2
11Department of Neurosurgery, Neurological Institute, Cleveland Clinic, Cleveland.

Objective:
Endoscopic surgical approaches to degenerative spinal pathologies may revolutionize the landscape of minimally invasive spine surgery. Given the novelty of endoscopic approaches, there remains a paucity of large-scale data to examine the unique risk and complication profile of their application in revision surgery. Thus, the authors utilized a large dataset to compare the risk profile and outcome metrics of primary versus revision thoracolumbar endoscopic decompressions and discectomies.
Methods:
This study was a retrospective cohort analysis of a multi-institutional, prospectively enrolled registry managed by the Endoscopic Spine Research Group. Demographic, perioperative, and self-reported outcome data for patients undergoing endoscopic spinal procedures from March 1, 2021, to February 1, 2026, were collected. Comparisons between primary and revision cohorts were performed using t-tests or Mann-Whitney U-tests for continuous variables and chi-square tests or Fisher's exact tests for categorical variables. Multivariable models were generated to assess age, BMI, sex, smoking status, and baseline Oswestry Disability Index (ODI). Linear regression models were used for continuous outcomes, and logistic regression models were applied for binary outcomes. Statistical significance was set as p < 0.05.
Results:
In total, 1379 patients met the study inclusion criteria and had undergone 1138 primary procedures (82.5%) and 241 revision procedures (17.5%). Revision procedures consisted of a higher proportion of discectomies (85.9% vs 76.0%, p < 0.01) and lower proportion of decompressions (14.1% vs 24.0%, p < 0.01). Baseline demographic and clinical characteristics were otherwise comparable between primary and revision groups. The mean ODI and ODI improvement were similar between the primary and revision cohorts at all postoperative time points. The attainment of a minimal clinically important difference (MCID) in the ODI was similar between the primary and revision groups at each postoperative time point. On regression analysis, a higher preoperative ODI was a strong independent predictor of an MCID (OR 1.14, 95% CI 1.11-1.18, p < 0.01). Preoperative ODI, age, and BMI were all significant predictors of postoperative ODI (all p < 0.01). Revision status did not predict postoperative MCID or ODI improvement.
Conclusions:
The authors conducted a retrospective review of a large, multicenter cohort, demonstrating similar outcomes between primary and revision thoracolumbar endoscopic decompression and discectomies, as measured by the ODI and an MCID in the ODI.