Related Experiment Video
Updated: Oct 3, 2026


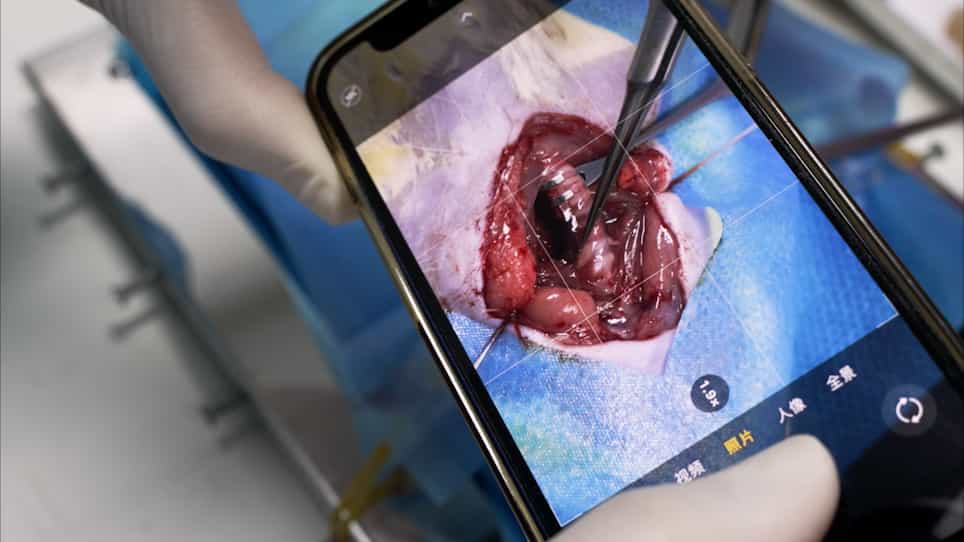
Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
Disease Burden, Surveillance, and Treatment Gaps in Chronic Hypoparathyroidism: Insights From a Multicenter Registry
Rodis D Paparodis1, Ioannis Androulakis2, Nikolaos G Angelopoulos2
1Endocrinology, Diabetes and Metabolism Clinics, Hellenic Endocrine Network, Greece; Department of Medicine, Edward Hines Jr VA Hospital, Hines, Illinois, USA; Division of Endocrinology, Diabetes and Metabolism, Loyola University Medical Center, Maywood, Illinois, USA.

Objective:
To evaluate disease and treatment burden, renal surveillance gaps, multidimensional biochemical control, hypercalciuria management, and parathyroid hormone (PTH) replacement therapy use in adults with chronic hypoparathyroidism.
Methods:
We conducted a multicenter retrospective cross-sectional registry study across 41 endocrinology clinics. Adults with chronic hypoparathyroidism (>12 months) were identified using ICD-10 codes, medication records, and manual chart verification. Multidimensional control required simultaneous achievement of albumin-corrected serum calcium, serum phosphate, and 24-hour urinary calcium targets. Secondary multivariable logistic regression analyses evaluated factors associated with suboptimal control, at least one applicable guideline-based care gap, and renal impairment.
Results:
Among 522 patients (83.1% women; median disease duration, 8 years), 496/522 (95.0%) had postsurgical disease. High-dose elemental calcium and alfacalcidol were required in 45/522 (8.6%) and 8/522 (1.5%), respectively. Among patients with at least 5 years of disease, 119/400 (29.8%) had never undergone 24-hour urinary calcium assessment and 101/400 (25.3%) had not undergone renal imaging. Multidimensional biochemical control was achieved in 126/230 patients (54.8%). Hypercalciuria was present in 72/282 patients (25.5%) at the latest assessment; 50/72 (69.4%) were not receiving calcium-sparing diuretic therapy. Among 239 patients eligible for PTH replacement therapy, 196/239 (82.0%) had not initiated treatment. Lower current age was associated with suboptimal control, longer disease duration and postsurgical etiology with at least one care gap, and older age with renal impairment.
Conclusion:
Assessment based solely on serum calcium may underestimate incomplete disease control. Multidimensional biochemical abnormalities, surveillance deficiencies, and therapeutic care gaps remain common despite specialist endocrine follow-up.
Related Concept Videos
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:27
Hyperthyroidism II: Pathophysiology
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:23
Hypothyroidism II: Pathophysiology
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment: