Related Experiment Video
Updated: Oct 3, 2026


Calcification of Vascular Smooth Muscle Cells and Imaging of Aortic Calcification and Inflammation
Published on: May 31, 2016
The effects of dialysate acids and divalent ions on calcification and cardiovascular outcomes: old wisdom and new
Jeroen P Kooman1,2, Karlien J Ter Meulen1,2, Peter Kotanko3,4
1Division of Nephrology, Department of Internal Medicine, Maastricht University Medical Center, Maastricht, the Netherlands.

Abstract:
Dialysate calcium (DCa) and magnesium (DMg) and the organic acid used in the acid concentrate have a profound combined influence on intradialytic mineral balance and may influence vascular calcification progression and treatment-related symptoms. Whereas Kidney Disease: Improving Global Outcomes recommends a DCa between 1.25 (DCa 1.25) and 1.50 mmol/l (DCa 1.50), the optimal DCa for an individual patient remains uncertain. No consistent mortality difference between DCa 1.50 and 1.25 has been observed. However, DCa 1.50 may induce a positive calcium balance, raising concerns about vascular calcification progression. Conversely, DCa below 1.25 mmol/l has been associated with a higher risk of sudden cardiac death. Compared with acetic acid (acetate dialysate, Acet-D), citric acid (citrate dialysate, Cit-D) reduces calcification propensity of serum, although the effect on vascular calcification progression is inconclusive. Whenever feasible, DCa should be individualized, ideally using estimates of calcium mass balance (CaMB). Because Cit-D generally results in a more negative CaMB than Acet-D solutions at the same nominal DCa, this difference should be considered when prescribing DCa. Increasing DMg from 0.50 to 0.75 mmol/l may improve surrogate cardiovascular outcomes although its effect on clinical outcomes remains to be defined. Overall, Acet-D with DCa 1.25 is a reasonable standard especially when using calcium-containing phosphate binders and in patients at risk for adynamic bone disease, whereas in patients with a high risk of sudden cardiac death, frequent intradialytic hypotension or with severe secondary hyperparathyroidism, DCa 1.50 may be a reasonable alternative. Regarding the choice of acid, the use of Cit-D represents a promising alternative pending further clinical evidence.


Related Concept Videos
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:27
Urinary Tract Calculi IV: Nutrition Therapy and Prevention
 01:21
Skeleton and Calcium Homeostasis
 01:29
Renal Regulation of Acid-Base Balance
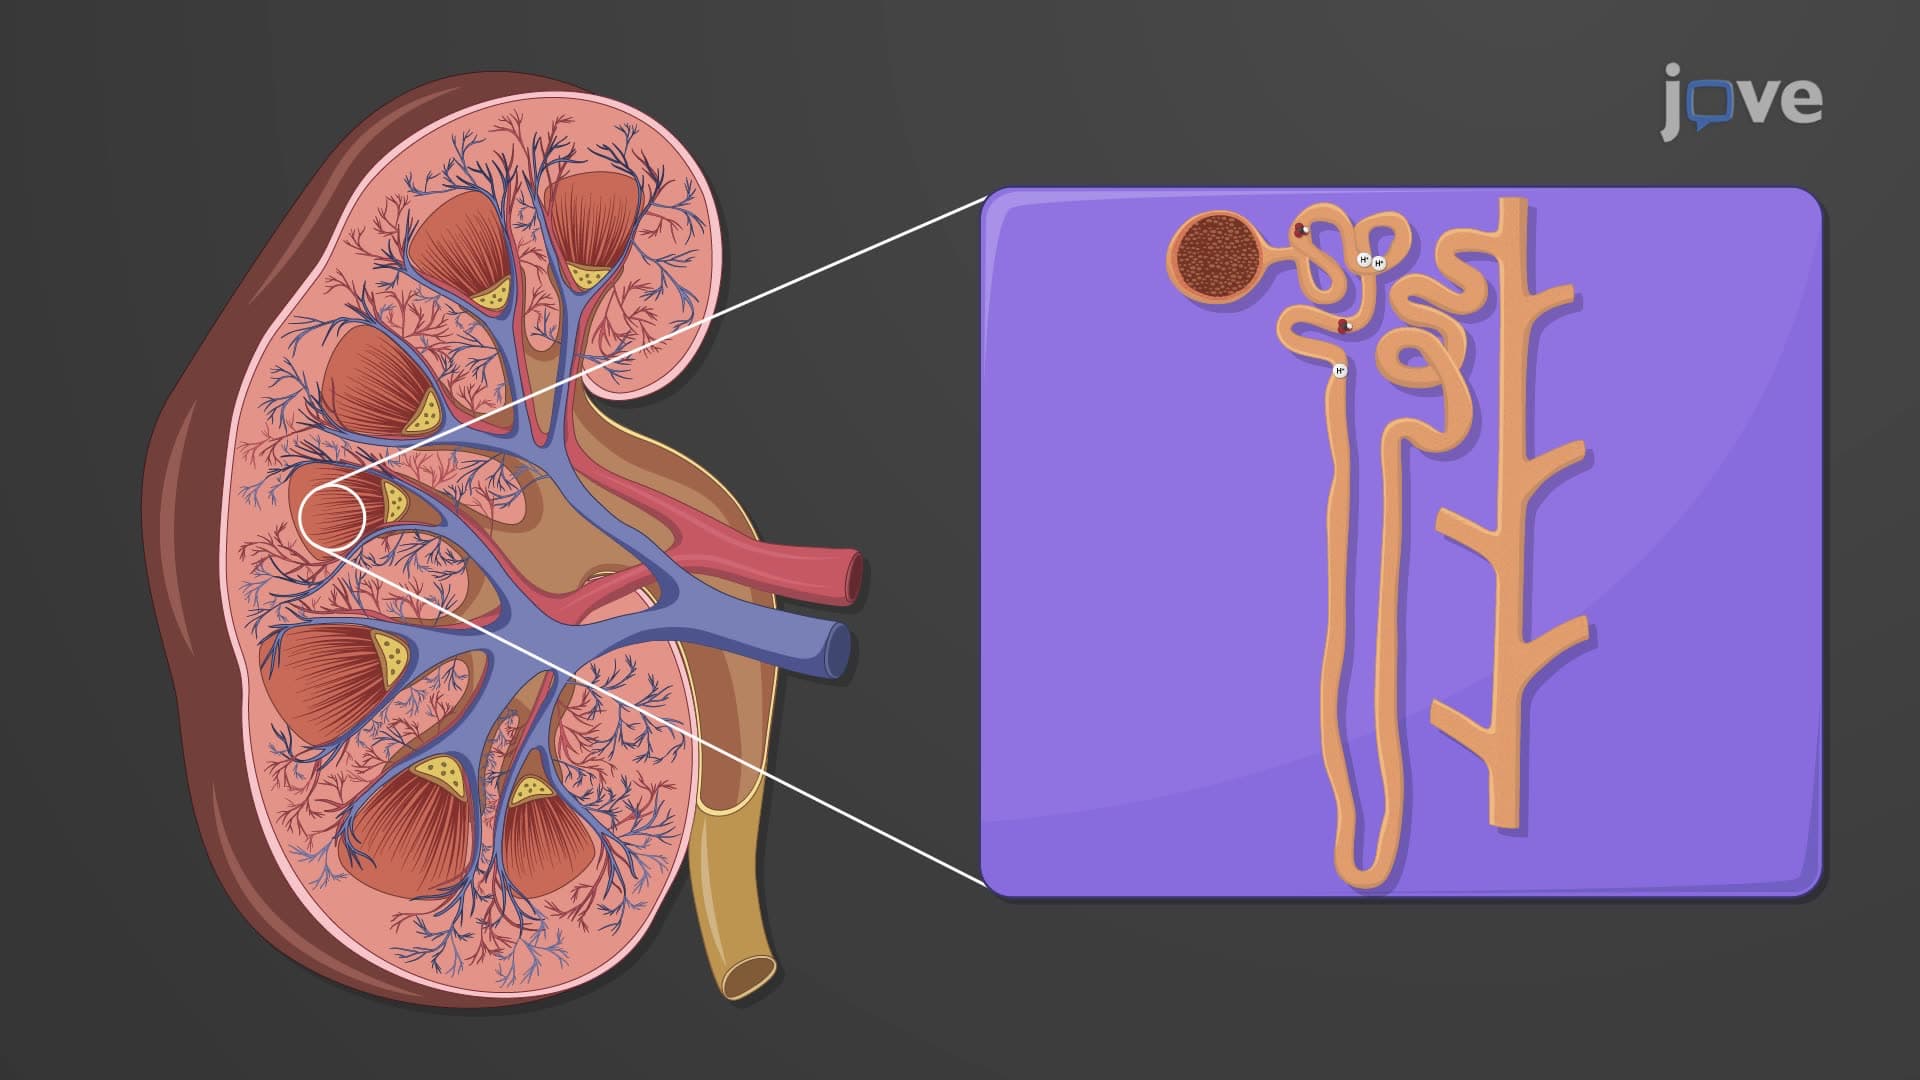
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:19
Ionic Strength: Effects on Chemical Equilibria
In this solution, the primary cation—the calcium...