Related Experiment Video
Updated: Oct 5, 2026
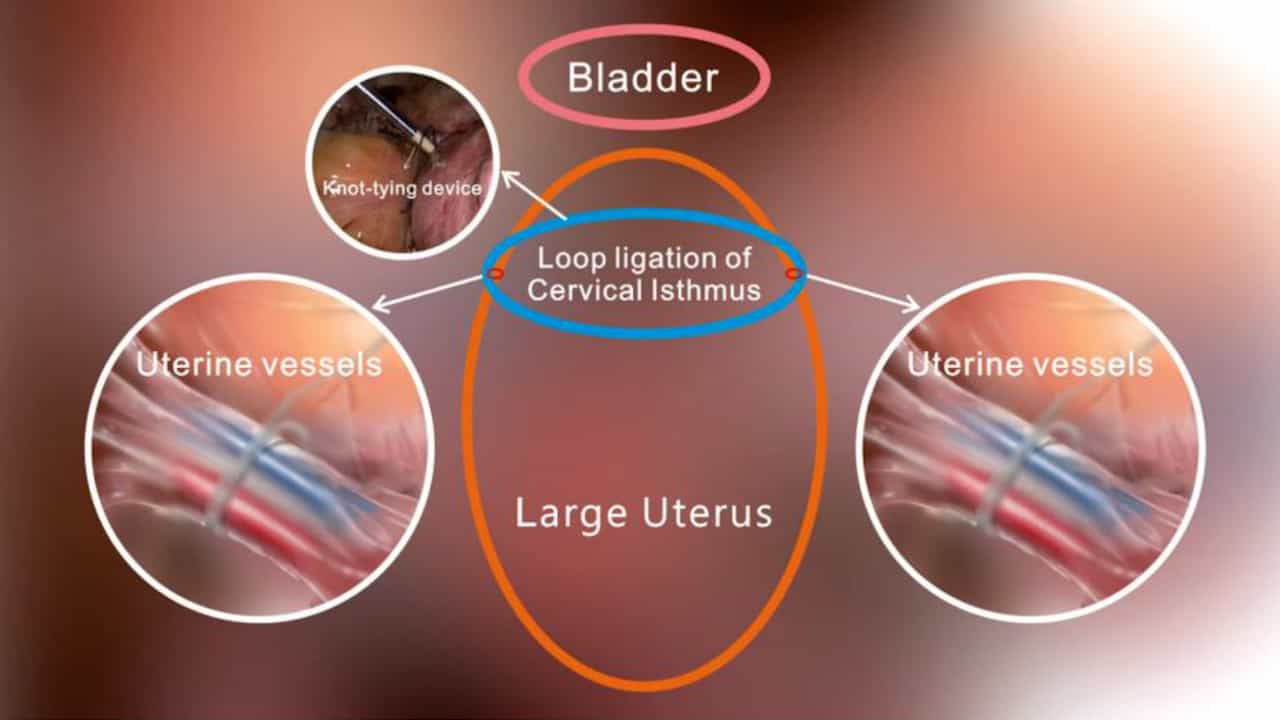

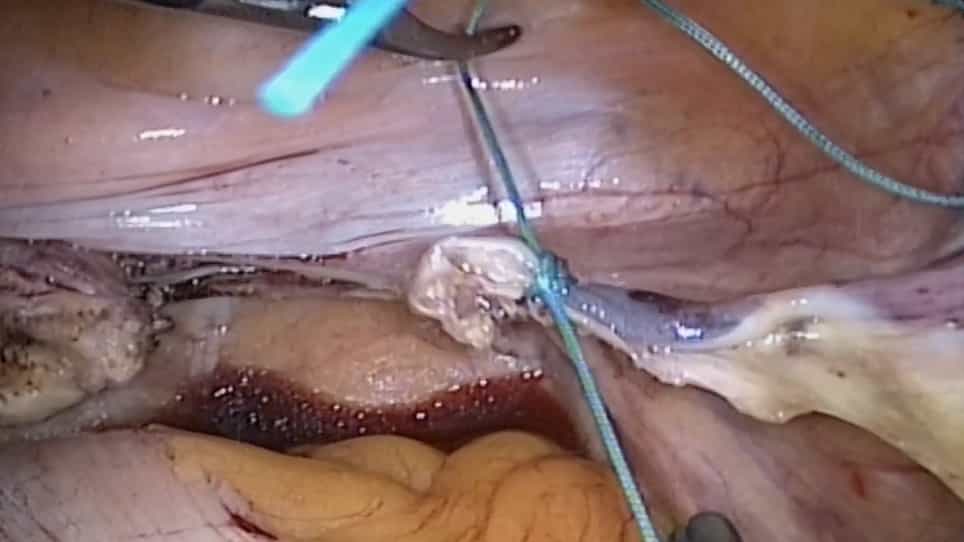
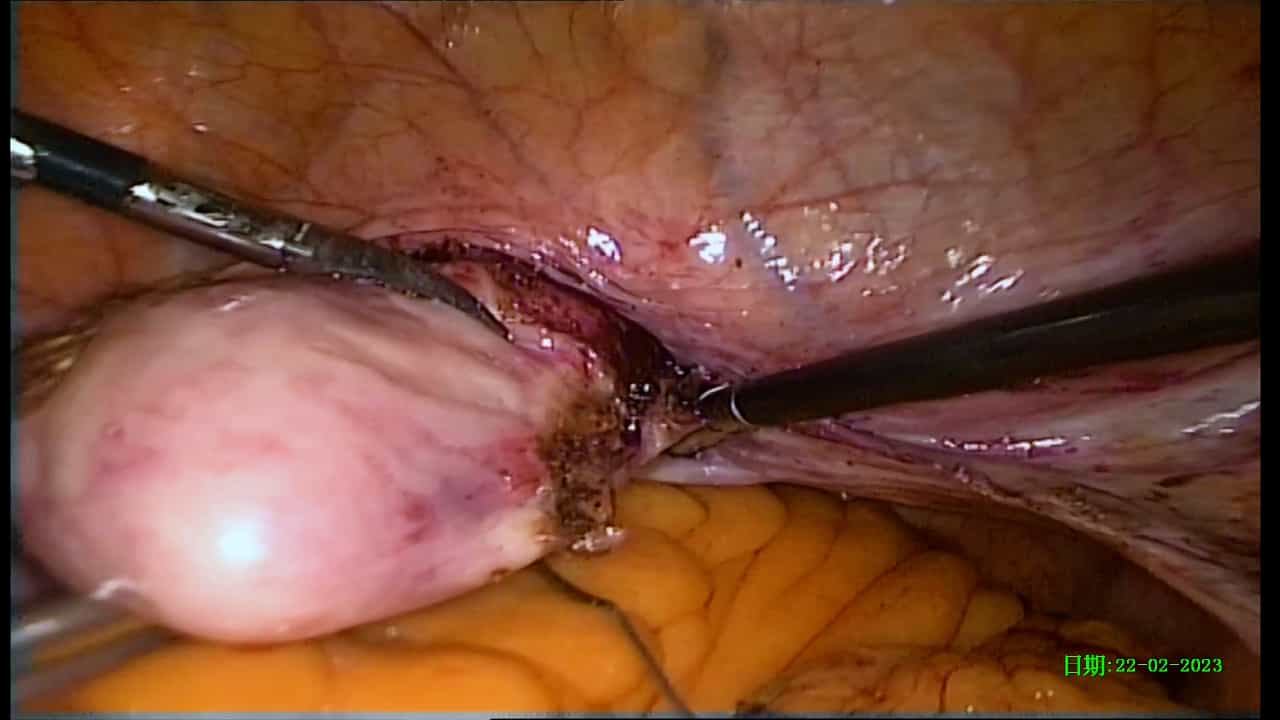
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Reinterpreting cervical cerclage classification: Diagnostic detection and operative context
Yong-Jin Park1, Moon-Il Park1,2
1Department of Obstetrics and Gynecology, Cervical Insufficiency Center, Dongtan Jeil Women's Hospital, Hwaseong, Republic of Korea.

Abstract:
Cervical cerclage is conventionally classified as history-indicated, ultrasound-indicated, or examination-indicated cerclage, the latter often performed as emergency cervical cerclage. These categories remain clinically useful because they describe common pathways of risk recognition, surveillance, intervention, and rescue. However, they are sometimes interpreted as biologically uniform or sequential stages of cervical insufficiency. This narrative review examines the historical and diagnostic basis of the conventional classification and focuses on its limitations for describing emergency cerclage. The three categories can also be understood as reflecting how and when cervical vulnerability becomes detectable: through antecedent obstetric history, sonographic cervical change, or physical examination findings. This interpretation does not diminish the importance of obstetric history or imply that ultrasound surveillance should delay preventive intervention. Rather, history and surveillance are complementary routes to timely recognition. In emergency cerclage, indication labels alone do not describe membrane exposure or prolapse, membrane reducibility, residual cervical tissue, procedural feasibility, or operative configuration. Therefore, we propose retaining the established indication-based classification while supplementing it with structured reporting of detection timing and operative context. This reporting approach might improve interpretation and comparability of emergency cerclage studies without replacing established clinical terminology.