Related Experiment Video
Updated: Oct 5, 2026
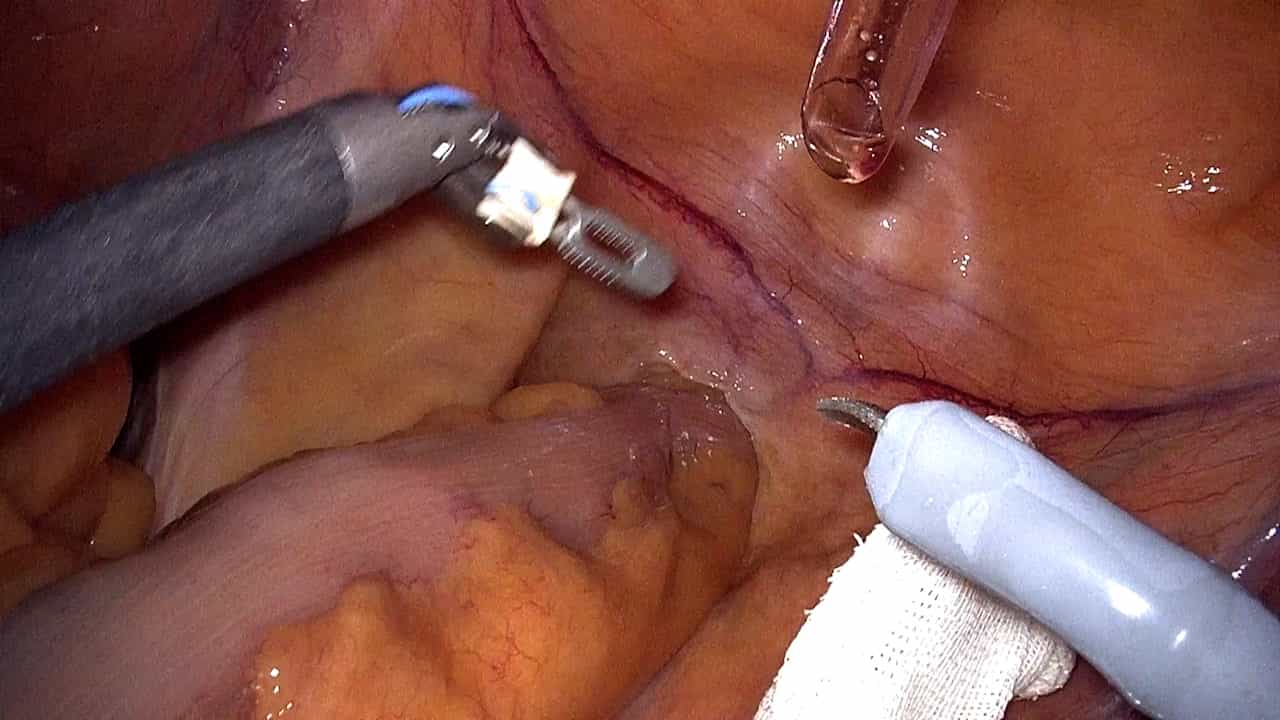

Surgical Robot-Assisted Transanal Specimen Extraction Radical Sigmoidectomy Without an Auxiliary Abdominal Incision
Published on: June 13, 2025
Beyond total operative time: phase-specific robotic efficiency and postoperative morbidity following colorectal
Mohamed Amin1,2, Mohamed Abosheisha3, Mohamed Salama1
1Department of General Surgery, York and Scarborough NHS Foundation Trust, York, UK.

Abstract:
Robotic colorectal surgery is associated with longer operative times than conventional laparoscopic approaches, yet total operative duration is a composite measure comprising fundamentally different procedural components. It remains unknown as to whether postoperative morbidity is attributable to overall operative length or to specific phases of the robotic procedure. A retrospective single-centre cohort study at York and Scarborough NHS Foundation Trust, UK, included consecutive robotic colorectal resections performed by eight consultant surgeons (Surgeons A-H). Two prespecified cohorts were analysed: Cohort A (primary, N = 490) with complete knife-to-skin and case-completion timestamps; Cohort B (nested, N = 138) with complete intraoperative phase timestamps across six predefined phases. The primary outcome was a composite comprising prespecified postoperative complications, readmission and return to theatre within 30 days, plus all-cause mortality within 90 days. Multivariable binary logistic regression was used to examine associations with total operative duration; restricted cubic splines were used as an exploratory assessment of functional form. In Cohort A (N = 490), the primary composite endpoint occurred in 113 patients (23.1%). Median total operative time was 354 min (IQR 270-442). On multivariable analysis, each additional 30 min of operative duration was independently associated with increased odds of the composite endpoint (adjusted OR 1.08, 95% CI 1.01-1.17, p = 0.036). Greater within-programme cumulative case experience was associated with lower odds of morbidity (OR 0.82 per 10 additional cases, 95% CI 0.73-0.92, p < 0.001). In Cohort B (N = 138; 41 events), no individual operative phase reached statistical significance in the originally fitted adjusted phase models; these phase-level analyses are exploratory and should not be interpreted as evidence that any individual phase is unrelated to morbidity. A longer total operative duration was independently associated with our composite morbidity endpoints after adjustment for age, within-programme case experience, operating surgeon and procedure type. Within the smaller nested phase-timing cohort, no individual phase revealed a statistically significant independent association. These phase-level findings are exploratory and do not establish whether console or non-console components mediate the association observed with total operative duration.
