Related Experiment Video
Updated: Oct 5, 2026
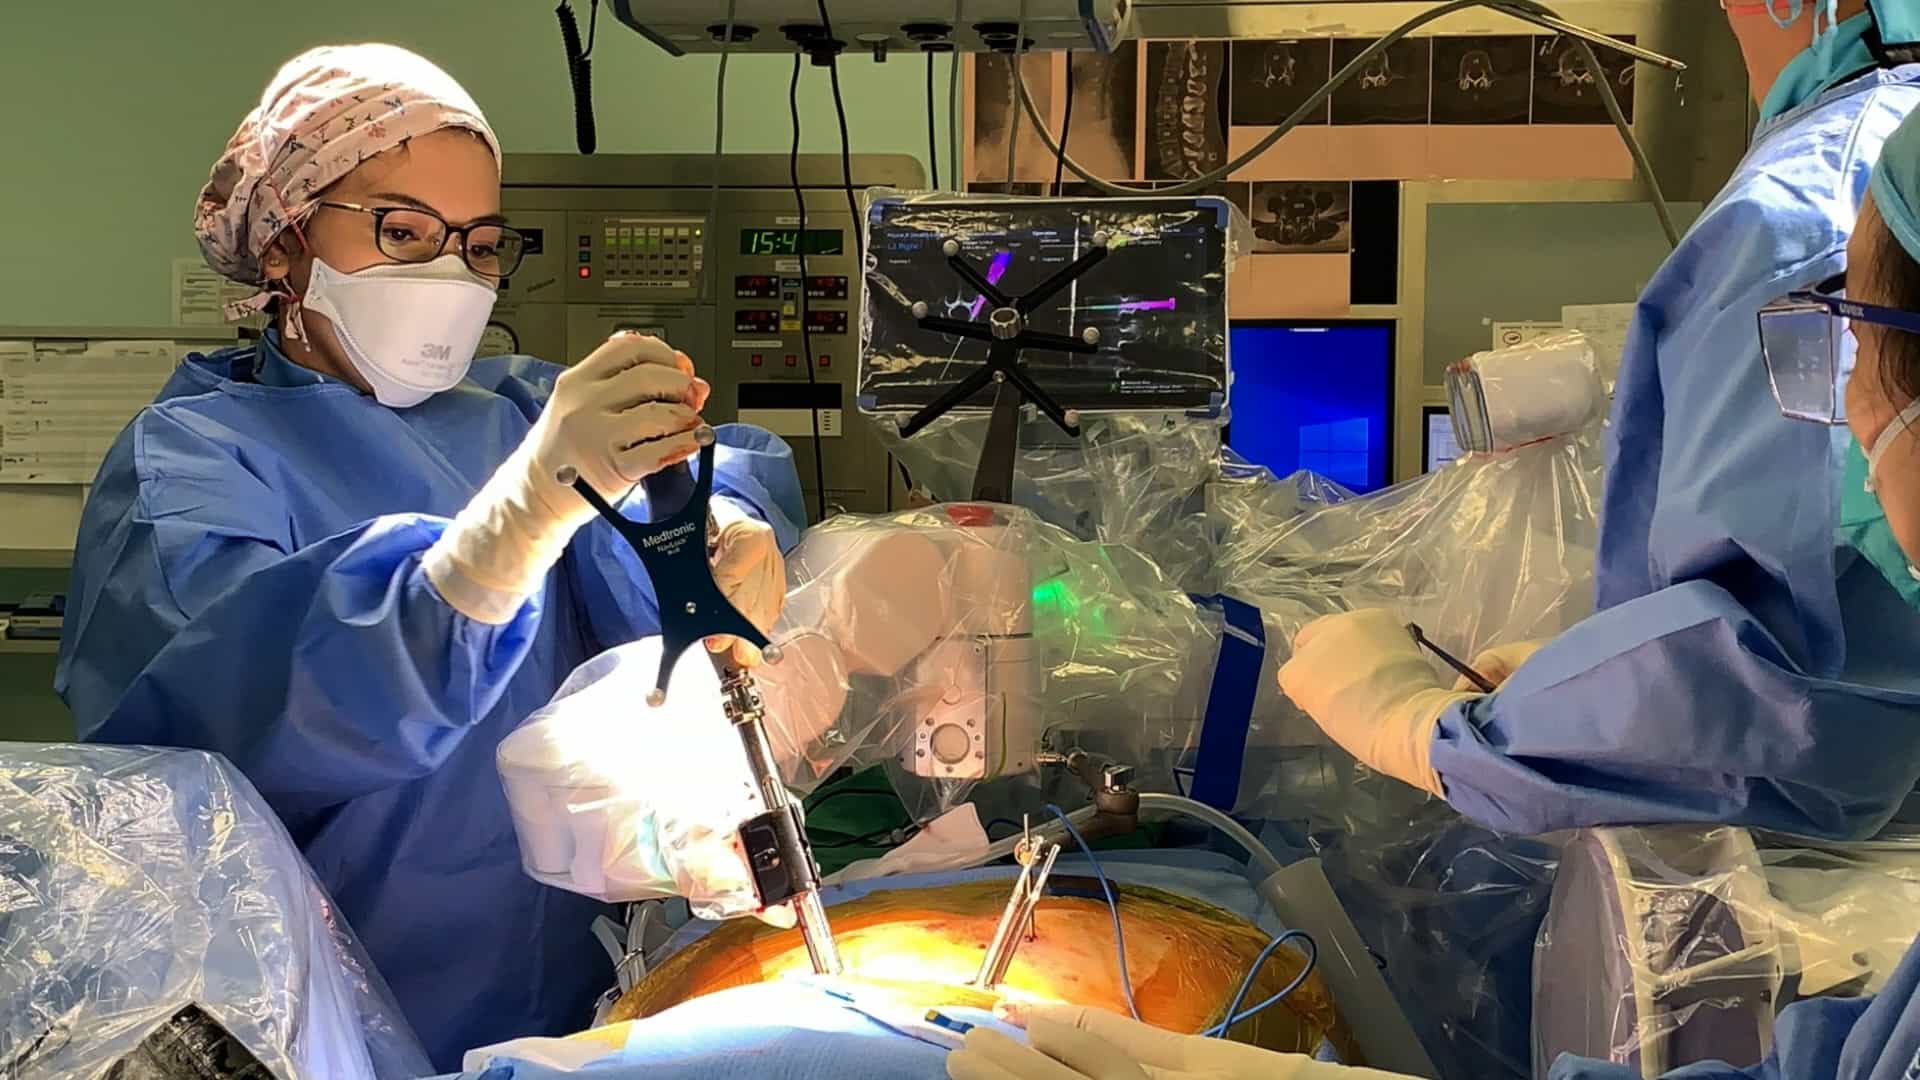

Multilevel Oblique Lumbar Interbody Fusion in Degenerative Lumbar Disc Disease with Instability
Published on: July 25, 2025
Outcomes Following Single-Level Spinal Fusion in Patients With Systemic Lupus Erythematosus
Patrizia M Manziano1, Grace Wilsey1, Sarah Kebaish1
1Department of Orthopaedic Surgery, University of Virginia School of Medicine, Charlottesville, USA.

Abstract:
Introduction Patients with systemic lupus erythematosus (SLE) experience an increased risk of complications and healthcare expenditures after surgery, yet there is limited knowledge regarding outcomes after spinal fusion. This study aimed to investigate outcomes after single-level cervical and lumbar fusion in patients with SLE. A secondary objective was to assess the effect of immunomodulatory therapy (IMT) within the SLE cohort on lumbar fusion outcomes. Methods In this retrospective cohort study, PearlDiver was used to identify patients older than 18 years who underwent single-level anterior cervical discectomy and fusion (ACDF), posterior cervical fusion (PCF), or lumbar fusion between 2010 and 2022. Patients were assessed for age, sex, and Elixhauser Comorbidity Index and were matched in a 1:4 ratio based on SLE status. Medical and surgical complications, postoperative healthcare utilization, two-year surgical outcomes, and mortality rates were evaluated. A subgroup analysis was performed in patients with SLE with and without IMT within 90 days of lumbar fusion. Results After single-level cervical or lumbar fusion, patients with SLE had significantly higher rates of 90-day medical and surgical complications and healthcare utilization than their non-SLE counterparts. Following lumbar fusion, patients with SLE also had higher two-year revision rates. In the lumbar fusion subgroup analysis, patients with SLE on IMT had higher rates of cerebrovascular accidents (OR 1.87, p = 0.020), atelectasis (OR 1.75, p = 0.006), 30-day ED visits (OR 2.44, p < 0.001), 90-day ED visits (OR 1.34, p < 0.001), and 30-day readmissions (OR 1.57, p < 0.001). Conclusion SLE was associated with higher odds of several postoperative complications and healthcare utilization outcomes after single-level cervical or lumbar fusion, as well as higher two-year revision rates following lumbar fusion. These findings suggest that SLE may represent an important marker of perioperative risk. Additional research is needed to identify mitigation strategies and better understand the perioperative risks associated with IMT in this population.