Related Experiment Video
Updated: Oct 6, 2026
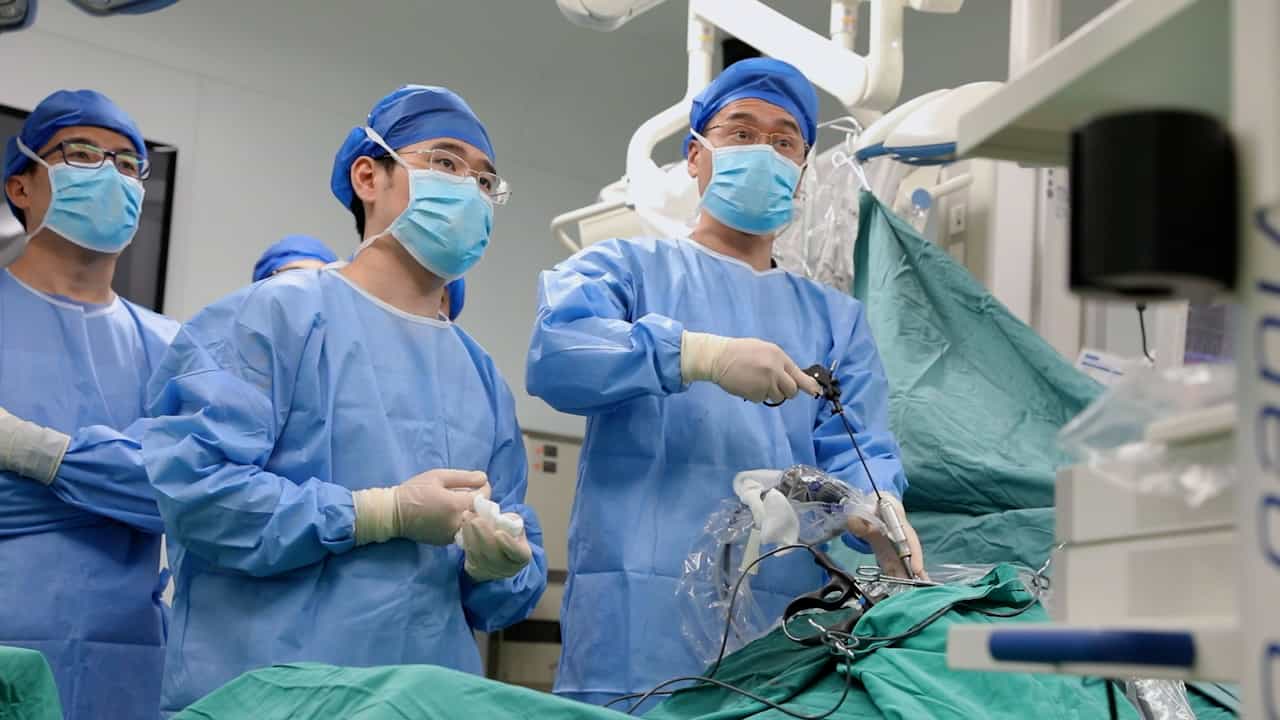

Percutaneous Endoscopic Unilateral-Approach Bilateral Decompression for Lumbar Spinal Stenosis
Published on: February 9, 2024
Spinal Anesthesia With Erector Spinae Plane Block and Sedation for Biportal Endoscopic Lumbar Decompression: A
Tae Hoon Kang1,2, Seokin Jang3, Minjoon Cho1,2
1Department of Orthopedic Surgery, Seoul National University College of Medicine.

Study Design:
Retrospective case-control study.
Objective:
To evaluate the feasibility, safety, and perioperative outcomes of spinal anesthesia combined with erector spinae plane block and dexmedetomidine sedation (SES) compared with general anesthesia (GA) in patients undergoing biportal endoscopic lumbar decompression (BELD).
Background:
Regional anesthesia has shown advantages in spine surgery, including reduced complications and faster recovery. However, spinal anesthesia alone has limitations in duration and patient tolerance during prolonged prone positioning. The erector spinae plane block provides extended analgesia, and dexmedetomidine sedation offers patient comfort without respiratory depression. Evidence regarding the combined application of these techniques for lumbar decompression surgery, especially BELD, is limited.
Materials And Methods:
This retrospective study included 41 patients who underwent 1- or 2-level BELD between June 2023 and June 2024. Nineteen patients received SES, and 22 patients underwent GA. Outcomes included operative times, hemodynamic parameters, postoperative pain, ambulation timing, hospital stay, and complications.
Results:
All SES procedures were completed without conversion to GA. SES was associated with significantly shorter operation times and earlier emergence, improved intraoperative hemodynamic stability, reduced postoperative pain scores (Visual Analog Scale: 0.2 ± 0.7 vs. 2.7 ± 1.4, P < 0.001), earlier ambulation (0.5 ± 0.8 vs. 1.5 ± 0.8 d, P < 0.001), and shorter hospital stay (3.8 ± 1.5 vs. 6.6 ± 3.0 d, P < 0.001). No anesthesia-related complications occurred in the SES group, whereas the GA group experienced several complications, including postoperative nausea and vomiting.
Conclusions:
SES is a feasible and safe anesthetic technique for BELD, offering favorable perioperative outcomes compared with GA. These preliminary results support SES as a promising approach for enhanced recovery protocols in minimally invasive spine surgery. Larger randomized trials are needed to confirm its safety and effectiveness.
Level Of Evidence:
Level III.