Related Experiment Video
Updated: Oct 7, 2026

Single-Anastomosis Duodeno-Ileal Bypass with Sleeve Gastrectomy Model in Mice
Published on: February 10, 2023
Magnetic Duodeno-Ileostomy as a Conversion Procedure After Sleeve Gastrectomy: First Single-Centre Experience in
Ricardo Nassar1, Felipe Giron2,3, Mateo Visbal-Zuluaga4,5
1Department of Surgery, Fundación Santa Fe de Bogotá, Bogotá, Colombia.

Background:
Magnetic duodeno-ileostomy (MAGDI) uses magnetic compression to create a side-to-side duodeno-ileal anastomosis without sutures or staples at the anastomotic site. Outcomes differ between primary and revisional settings. We describe our initial experience with MAGDI as a conversion procedure after sleeve gastrectomy.
Methods:
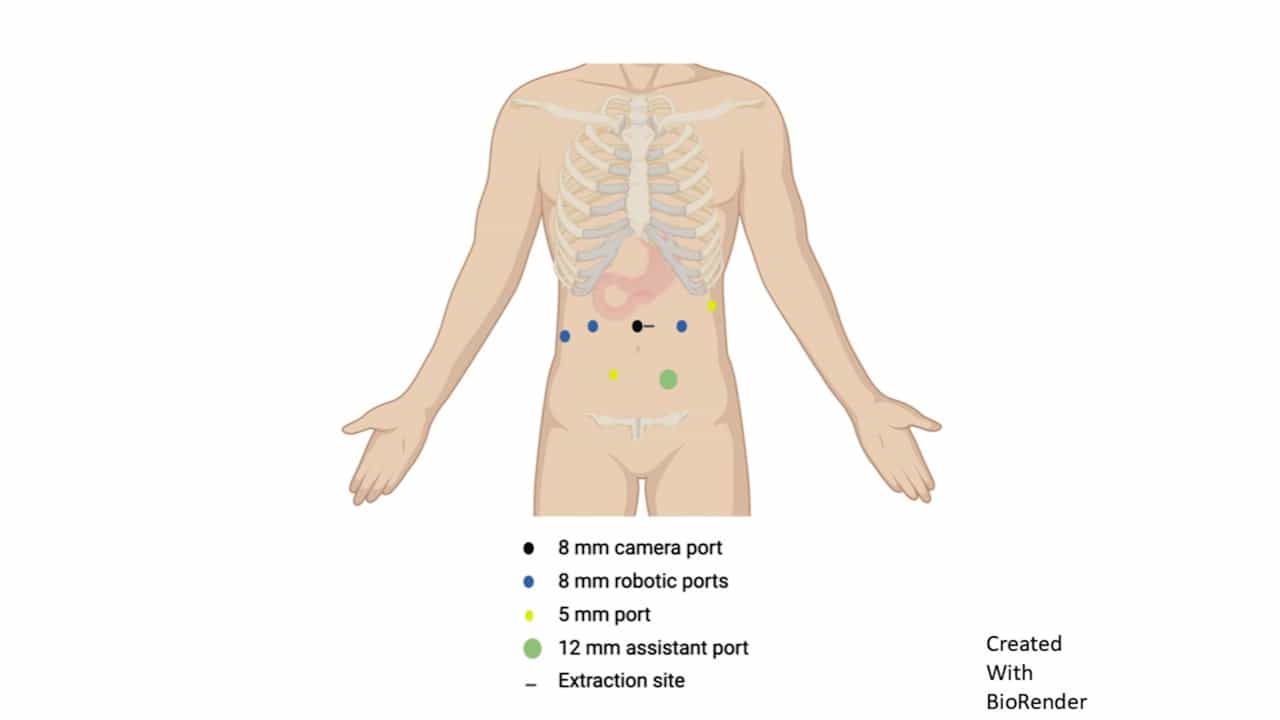
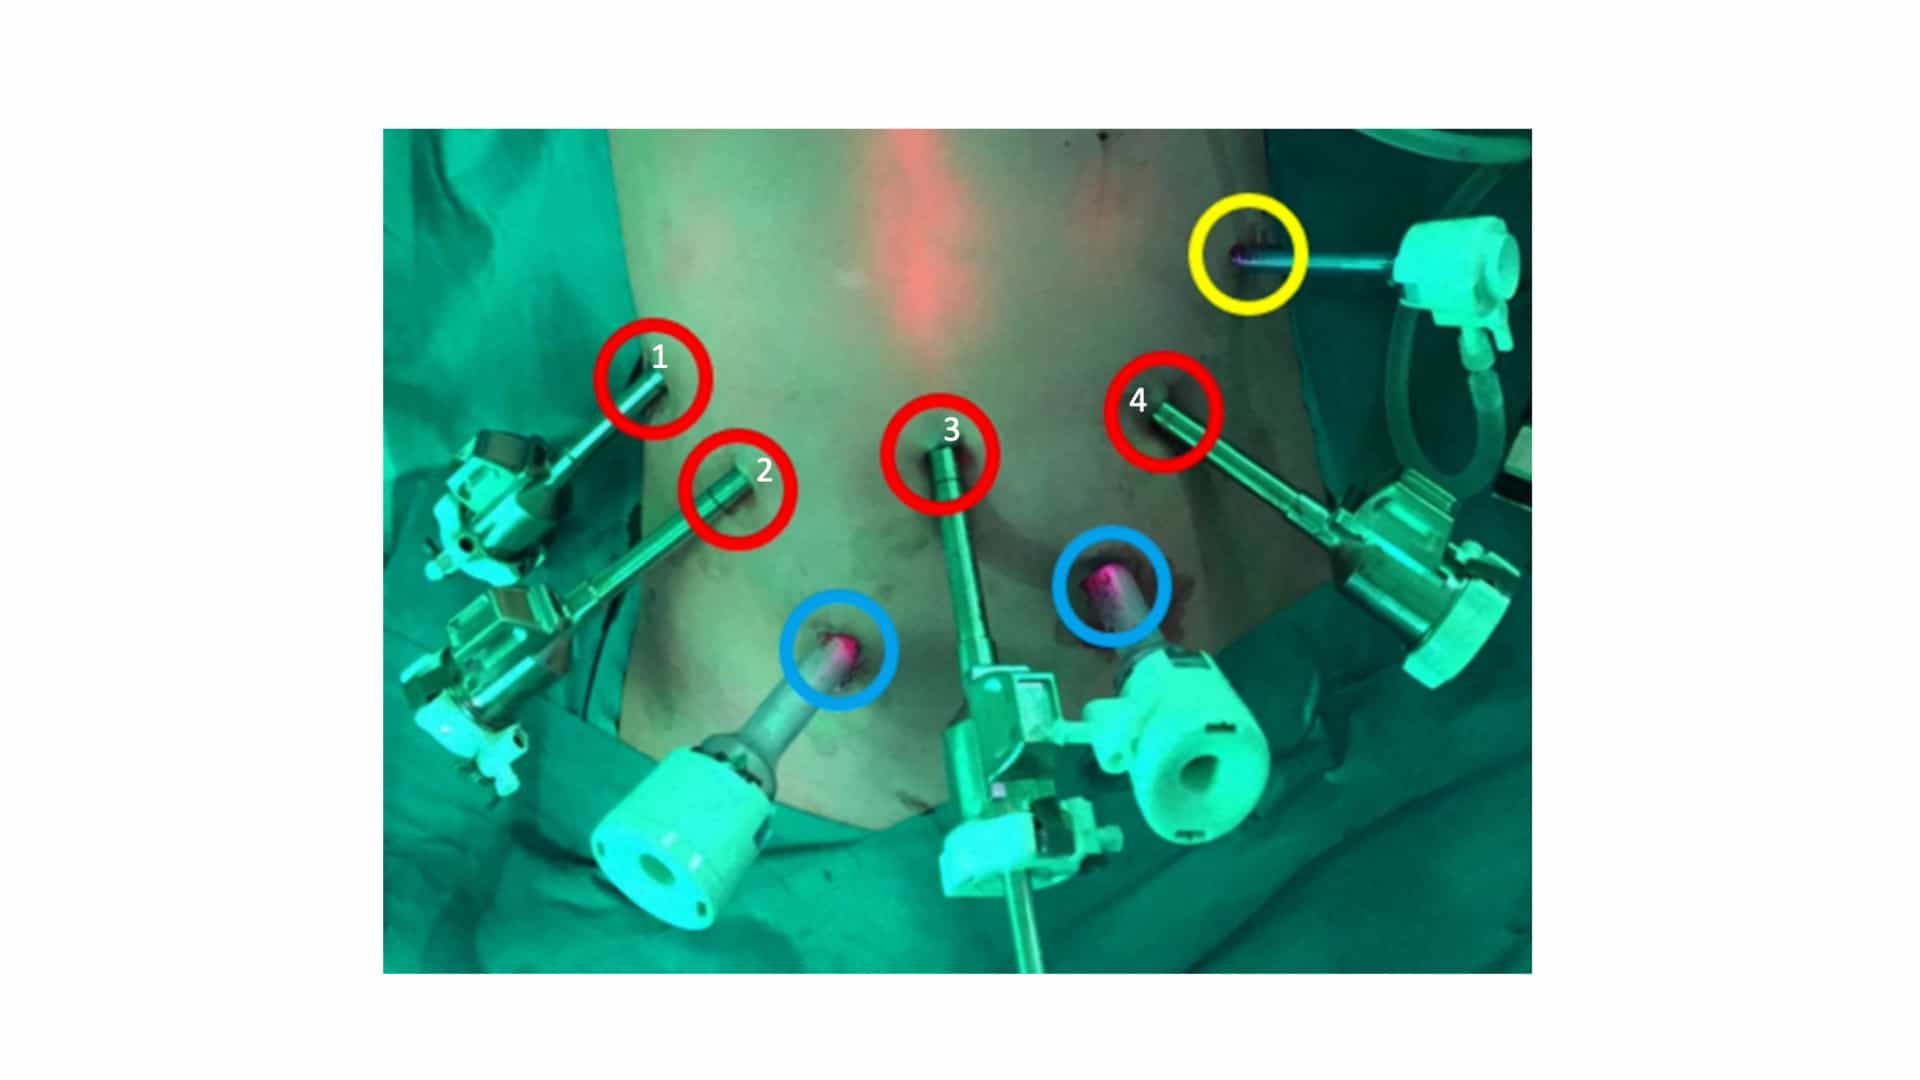
Three consecutive patients underwent MAGDI after laparoscopic sleeve gastrectomy for insufficient clinical response or recurrent weight gain, following multidisciplinary evaluation. Procedures were laparoscopic, with magnetic docking 300 cm proximal to the ileocecal valve. Patients were reviewed monthly, with contrast study and endoscopy at three to four months. Outcomes are reported per patient at six months.
Results:
Deployment was successful in all three patients. Operative times were 113, 72 and 70 min, and anastomosis creation times 17, 14 and 13.6 min; the longest procedure required an enterotomy for distal magnet positioning. All patients were discharged on the day of surgery, without emergency attendance, readmission or reintervention through six months. No anastomotic leak, bleeding or other surgical complication occurred. At six months, total weight loss was 7.6%, 5.3% and 20.2%, and body mass index fell by 3.1, 1.8 and 6.5 kg/m². One patient developed meal-related gastrointestinal symptoms compatible with early dumping, persisting at six months under dietary management. Contrast study and endoscopy confirmed a patent anastomosis in all patients, without stricture or retained device material.
Conclusion:
MAGDI was technically feasible in three selected patients undergoing conversion after sleeve gastrectomy. The sample size and follow-up do not permit conclusions regarding safety or efficacy; larger prospective cohorts are required.