Related Experiment Video
Updated: Oct 7, 2026
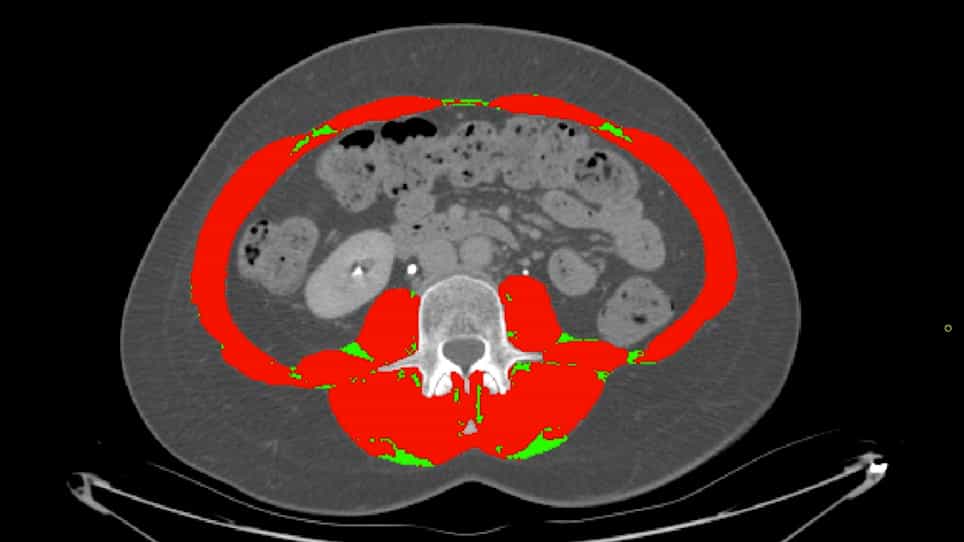

Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
Low-BMI sarcopenic obesity in adults with profound intellectual and multiple disabilities: A body composition
Toshihiko Kohji1, Miki Takaiwa2, Akihiro Ishida3
1Department of Pediatric Neurology, Tokyo Metropolitan Higashiyamato Medical Center for the Severely Disabled, Higashiyamato, Tokyo, Japan; Department of Nutrition, Tokyo Metropolitan Higashiyamato Medical Center for the Severely Disabled, Higashiyamato, Tokyo, Japan.

Purpose:
To clarify the prevalence, longitudinal changes, and body composition characteristics of sarcopenic obesity (SO) in institutionalized adults with profound intellectual and multiple disabilities (PIMD) using bioelectrical impedance analysis (BIA) and CT.
Methods:
From 101 screened residents, 77 institutionalized adults with PIMD (median age, 52 years) underwent annual BIA over three years. Sarcopenia was defined according to the Asian Working Group for Sarcopenia 2019 criteria. Obesity was defined using body fat percentage thresholds (men ≥27%, women ≥38%). CT scans were available for 64 participants, including 31 with concurrent BIA. Factors associated with SO were examined using multivariable logistic regression.
Results:
Sarcopenia was universal, and 51% exhibited SO. The SO group showed an "anthropometric paradox": higher BMI (18.2 vs. 15.9 kg/m2) but lower skeletal muscle index (SMI; 3.4 vs. 4.2 kg/m2) and phase angle (PA; 3.5 vs. 3.8°) than the sarcopenia-only group. Postural control ability (OR 0.38), SMI (OR 0.53), and PA (OR 0.41) were independently associated with SO. Over three years, SMI decreased (3.9 to 3.6 kg/m2) and body fat increased (31% to 35%) significantly. BIA markers demonstrated high concurrent validity; fat mass correlated with CT-measured total fat area (ρ = 0.84) and visceral fat area (ρ = 0.71), SMI with total abdominal muscle area (ρ = 0.778), and PA with low-attenuation muscle area (ρ = -0.501).
Conclusion:
BMI-based assessment alone underestimates adverse body composition in adults with PIMD. BIA and CT are valuable for detecting low-BMI SO and visualizing myosteatosis, supporting individualized nutritional and rehabilitation strategies.