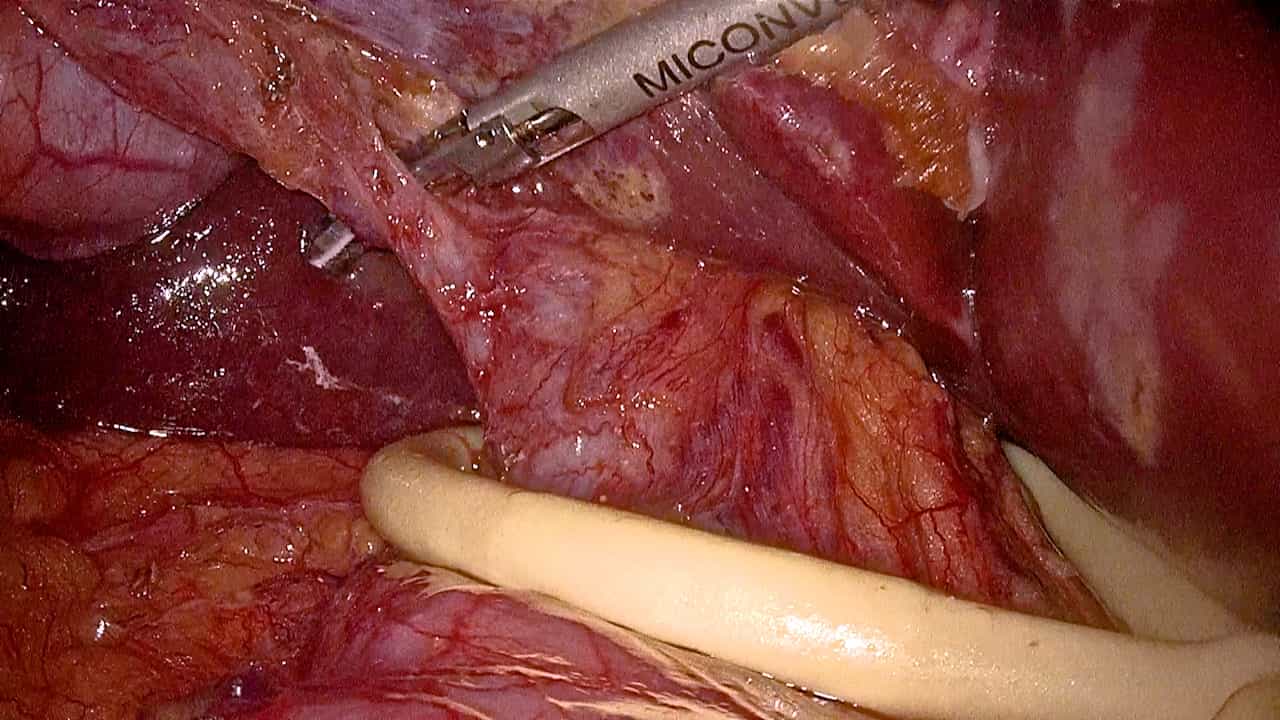
Related Experiment Video
Updated: Oct 7, 2026
Laparoscopic Anatomic S7+S8d Resection Preserving Inferior Right Hepatic Vein and S6 with Right Hepatic Vein Transection
Published on: December 30, 2025
What are the subsegments of the right hemiliver and when are they surgically relevant? A systematic review
Kah Heng Alexander Lim1, Clare O'Sullivan2, Minghao Zheng3
1School of Biomedical Sciences, University of Western Australia, Perth, Western Australia, Australia; WA Liver and Kidney Surgical Transplant Service, Sir Charles Gairdner Hospital, Nedlands, Western Australia, Australia.

Background:
Since publication of the Tokyo 2020 consensus that formalised definitions of hepatic subsegments and cone units based on inflow, information on these smaller-than-Couinaud entities and their surgical relevance remains sparse.
Methods:
A systematic review was performed to identify right hemiliver subsegments; focusing on resections, intraoperative visualisation, and anatomical studies.
Results:
74 articles were included (80% from East Asia), describing a wide range of techniques to isolate subsegmental inflow. Resections of 8 dorsal and 8 ventral are consistently described, with authors favouring transfissural approaches to access subsegment glissonean pedicles. Subsegments bordering the right hepatic vein are potential sources of nomenclature confusion. Of these, the entity '6 ventral' - supplied by inflow from the right posterior trunk but residing medial to the right hepatic vein - is a target for preservation during major resections of the right anterior section. Subsegments uniformly supplied by side-branches from a trunk can be classified in hilum-distal order; others formed by terminal branching of right anterior/posterior trunks are poorly described using heterogeneous nomenclature.
Conclusions:
Reproducibility of subsegment-level reporting remains limited. International expert collaboration is required to standardise nomenclature and assess inter-observer reliability. This would improve external validity and facilitate comparison of increasingly complex inflow-based liver resections.