Related Experiment Video
Updated: Oct 7, 2026
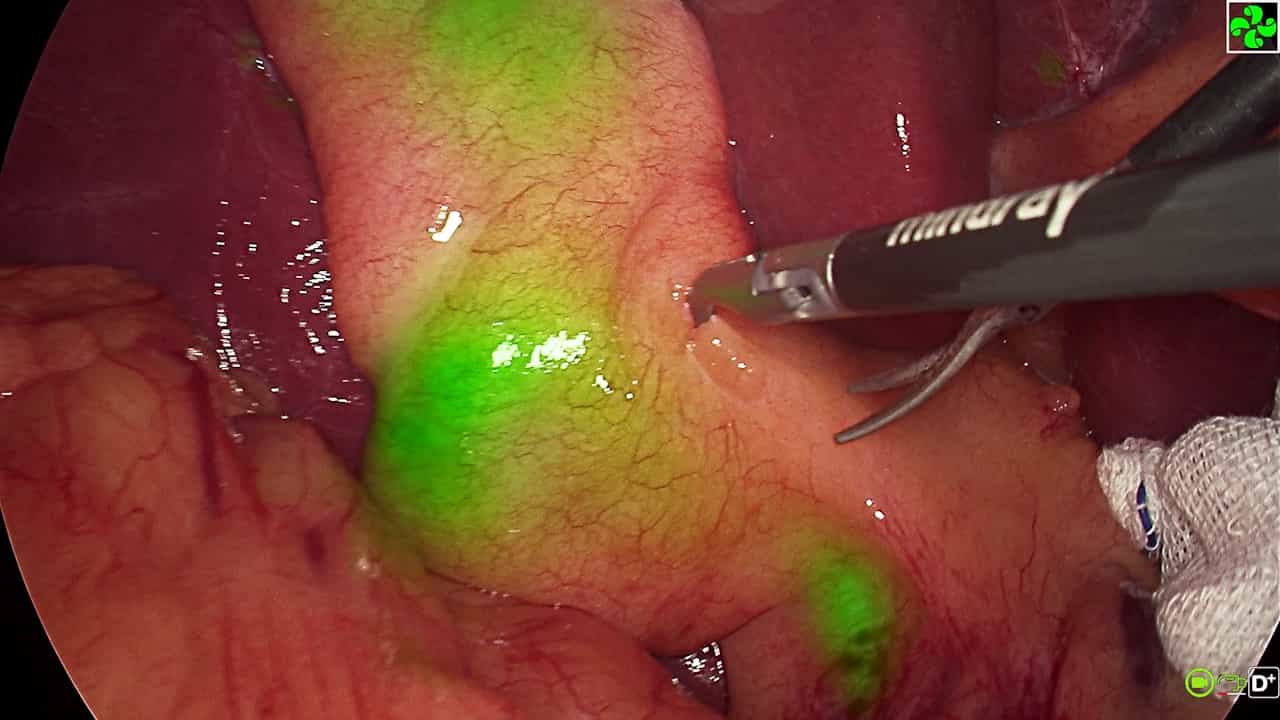

Laparoscopic Cholecystectomy with Indocyanine Green Fluorescence: Choledochoscopic Stone Extraction and Primary Duct Suture
Published on: November 25, 2025
Fluoroscopy-guided colorectal stent placement for distal malignant colorectal obstruction: a retrospective
Aycan Uysal1, Mert Göl1, Devrim Akıncı1
1Hacettepe University Hospital, Department of Radiology, Ankara, Türkiye.

Purpose:
Malignant distal colorectal obstruction is associated with substantial morbidity and mortality when managed with emergency surgery. This study aimed to evaluate the technical and early clinical outcomes, safety, procedural radiation exposure, and stent-related reintervention of fluoroscopy-guided self-expandable metal stent (SEMS) placement.
Methods:
This retrospective single-center study included patients treated between January 2018 and December 2025. Bridge-to-surgery or palliative intent was established before stent placement and retrospectively abstracted from contemporaneous records. Primary end points were technical success and early clinical success within 48 hours. Secondary end points included adverse events within 30 days, stent-related reintervention, time to oral intake, total procedure time, fluoroscopy time, and dose-area product.
Results:
The cohort comprised 19 patients. Technical success was achieved in all patients [100%; 95% confidence interval (CI), 82.4%-100%], and early clinical success in 18 (94.7%; 95% CI, 74.0%-99.9%). Median time to oral intake was 3 days (interquartile range, 2-5 days). Median total procedure time was 38 minutes (range, 25-55 minutes). Median fluoroscopy time was 4.5 minutes (range, 3.8-8.0 minutes), and median dose-area product was 6.4 Gy·cm2 (range, 5.1-8.8 Gy·cm2). One severe adverse event occurred (5.3%; 95% CI, 0.1%-26.0%): delayed perforation requiring surgery. No stent migration or 30-day mortality occurred. Stenting was performed with bridge-to-surgery intent in 5 patients and palliative intent in 14. All bridge-to-surgery patients underwent surgery after a median of 12 days; 3 underwent primary anastomosis and 2 required stoma creation. Among patients treated with palliative intent, 13 achieved early clinical success and 1 experienced clinical failure. One endoscopic reintervention for delayed stent dysfunction was performed at 150 days.
Conclusion:
Fluoroscopy-guided SEMS placement achieved high technical and early clinical success in selected patients with distal malignant colorectal obstruction and may provide an effective interventional radiology-led decompressive option in experienced centers.
Clinical Significance:
Fluoroscopy-guided SEMS placement can provide timely decompression in selected patients with distal malignant colorectal obstruction within an interventional radiology-led multidisciplinary pathway, with endoscopic support available when needed.