Related Experiment Video
Updated: Oct 8, 2026


Dual Test Gas Pulmonary Diffusing Capacity Measurement During Exercise in Humans Using the Single-Breath Method
Published on: February 2, 2024
Ventilatory drive modulates the temporal evolution of multidimensional dyspnoea during constant-load exercise in
Leah M Mann1, Paolo B Dominelli1, Lee M Romer2
1Faculty of Kinesiology, University of Calgary, Calgary, AB, Canada.

Abstract:
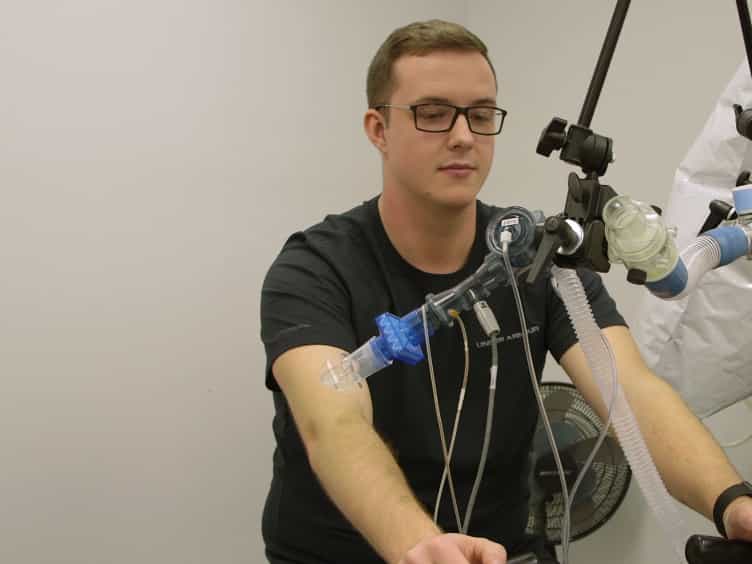
How increased ventilatory drive shapes the temporal evolution and multidimensional experience of exertional dyspnoea remains incompletely understood. This study examined whether experimentally increasing ventilatory drive via dead-space loading (DSL) alters dyspnoea during constant-load exercise. Nine healthy adults (7 male; V̇O2peak 100 ± 16% predicted) performed constant-load cycle ergometry to task failure at 50%Δ between the gas-exchange threshold and V̇O2peak under control (CTRL) and DSL (15% vital capacity) conditions in a randomised crossover design. Dyspnoea intensity, dyspnoea unpleasantness, and leg discomfort were assessed using the Borg CR10 scale, and sensory-perceptual and affective-emotional dimensions using the Multidimensional Dyspnoea Profile. Compared with CTRL, DSL increased end-tidal CO2, minute ventilation, tidal volume, and inspiratory pressures without altering cardiometabolic responses, and reduced time to task failure (10.0 ± 2.3 vs. 13.8 ± 4.6 min; p = .012). Dyspnoea intensity rose more rapidly during DSL, but was similar at task failure, whereas dyspnoea unpleasantness was consistently higher without a distinct temporal divergence. Leg discomfort and dyspnoea descriptor frequencies did not differ between conditions. Post-exercise multidimensional profiling revealed greater breathing unpleasantness (p = .008), immediate perception scores (p = .036), respiratory work/effort (p = .040), and air hunger (p = .027), with no differences in emotional response scores. Greater iso-time increases in dyspnoea intensity and unpleasantness were associated with shorter time to task failure (r = - .82 to - 0.88; p ≤ .007). These findings suggest that increased ventilatory drive accelerates dyspnoea development and preferentially augments sensory-perceptual characteristics of dyspnoea, contributing to earlier task failure despite similar end-exercise symptom intensity.
Related Concept Videos
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:25
Hyperpnea and Hyperventilation
 01:29
Mechanical Ventilation I: Indication and Settings
 01:24
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...