Related Experiment Video
Updated: Oct 8, 2026
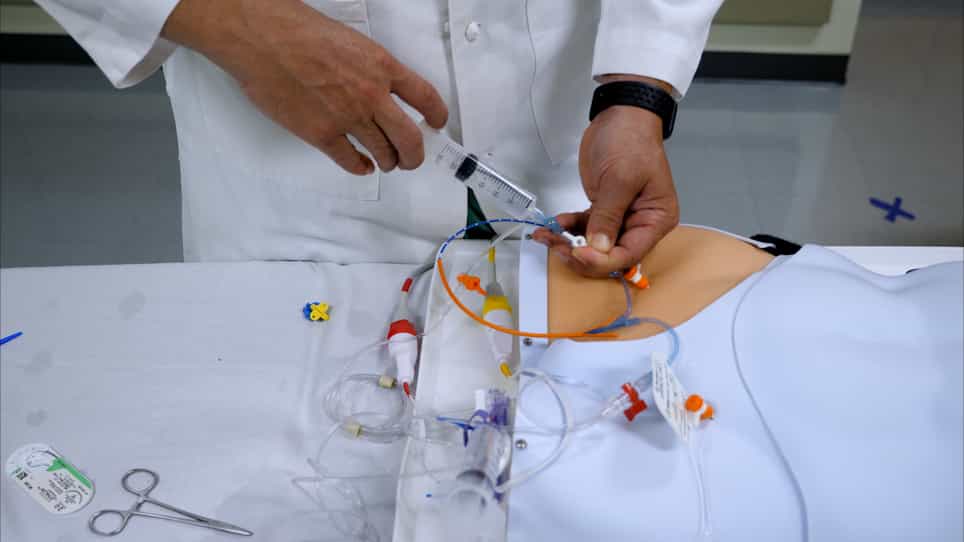

Complete and Partial Resuscitative Endovascular Balloon Occlusion of the Aorta for Hemorrhagic Shock
Published on: May 19, 2022
Bystander AED effectiveness despite low utilisation in OHCA
Youdong Sohn1, Gyuchong Cho1, Youngsuk Cho1
1Department of Emergency Medicine, Kangdong Sacred Heart Hospital, Hallym University College of Medicine, Seoul, Republic of Korea.

Objectives:
Observational estimates of bystander automated external defibrillator (AED) effectiveness are inconsistent in settings with mature public-access defibrillation infrastructure but low utilisation, partly because the conventional reference group pools emergency medical services (EMS)-shocked with non-defibrillated patients. We estimated bystander AED effectiveness against a partitioned no-defibrillation reference, tested effect modification by location, and quantified the deployment-utilisation gap.
Methods:
Retrospective analysis of a prospectively collected multicentre out-of-hospital cardiac arrest (OHCA) registry (Korea, October 2015-June 2025; 23,918 adults of presumed medical aetiology). A three-tier prehospital defibrillation-provider variable was defined: bystander AED applied (n = 383); EMS-delivered shock without preceding bystander AED (n = 5,975); and no prehospital defibrillation (reference; n = 17,560). Primary outcomes were survival to discharge and good neurological outcome (Cerebral Performance Category 1-2), analysed by multivariable logistic regression with propensity-score, inverse-probability-weighting and location-stratified secondary analyses.
Results:
Bystander AED application was associated with improved survival (adjusted odds ratio [aOR] 1.60; 95% CI 1.19-2.14) and good neurological outcome (2.31; 1.65-3.23), comparable to that of EMS-delivered shock; the pooled-control specification attenuated estimates to non-significance (survival 1.09; neurological 1.14). Shock-delivered applications significantly exceeded EMS-delivered shock for neurological outcome (aOR 1.43; P = 0.03). Effectiveness did not differ by location (interaction P ≥ 0.15). Bystander AED was applied in 8.5% of Public-area versus 1.9% of Non-public AED-opportunity cases - a 4.5-fold gap.
Conclusions:
Bystander AED was associated with improved outcomes when applied, comparable to or exceeding EMS-delivered shock; the dominant constraint was the deployment-utilisation gap, greatest in residential settings. Residential rapid-activation infrastructure warrants policy priority alongside, not instead of, continued device placement.

Related Concept Videos
 01:23
Cardiopulmonary Resuscitation III: AED Use
 02:09
Bystander Effect
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:08
The Availability Heuristic