Related Experiment Video
Updated: Oct 8, 2026
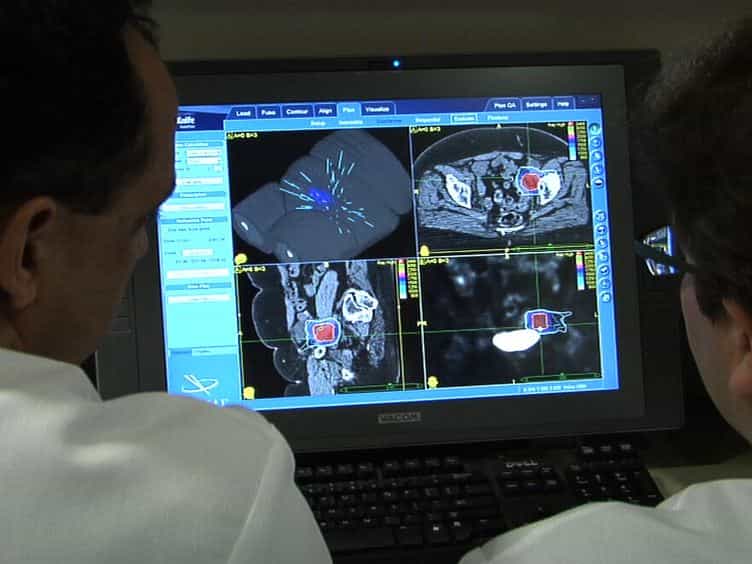

Stereotactic Radiosurgery for Gynecologic Cancer
Published on: April 17, 2012
Case Report: Image-guided adaptive lattice radiotherapy for a 2,772-cc ulcerative triple-negative breast cancer
Min Xiao1, Qian Wang1, Gangyang Yu1
1Department of Radiation Oncology, Hankou Hospital Affiliated with Wuhan University of Science and Technology (Wuhan Hankou Hospital), Wuhan, Hubei, China.

Background:
Giant ulcerative breast cancers (>2,000 cc) with active hemorrhage present a critical therapeutic challenge, as conventional radiotherapy carries a high risk of severe toxicity to surrounding organs. Lattice radiotherapy (LRT) delivers spatially fractionated high-dose vertices within a low-dose background, offering the potential to overcome dose constraints. However, rapid tumor regression induced by LRT may render fixed plans unsafe, necessitating adaptive replanning.
Case Presentation:
A 46-year-old female with stage IV triple-negative breast cancer (TNBC; BRCA1 germline mutation) presented with a 2,772.2-cc ulcerative left breast and axillary masses complicated by persistent hemorrhage, recurrent infection, and Eastern Cooperative Oncology Group (ECOG 3). After failure of systemic therapies including fluzoparib, image-guided adaptive LRT was initiated (gross tumor volume [GTV]: 12 Gy/4 fractions; lattice vertices: 60 Gy/4 fractions). Before fractions 2-4, the GTV was re-contoured on daily fan-beam computed tomography (FBCT), lattice vertices were redistributed away from the skin surface, and plans were recalculated. LRT was followed by conventionally fractionated VMAT (40 Gy/20 fractions). Hemorrhage ceased within 2 weeks and persistent fever subsided, becoming intermittent and progressively less frequent. Tumor volume progressively decreased by 21.2% during LRT (before fraction 4), 81.5% post-VMAT, and 96.1% (108.3 cc residual) at 2-month follow-up. Cumulative organ-at-risk (OAR) doses, estimated by rigid-registration dose accumulation, remained within tolerance, with only Grade 2 dermatitis and no ≥Grade 3 toxicity.
Conclusion:
This case demonstrates the technical feasibility of image-guided adaptive lattice replanning in a rapidly changing, ultra-large fungating breast tumor. Adaptive replanning may reduce geometric displacement of high-dose vertices; however, its dosimetric and clinical benefits require confirmation in further patients and with longer follow-up.
