Related Experiment Videos
ISG Task Force on Upper Gastrointestinal Bleeding (UGIB)-Comparison of Risk Scores in Nonvariceal Bleeding-A
Manoj K Sahu1, Avinash Balekuduru2, Saroj K Sinha3
1Department of Gastroenterology Institute of Medical Sciences & SUM Hospital, SOA Bhubaneswar India.

Background:
To compare the performance of the Glasgow Blatchford score (GBS) to the Total Rockall score (TRS) in predicting clinical interventions in Indian patients with acute nonvariceal upper gastrointestinal bleeding (ANVUGIB).
Materials And Methods:
We prospectively studied ANVUGIB in 93 hospitals in India from October 2014 to September 2018. The etiological, clinical, and investigational details were recorded on a uniform structured proforma. The GBS and TRS were prospectively calculated for all patients. Clinical interventions were defined as blood transfusion, rebleed, and mortality with 30-day follow-up.
Results:
A total of 6450 patients with ANVUGIB were identified, followed up for 30 days and selected for analysis. Almost 5176 (80%) of the patients were male, and the mean age 50.7 ± 16.8 years (2-98 years). Blood transfusion was considered clinically necessary in 115 (1.7%) of the patients. Surgery and interventional radiology were required as rescue therapy in only 20 patients (0.3%) and 22 (0.3%) patients, respectively. The 30-day rebleeding and mortality occurred in 92 (1.4%) and in 184 (2.8%) patients, respectively. GBS was similar to TRS in predicting mortality (AUC 0.687 vs. 0.663) with cutoff values of 10.5 and 3.5 and predicting rebleeding with (AUC 0.637 vs. 0.630) cutoff values of 11.5 and 3.5, respectively. Outcomes were defined as 30-day mortality and rebleeding. Interventions were defined as transfusions, repeat endoscopy, surgery, or interventional radiology.
Conclusions:
GBS was more accurate and had more desirable clinical characteristics in predicting the need for a transfusion for hospitalized patients than TRS. However, both GBS and TRS have poor to modest predictive capability for 30-day mortality and rebleeding. They do not, then, appear to be useful as screening tools to identify people at risk for those two outcomes in a hospital setting.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:24
Esophageal Varices-I: Introduction
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:24
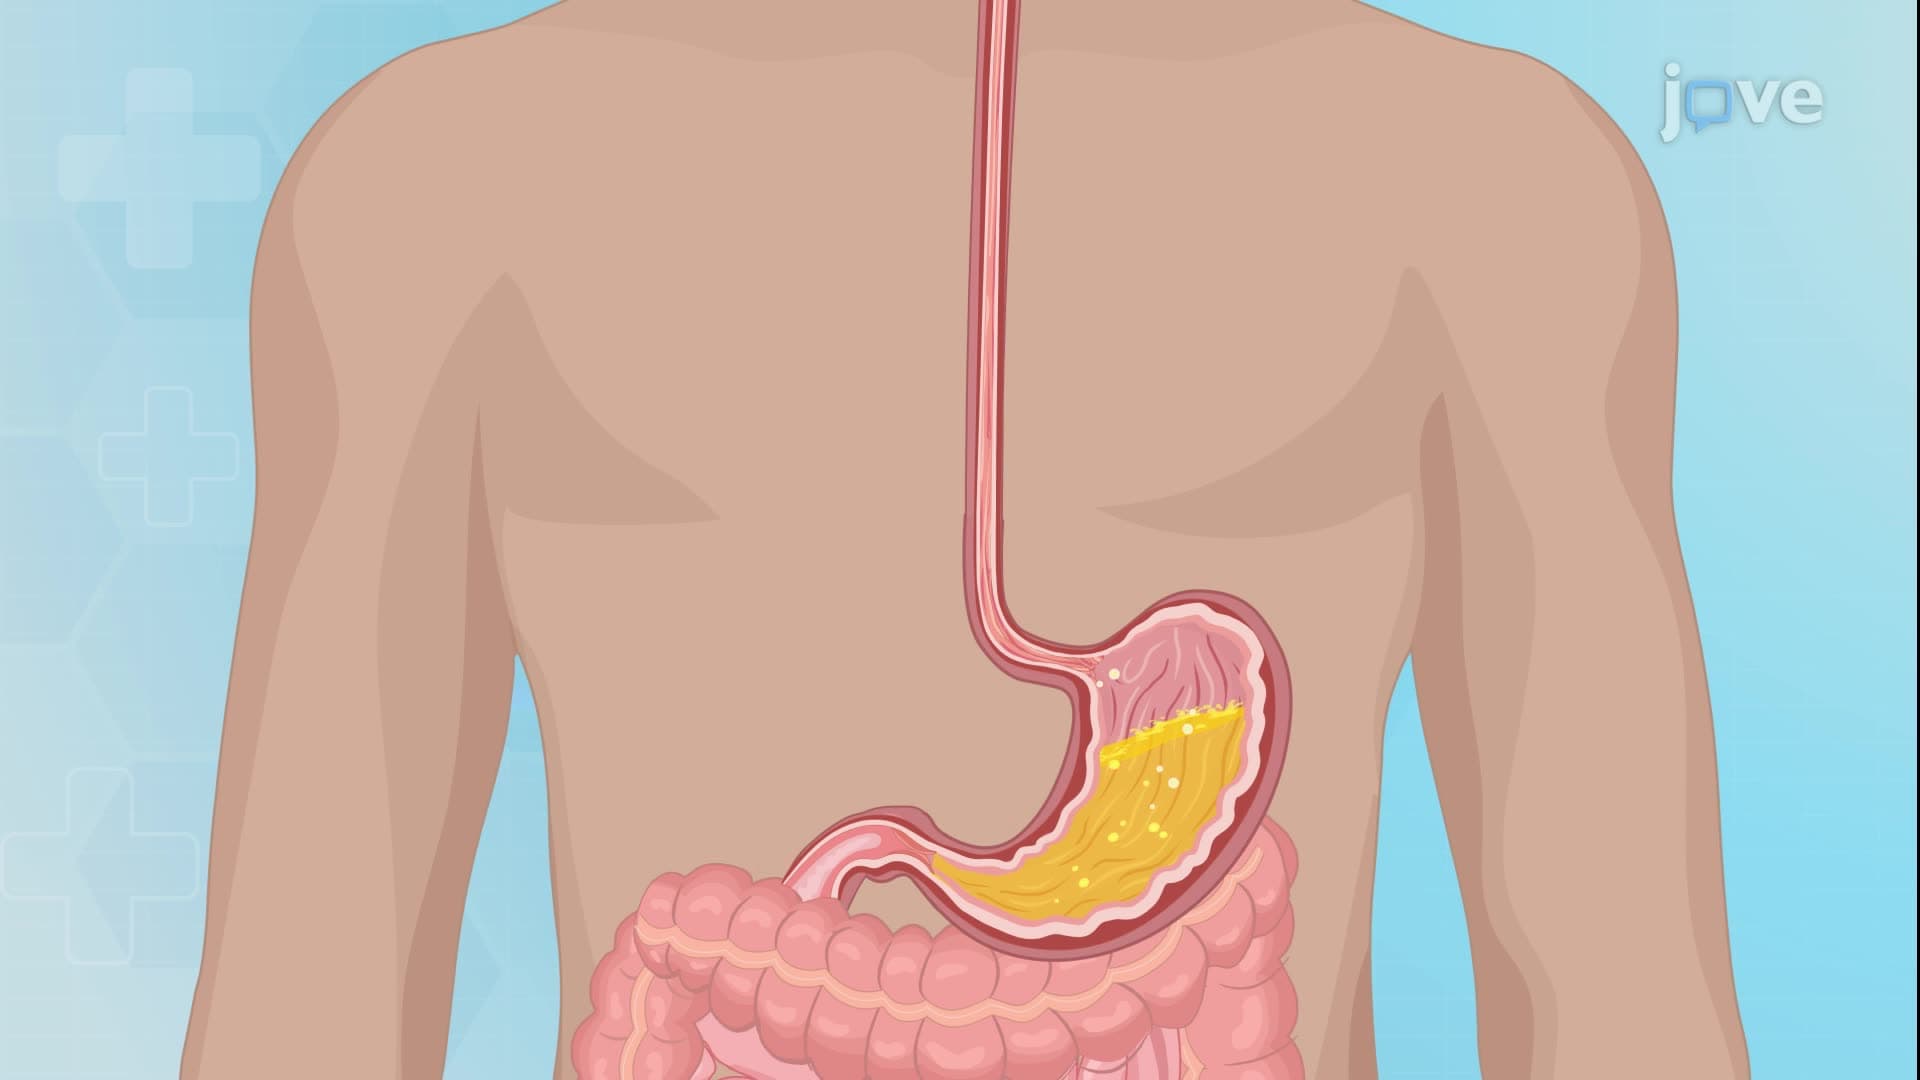
Upper GI Series: Barium Swallow
Purpose and Procedure
Patients undergoing this procedure ingest a liquid containing barium sulfate with a chalky...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.