Related Experiment Video
Updated: Oct 9, 2026
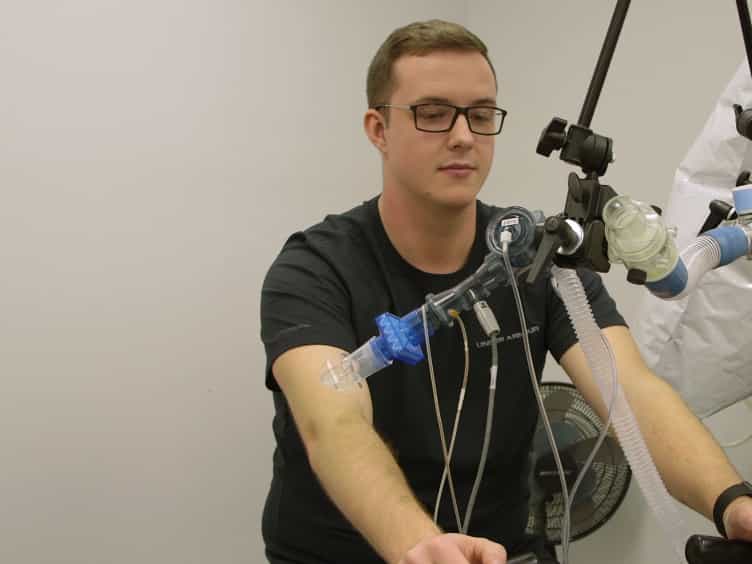

Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Left ventricular transmural pressure and ventilatory inefficiency during exercise in advanced heart failure
Barkin Kultursay1, Seda Tanyeri Uzel2, Murat Karacam3
1Department of Cardiology, Tunceli State Hospital, Cumhuriyet Mah. 552. Sokak No: 2, 62000 Tunceli/Merkez, Türkiye.

Background:
Baseline intracavitary haemodynamic measurements frequently demonstrate an inconsistent relationship with exertional performance. This may reflect an incomplete interpretation of left ventricular (LV) filling pressures. LV transmural pressure difference (ΔPTM = LV end-diastolic pressure [LVEDP]-right atrial pressure [RAP]) integrates LV filling pressure with right ventricular/pericardial constraint and may provide a composite representation of resting haemodynamic conditions. Ventilatory efficiency, assessed by the minute ventilation-carbon dioxide production (VE/VCO2) slope during cardiopulmonary exercise testing (CPET), is a leading representation of cardiopulmonary reserves and a powerful prognostic marker in heart failure (HF). Whether ΔPTM is associated with exercise ventilatory efficiency beyond conventional resting filling pressure measurements remains unclear.
Methods:
We retrospectively studied 422 patients with advanced HF (LVEF ≤25%) who underwent right-heart catheterization and CPET. ΔPTM was analysed both continuously and by tertiles. The primary outcome was VE/VCO2 slope; peak VO2 was a secondary outcome. Bayesian multivariable regression models were adjusted using a directed acyclic graph-derived confounder set. Sensitivity analyses compared ΔPTM with LVEDP and RAP modelled individually and jointly.
Results:
Among 422 patients (mean age 51.3 ± 10.8 years; 62 [14.7%] female), higher ΔPTM was independently associated with a lower VE/VCO2 slope (posterior mean β = -0.34 per mmHg; 95% credible interval [CrI] -0.58 to -0.11; 99.7% posterior probability of a negative association). Unadjusted VE/VCO2 slope decreased from 40.2 (31.7-67.1) in the lowest ΔPTM tertile to 34.9 (30.6-44.8) in the highest tertile (P = .029). The adjusted posterior predictive difference between the highest and lowest ΔPTM tertiles was -4.42 units (95% CrI -7.85 to -0.62). Following multivariable adjustment, ΔPTM showed no significant association with peak VO2 (posterior mean β = +0.06; 95% CrI -0.02 to +0.14). Neither LVEDP nor RAP, modelled individually or jointly, demonstrated independent associations with ventilatory efficiency.
Conclusion:
Resting ΔPTM was inversely associated with the VE/VCO2 slope during exercise, whereas no independent association was observed with peak VO2. Compared with individual left- or right-sided filling pressures, ΔPTM provides a parsimonious summary of the balance between left-sided distending pressure and right-sided constraint associated with ventilatory efficiency in advanced HF.

Related Concept Videos
 01:29
Heart Failure II: Pathophysiology
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:22
Mitral Stenosis I: Introduction
 01:20
Mitral Regurgitation I: Introduction
 01:17
Pathophysiology of Heart Failure
 01:26
Heart Failure III: Clinical Manifestations