Related Experiment Video
Updated: Oct 9, 2026


Establishment and Evaluation of a Risk Prediction Model for Pathological Escalation of Gastric Low-Grade Intraepithelial Neoplasia
Published on: February 16, 2024
Gastric dysplasia: an integrated classification of surface epithelium-derived precursor lesions
1Department of Pathology, The University of Tokyo, 7-3-1 Hongo, Bunkyo-ku, Tokyo, 113-0033, Japan. usikut@g.ecc.u-tokyo.ac.jp.

Abstract:
Gastric dysplasia comprises a heterogeneous group of non-invasive epithelial neoplasms with distinct clinicopathological and biological characteristics. This review focuses on surface epithelium-derived lesions, including intestinal-type, foveolar-type, and serrated dysplasia/adenoma. Conventional low-grade intestinal-type dysplasias/adenomas arise mainly in atrophic and metaplastic mucosa associated with Helicobacter pylori infection or, much less frequently, autoimmune gastritis. Small, pale, flat-elevated lesions with orderly small-intestinal differentiation generally behave indolently, whereas large size, redness, depression, nodularity, high-grade histology, and abnormal p53 expression are associated with an increased risk of progression. Foveolar-type dysplasia/adenoma is particularly heterogeneous. Flat-elevated foveolar-type adenoma, raspberry-type adenoma, and dysplasia arising in fundic gland polyps represent distinct dysplasia subtypes with indolent behavior. In contrast, other foveolar-type lesions are biologically heterogeneous; some are associated with microsatellite instability-high or Epstein-Barr virus-associated gastric carcinoma, whereas others may represent the superficial component of poorly differentiated or deceptively well-differentiated adenocarcinoma. Gastric serrated dysplasia is rare but is frequently associated with invasive carcinoma and should be regarded as a high-risk lesion requiring complete resection. Accurate diagnosis therefore requires integration of histological findings with endoscopic appearance and the background gastric mucosa. The principal role of pathological diagnosis is to distinguish dysplastic lesions with indolent behavior from those carrying a non-negligible risk of progression to invasive carcinoma, thereby guiding optimal clinical management.

Related Concept Videos
 01:24
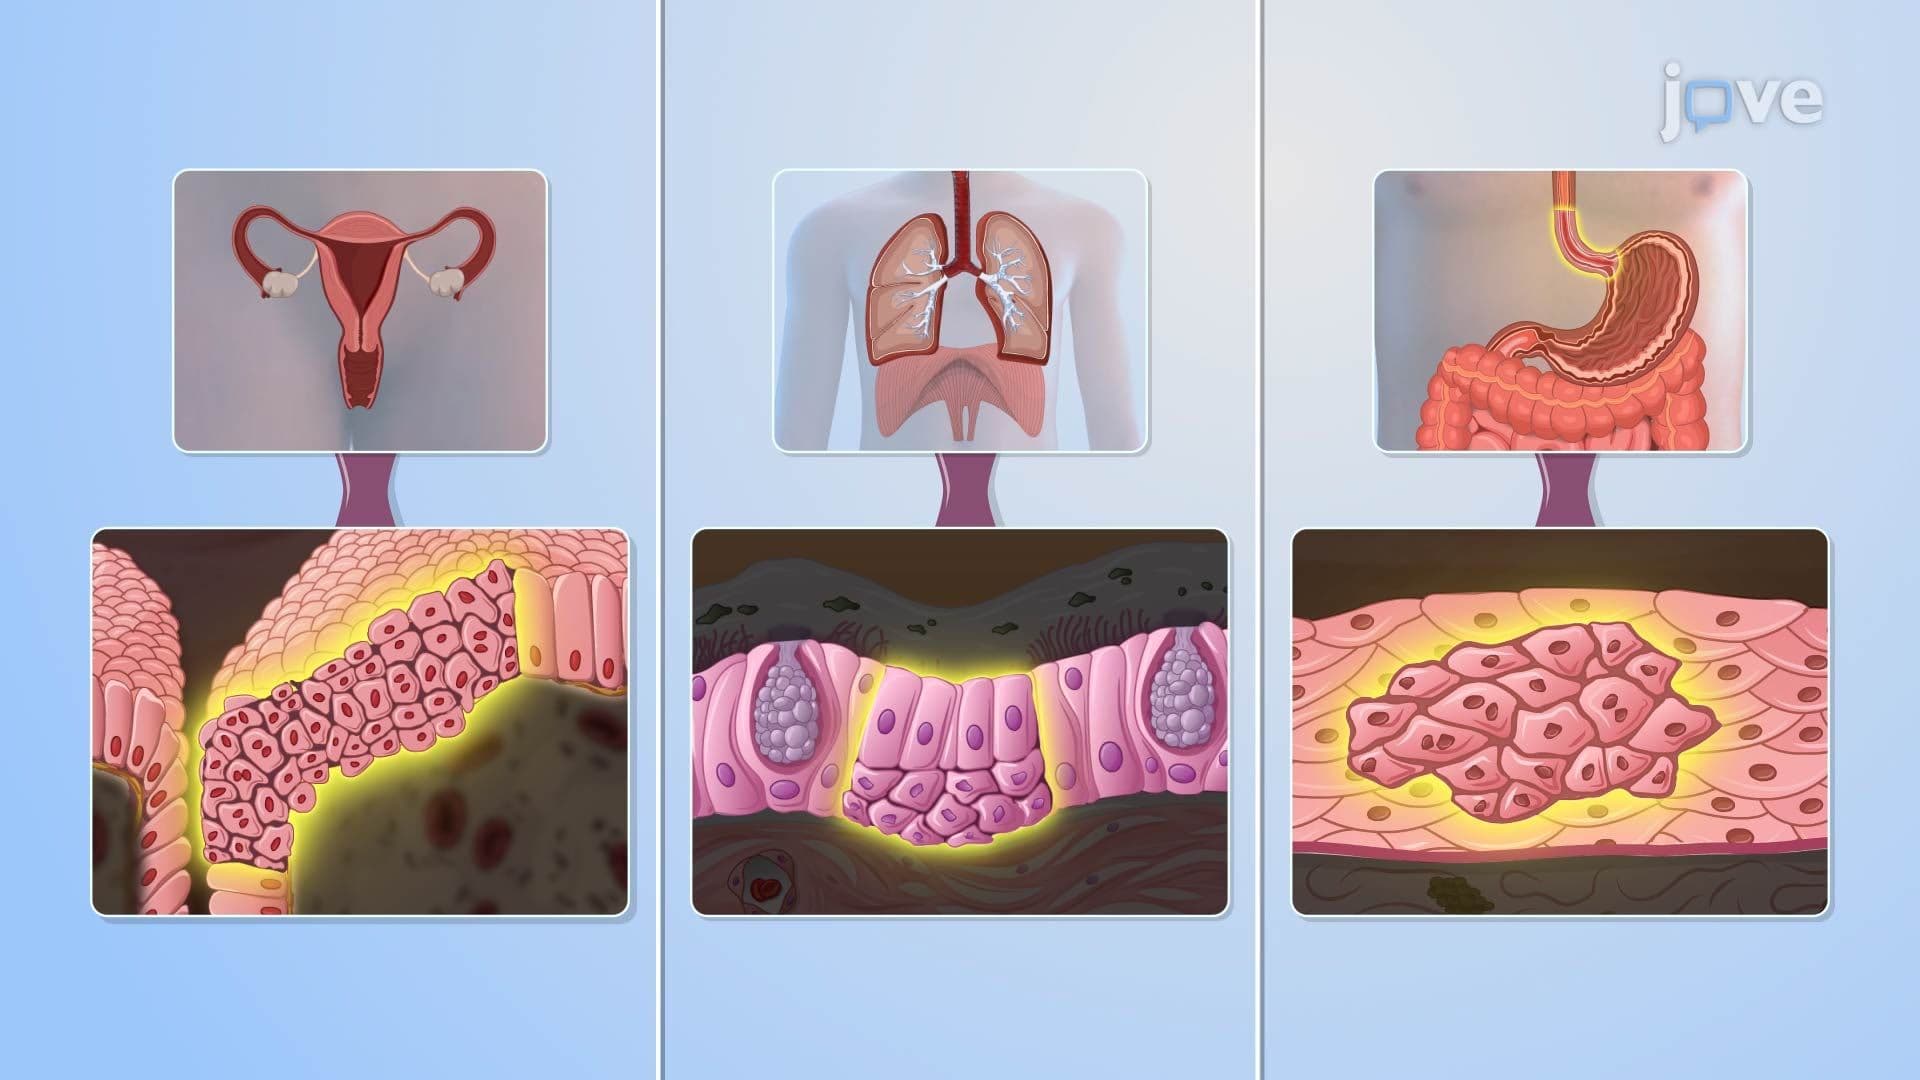
Cellular Adaptation IV: Dysplasia and Metaplasia
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...
 01:26
Gastritis II: Pathophysiology
 01:27
Gastritis-I: Introduction and Types
Acute gastritis presents as a sudden inflammation triggered by various stressors to the stomach lining, such as exposure to corrosive agents, local irritants like aspirin and other NSAIDs, alcohol consumption, radiation therapy, physical trauma, severe burns, sepsis,...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...