Related Experiment Video
Updated: Oct 9, 2026
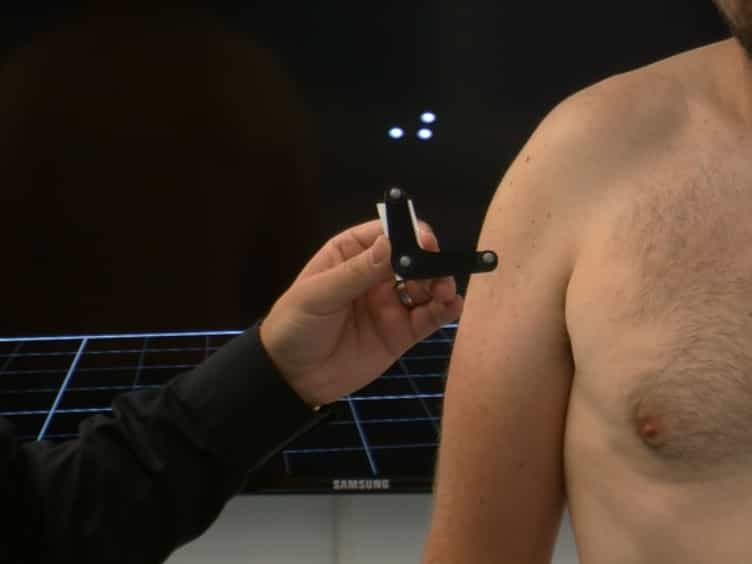

Measurement of Dynamic Scapular Kinematics Using an Acromion Marker Cluster to Minimize Skin Movement Artifact
Published on: February 10, 2015
Scapular posture estimation from manual palpation of anatomical landmarks: An uncertainty and sensitivity analysis
Florent Moissenet1, Hugo Francalanci1, Stéphane Armand2
1Biomechanics and Translational Research in Surgery, Department of Surgery, Geneva University Hospitals and University of Geneva, Geneva, Switzerland; Kinesiology Laboratory, Geneva University Hospitals and University of Geneva, Geneva, Switzerland.

Abstract:
Preoperative planning for reverse total shoulder arthroplasty (rTSA) is commonly based on supine computed tomography (CT), which does not reflect functional standing scapular posture. Integrating standing posture into planning workflows may improve their physiological relevance. One approach consists in registering a CT-derived scapular bone model onto anatomical landmarks acquired in the standing position through manual palpation. However, the impact of clinically realistic landmark positioning variability on the reliability of such bone registration remains unclear. This study aimed to quantify how variability in manually identified anatomical landmarks propagates to uncertainty in glenoid orientation when using a landmark-based bone registration framework. A retrospective cohort of 72 patients undergoing rTSA was analysed. Landmark positioning variability was characterised from CT-based scapular landmarks and from palpation-derived landmarks recorded using motion capture (scapular and thoracic) and propagated using a global uncertainty analysis. A variance-based sensitivity analysis using Sobol indices was conducted to identify the most influential parameters. CT-based scapular landmark variability remained very low (<3 mm). In contrast, motion capture-based landmark variability was higher and differed between anatomical regions. For scapular landmarks, variability remained low along the mediolateral axis (<3 mm) but reached up to 12.7 mm along the other axes. For thoracic landmarks, variability was greater, particularly along the horizontal plane, with deviations up to 18.1 mm. Despite this, the propagated effect on glenoid orientation remained limited: 95% of simulations resulted in angular deviations below 5°, while extreme cases did not exceed 10°. Sensitivity analysis showed that thoracic landmarks, particularly the incisura jugularis, were the primary contributors to variability in glenoid orientation. These findings show that, under the tested conditions, manual landmark-based registration provides a geometrically robust estimate of standing scapular posture. This represents a methodological step toward incorporating standing posture into rTSA planning workflows, although its impact on predicted postoperative impingement-free ranges of motion and clinical decision-making remains to be established.
Related Concept Videos
 01:23
Assessment of the Abdomen III: Palpation
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above the...