Related Experiment Video
Updated: Oct 9, 2026
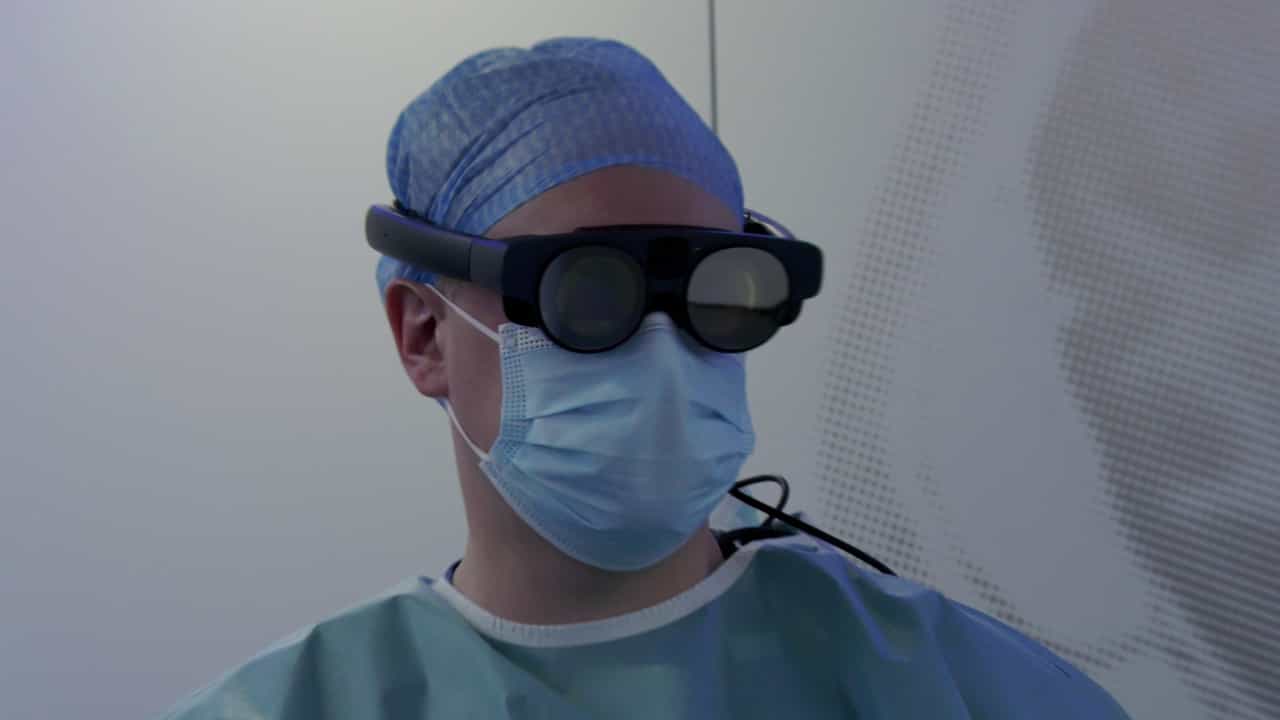

Pedicle Screw Placement Using an Augmented Reality Head-Mounted Display in a Porcine Model
Published on: May 24, 2024
Accuracy of Augmented Reality-Guided Angular Trajectories in Spine Surgery: A Cadaveric Study Comparing 2D-3D vs
Gabriel Urreola1, Jose A Castillo2, Venina Kalistratova1
1School of Medicine, University of California Davis, Sacramento, CA, USA.

Background:
Augmented reality (AR) navigation has demonstrated accuracy for pedicle screw placement but has not been well studied for angular trajectories required to access disc spaces and sacroiliac joints (SIJs). This study evaluated the accuracy of AR-guided angular trajectories comparing 2 registration methods: intraoperative 3D computed tomography (CT)-based registration and 2D-3D registration using intraoperative radiographs matched to preoperative CT imaging.
Methods:
In this prospective cadaveric study, 4 experienced spine surgeons performed 67 AR-navigated angular trajectories targeting thoracic, lumbar, and SIJ anatomy across 4 human cadavers. Jamshidi tools were used to simulate angular navigation. Trajectories were planned using either intraoperative CT registration or 2D-3D registration. Absolute stereotactic accuracy was assessed by comparing postoperative CT trajectories to the system's virtual trajectories. Angular deviations were measured in axial and sagittal planes with a predefined success criterion of a 99% upper confidence bound ≤3.0°.
Results:
All trajectories, including 32 medial, 31 lateral, and 4 intracanal (trajectories directed into the spinal canal to simulate access pathways for decompression or discal approaches), met predefined accuracy criteria for both methods. The 99% upper bounds of angular error were 1.65° (axial) and 1.54° (sagittal) for intraoperative registration and 1.78° (axial) and 1.75° (sagittal) for 2D-3D registration. Mean angular errors in both planes remained below 3.0°. Cadavers had a mean age of 72.5 years and a mean body mass index of 22.2.
Conclusion:
AR-guided navigation enables accurate angular trajectory guidance for disc space and SIJ targeting. Comparable accuracy between intraoperative CT and 2D-3D registration suggests that 2D-3D AR workflows may reduce radiation exposure and operative time while maintaining precision.
Clinical Relevance:
AR navigation may improve surgical workflow by providing real-time 3D visualization while reducing reliance on intraoperative CT, potentially decreasing radiation exposure and operative time without compromising accuracy in complex spine procedures.
Level Of Evidence:
Level 5 (cadaveric study).
