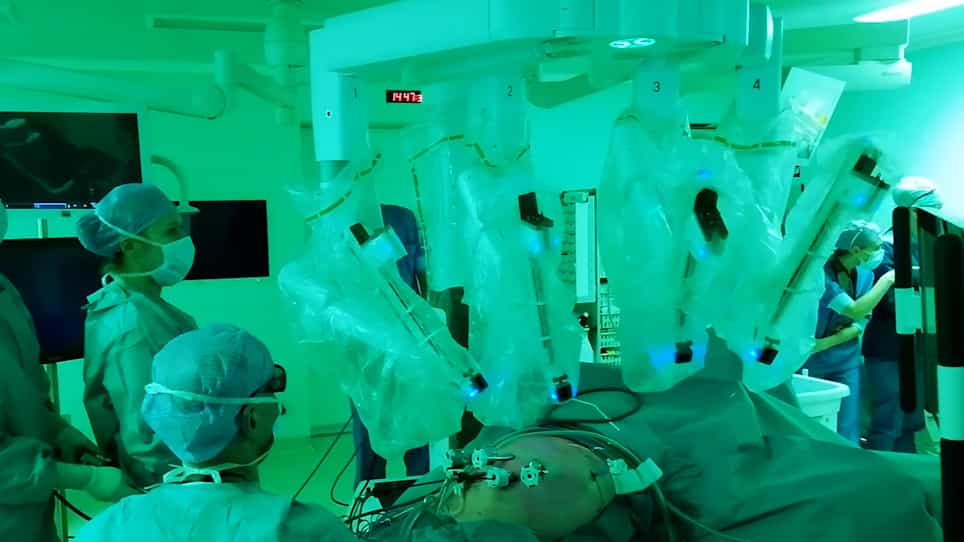
Related Experiment Video
Updated: Oct 9, 2026
Technical Detail for Robot Assisted Pancreaticoduodenectomy
Published on: September 28, 2019
Learning curve of robotic pancreaticoduodenectomy: a CUSUM and risk-adjusted CUSUM analysis of 120 consecutive cases
Giuseppe Quero1,2, Matteo Aulicino1, Lodovica Langellotti1
1Pancreatic Surgery Unit, Department of Surgery, Gemelli Pancreatic Center, CRMPG (Advanced Pancreatic Research Center), Fondazione Policlinico Universitario "Agostino Gemelli" IRCCS, Largo Agostino Gemelli, 8, 00168, Rome, Italy.

Background:
Robotic pancreaticoduodenectomy (RPD) has progressively gained acceptance in high-volume pancreatic surgery centers. However, the learning curve associated with implementation of an RPD program remains incompletely defined. This study aimed to evaluate the learning curve of RPD using cumulative sum (CUSUM) and risk-adjusted cumulative sum (RA-CUSUM) analyses.
Methods:
A retrospective analysis of a prospectively maintained database including 120 consecutive patients undergoing RPD between January 2023 and April 2026 was performed. CUSUM analysis of operative time and RA-CUSUM analysis of major postoperative morbidity (Clavien-Dindo grade ≥III) were used to assess operative efficiency and postoperative safety, respectively. Outcomes were compared before and after the exploratory RA-CUSUM-derived learning curve transition point.
Results:
Median operative time was 625 min (IQR 568-706), whereas major postoperative morbidity occurred in 30 patients (25%). CUSUM analysis identified an inflection point at case 49, demonstrating progressive improvement in operative efficiency. Linear regression analysis confirmed a significant reduction in operative time across consecutive procedures (regression coefficient - 1.68 min/case; R2 = 0.3884; p < 0.001). RA-CUSUM analysis identified an exploratory change point at case 56, after which a sustained downward trajectory of the risk-adjusted morbidity curve was observed. Following the exploratory change point, operative time significantly decreased from 706 to 574 min (p < 0.001), whereas major morbidity significantly decreased from 39.2 to 12.5% (p < 0.001). Post-pancreatectomy hemorrhage also significantly decreased (7.1% vs 0%, p = 0.04). Exploratory modeling demonstrated a significant progressive reduction in the predicted risk of major postoperative morbidity with increasing cumulative surgical experience (p = 0.0056). Oncological outcomes remained stable throughout the learning process.
Conclusions:
RPD demonstrates a measurable learning curve characterized by progressive improvement in operative efficiency and postoperative safety. These findings suggest that postoperative safety may provide a more clinically meaningful framework than operative time alone for describing the evolution of the learning curve.