Related Experiment Video
Updated: Oct 9, 2026


Non-fluoroscopic Catheter Tracking for Fluoroscopy Reduction in Interventional Electrophysiology
Published on: May 26, 2015
Serial Artificial Intelligence ECG-Derived Atrial Fibrillation Probability and Recurrence Risk After Pulsed Field
Mayank Sardana1, Juan F Rodriguez-Riascos1, Hema S Vemulapalli1,2
1Department of Cardiovascular Medicine, Mayo Clinic, AZ (M.S., J.F.R.-R., H.S.V., J.K., K.S.).

Background:
Pulsed field ablation is now widely used for atrial fibrillation (AF) ablation, but atrial tachyarrhythmia recurrence remains common and postablation risk tools are limited. We assessed whether a validated sinus‑rhythm artificial intelligence- enabled ECG AF probability score, and its early postablation change, predicts recurrence after pulsed field ablation.
Methods:
We studied consecutive patients undergoing index pulsed field ablation across 3 Mayo Clinic sites (February 2024-March 2025) with ≥1 sinus‑rhythm ECG within 180 days preprocedure. Baseline artificial intelligence-enabled ECG AF score (range 0-1) was the mean across baseline ECGs. Recovery indices (RI30/60/90), defined as mean postprocedure artificial intelligence-enabled ECG score within days 1-30/60/90 minus baseline, predicted post‑blanking recurrence using corresponding 30‑, 60‑, and 90‑day blanking windows. The primary outcome was time to first documented AF/atrial flutter/atrial tachycardia episode >30 seconds, ascertained via clinic ECGs, ambulatory monitoring, and device interrogations. Cox regression adjusted for prespecified clinical and echocardiographic covariates assessed associations; Harrell C‑statistic quantified discrimination.
Results:
Among 1052 patients (67±10 years; 33% women), median baseline score was 0.35; 320 (30%) recurred over 188 days. Higher baseline score independently predicted recurrence (hazard ratio per 0.1 increase, 1.08 [95% CI, 1.03-1.14]). Scores rose on day 0 after ablation, then declined over subsequent weeks, with persistently higher, less‑improving trajectories among patients who recurred (time×recurrence interaction P<0.001). Day 0 score was not independently associated with recurrence after adjustment. Attenuated early recovery (higher recovery index) was independently associated with recurrence, most robustly for RI-90 (hazard ratio per 0.1 increase, 1.15 [95% CI, 1.07-1.24]), and improved discrimination beyond baseline and covariates (C‑statistic, 0.63-0.67; ΔC=0.04). Findings were consistent in a historical thermal ablation cohort.
Conclusions:
Baseline and early postablation dynamics of a sinus‑rhythm artificial intelligence-enabled ECG AF probability score are associated with pulsed field ablation recurrence and may aid multivariable risk stratification; prospective validation is warranted.


Related Concept Videos
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:23
Cardiopulmonary Resuscitation III: AED Use
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
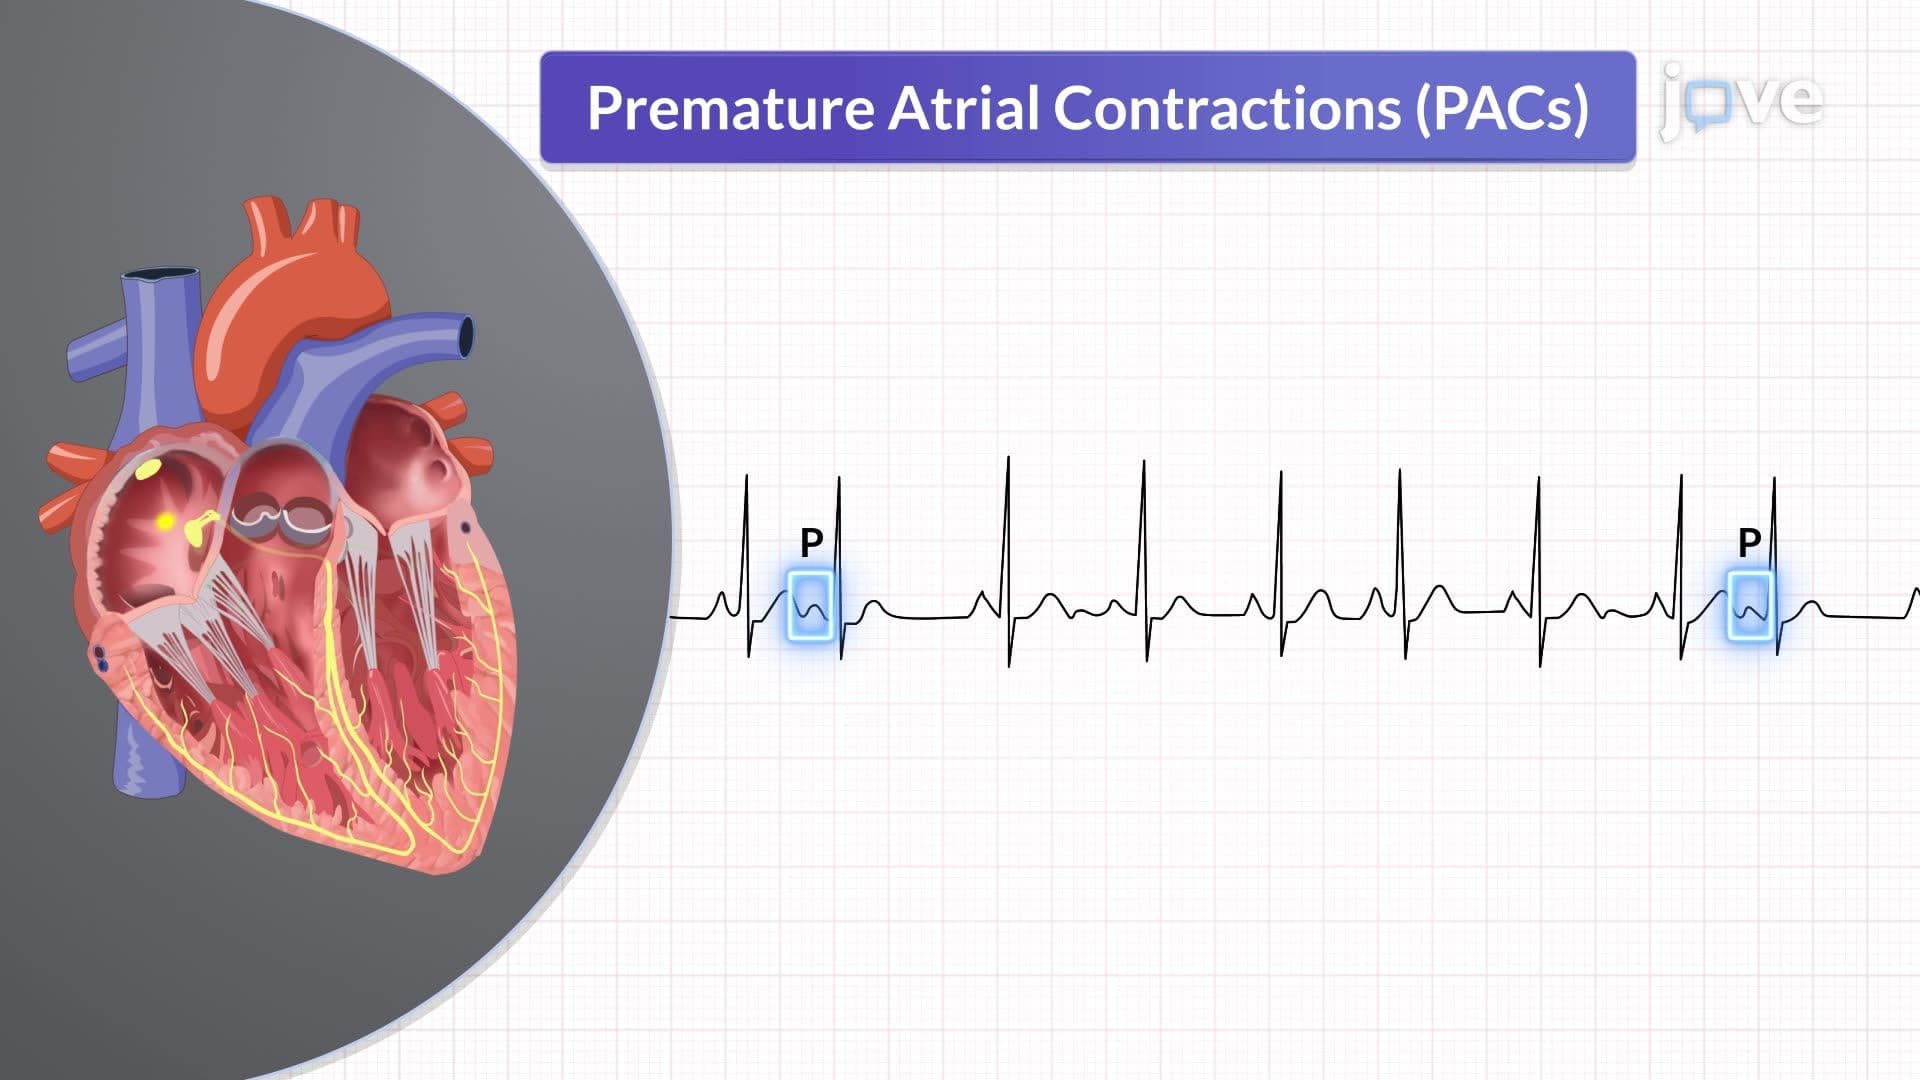 01:29
Dysrhythmias III: Characteristics of Dysrhythmias