Related Experiment Video
Updated: Oct 9, 2026
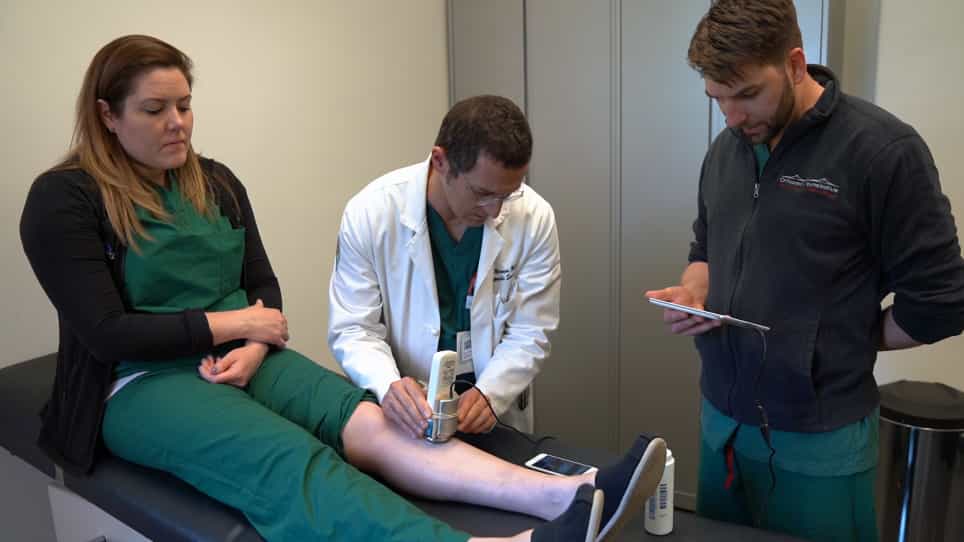

A Novel Non-invasive Method for the Detection of Elevated Intra-compartmental Pressures of the Leg
Published on: May 31, 2019
Clinical phenotypes and risk stratification for limb-threatening outcomes in acute compartment syndrome: a
Hong Cheng1, Sitan Feng2,3, Weiming Tan4
1Department of Trauma Orthopaedics and Hand Surgery, Nanxishan Hospital of Guangxi Zhuang Autonomous Region (The Second People's Hospital of Guangxi Zhuang Autonomous Region), Guilin, China.

Background:
Acute compartment syndrome (ACS) is a time-sensitive limb-threatening condition that may progress to irreversible muscle necrosis and amputation. Clinical heterogeneity complicates early assessment of severe limb outcomes. This study aimed to identify clinically interpretable phenotypic patterns and evaluate whether phenotype information improves risk stratification in ACS.
Methods:
This multicenter retrospective cohort study included 1,475 patients with ACS from five medical centers, comprising a training cohort (n = 1,088) and a hospital-independent external validation cohort (n = 387). Data-driven clustering of 115 routinely collected clinical variables was performed without outcome information to identify exploratory phenotypes. Risk models for muscle necrosis and amputation were then developed using clinical variables alone or combined with phenotype information. Performance was evaluated by discrimination, calibration, decision-curve analysis, external validation, and predictor-contribution analysis.
Results:
Five exploratory clinical phenotypes were identified, reflecting distinct patterns of injury characteristics, ischemic manifestations, tissue-injury burden, and systemic compromise. In external validation, phenotype information provided little additional discrimination for muscle necrosis (ROC-AUC 0.989 for both models). For amputation, the phenotype-informed model showed higher discrimination than the base model (ROC-AUC 0.959 vs. 0.937; PR-AUC 0.763 vs. 0.681) and a lower Brier score (0.105 vs. 0.119). Risk estimates were predominantly informed by markers of muscle injury, renal function, and systemic severity.
Conclusion:
ACS comprises clinically heterogeneous patterns associated with different risks of severe limb outcomes. Phenotype information provided additional risk-stratification value for amputation but not for muscle necrosis. These phenotypes should be regarded as exploratory clinical patterns rather than definitive biological subtypes. Prospective validation and recalibration are required before individualized risk estimates can be considered for clinical use.
