Related Experiment Video
Updated: Oct 9, 2026
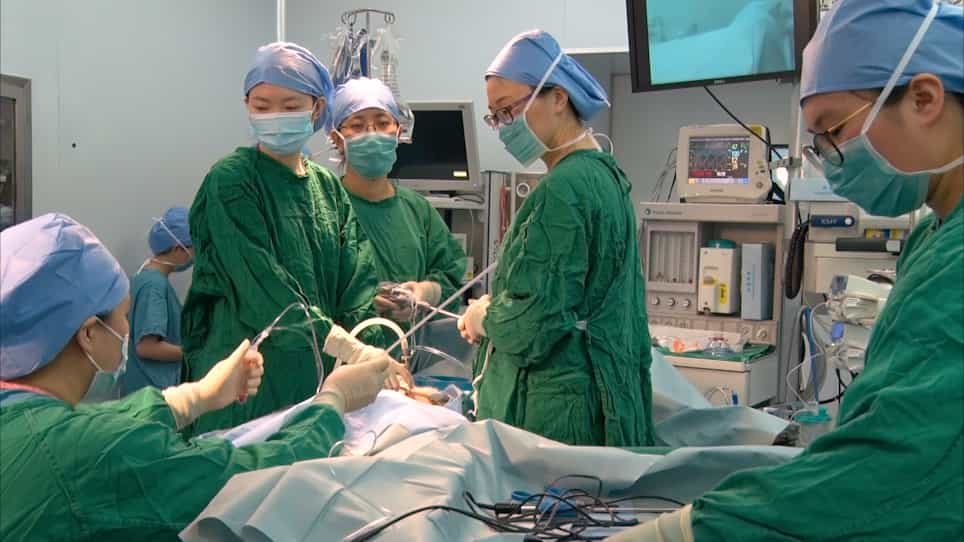

OP-IVM: Combining In vitro Maturation after Oocyte Retrieval with Gynecological Surgery
Published on: May 9, 2021
Quantity down, quality preserved: a continuous HOMA-IR analysis of IVF/ICSI outcomes in PMOS patients
Huiyi Xie1, Jingu Li1, Yunni Cai1
1Department of Reproductive Medicine, Quanzhou Women and Children's Hospital (Quanzhou Children's Hospital), Quanzhou, Fujian, China.

Objective:
To evaluate the dose-response relationship between HOMA-IR as a continuous variable and embryo development outcomes in fresh IVF/ICSI cycles of PMOS patients (formerly PCOS), distinguishing IR effects on oocyte yield (ovarian responsiveness) from effects on embryo developmental efficiency (per-oocyte conversion potential), and to evaluate differential IR impacts on cumulative implantation versus pregnancy maintenance.
Design:
Single-center retrospective cohort study of all fresh IVF/ICSI cycles from July 2022 to March 2026, comprising 3058 de-duplicated patients (2799 non-PMOS, 259 PMOS; PMOS-nonIR n=115, PMOS-IR n=144, cut-off ≥2.5). Spearman correlation and multivariable linear regression (adjusted for age, BMI, AMH) were used to evaluate the independent associations of HOMA-IR with oocyte maturation, fertilization, and embryo development at each stage.
Results:
Oocyte maturation rate showed no correlation with HOMA-IR (r=-0.014, P = 0.8178). HOMA-IR was negatively correlated with oocyte count (r=-0.226, P = 0.0002), and oocyte yield was significantly lower in PMOS-IR vs PMOS-nonIR. Transferable embryo and usable blastocyst counts were negatively associated with HOMA-IR, but transferable embryo rate showed no association with HOMA-IR (adjusted β=0.817, P = 0.3940), nor did blastocyst formation rate or usable blastocyst rate. Cumulative β-hCG positive and clinical pregnancy rates were significantly higher in PMOS-IR (85.4% and 81.9%) versus Non-PMOS (72.8% and 69.0%, P = 0.0024 and P = 0.0022), largely driven by greater transfer opportunity (97.9% vs 89.0%). By contrast, clinical pregnancy loss (no live birth among clinical pregnancies with a known outcome) showed a graded upward trend (13.5% vs 15.6% vs 17.2%), but the between-group difference was not statistically significant; owing to the limited number of loss events in the PMOS subgroups, this comparison should be interpreted with caution. Cumulative live birth rates did not differ significantly across groups (56.9% vs 56.5% vs 54.5%, P = 0.7853).
Conclusions:
In PMOS patients, IR exhibits multi-stage differential effects - impairing oocyte yield while preserving embryo developmental competence. Once oocytes are retrieved, their developmental efficiency is unaffected by IR status. Higher cumulative implantation in PMOS-IR was largely driven by greater transfer opportunity, whereas clinical pregnancy loss showed an upward trend without statistical significance, indicating that IR-related reproductive impairment primarily involves oocyte yield and transfer opportunity, while post-implantation pregnancy maintenance merits further evaluation. This warrants prospective validation. HOMA-IR should be integrated into pre-IVF ovarian response stratification but not used to predict embryo developmental competence.