Related Experiment Video
Updated: Oct 10, 2026
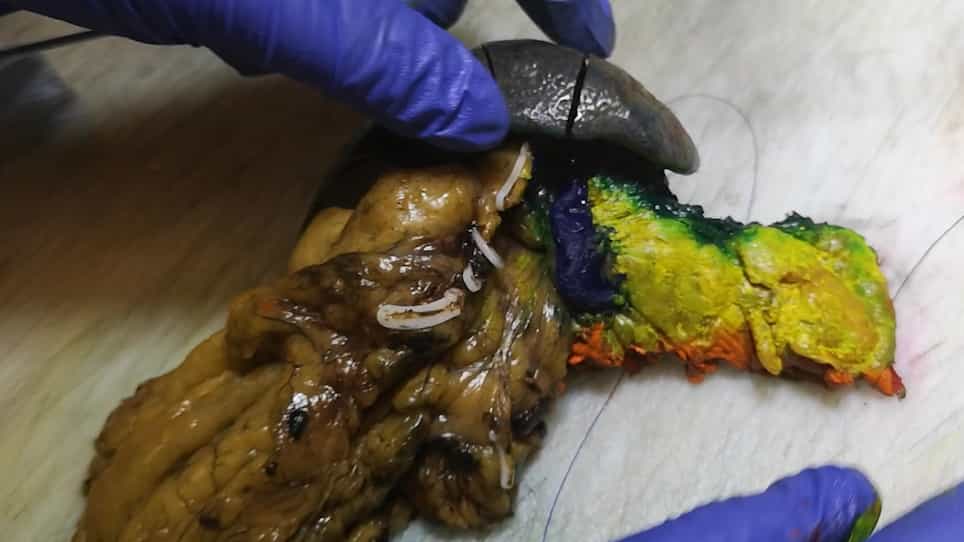
DIPLOMA Approach for Standardized Pathology Assessment of Distal Pancreatectomy Specimens
Published on: February 1, 2020
Noninvasive microbiota-based diagnostic models for pancreatic ductal adenocarcinoma: a systematic review and
Liang Zhang1, Jian Liu1, Mengyao Pang1
1Department of Gastroenterology, Beijing Huaxin Hospital, The First Hospital of Tsinghua University, Beijing, China.

Background:
Due to delays in diagnosis, many patients with pancreatic ductal adenocarcinoma (PDAC) miss the window for curative interventions. The oral and gut microbiomes are attractive as noninvasive triage instruments; however, while the literature provides AUROC values, it has not established clinically useful thresholds.
Objective:
To systematically assess the diagnostic performance and clinical maturity of noninvasive microbiota-derived tools for identifying PDAC.
Methods:
Following PRISMA 2020 and PRISMA-DTA, we searched eight databases up to April 19, 2026, and conducted a targeted supplementary search on September 3, 2026. Risk of bias was assessed using PROBAST and QUADAS-2. The nine-row meta-analysis, which included approximations and correlated estimates, was exploratory.
Results:
The initial search and targeted supplementary search yielded 16 studies covering 21 sample-domain items; 20 model-based records constituted the units of analysis for the risk-of-bias assessment. Fifty-one AUROC estimates formed a separate list of discrimination estimates. Six-row fixed-threshold data from five studies constituted the primary descriptive core. Sensitivity ranged from 0.682 to 0.964, and specificity ranged from 0.667 to 0.963. The exploratory nine-row bivariate model yielded pooled sensitivity of 0.86 (95% CI 0.80-0.90) and specificity of 0.80 (95% CI 0.73-0.86). These nine rows represented seven studies; Li 2025 and Chen 2025b each provided a correlated row, so the pooled estimates were hypothesis-generating. The certainty of evidence was rated very low using an adapted, GRADE-informed appraisal. All model-based rows (20/20) were at high risk of bias in the PROBAST analysis domain and high overall risk on QUADAS-2. Although stool-based testing provided the clearest signal of external validation, benign pancreatic mimics remained underrepresented.
Conclusion:
Detecting PDAC via noninvasive microbiota classifiers carries a biologically plausible yet very low-certainty diagnostic signal. Current findings do not support stand-alone clinical deployment and support only exploratory adjunctive triage. Validating prospectively against benign pancreatic mimics is mandatory before routine clinical adoption.
Systematic Review Registration:
https://www.crd.york.ac.uk/PROSPERO/view/CRD420261370926, Identifier, CRD420261370926.
