Related Experiment Video
Updated: Oct 10, 2026
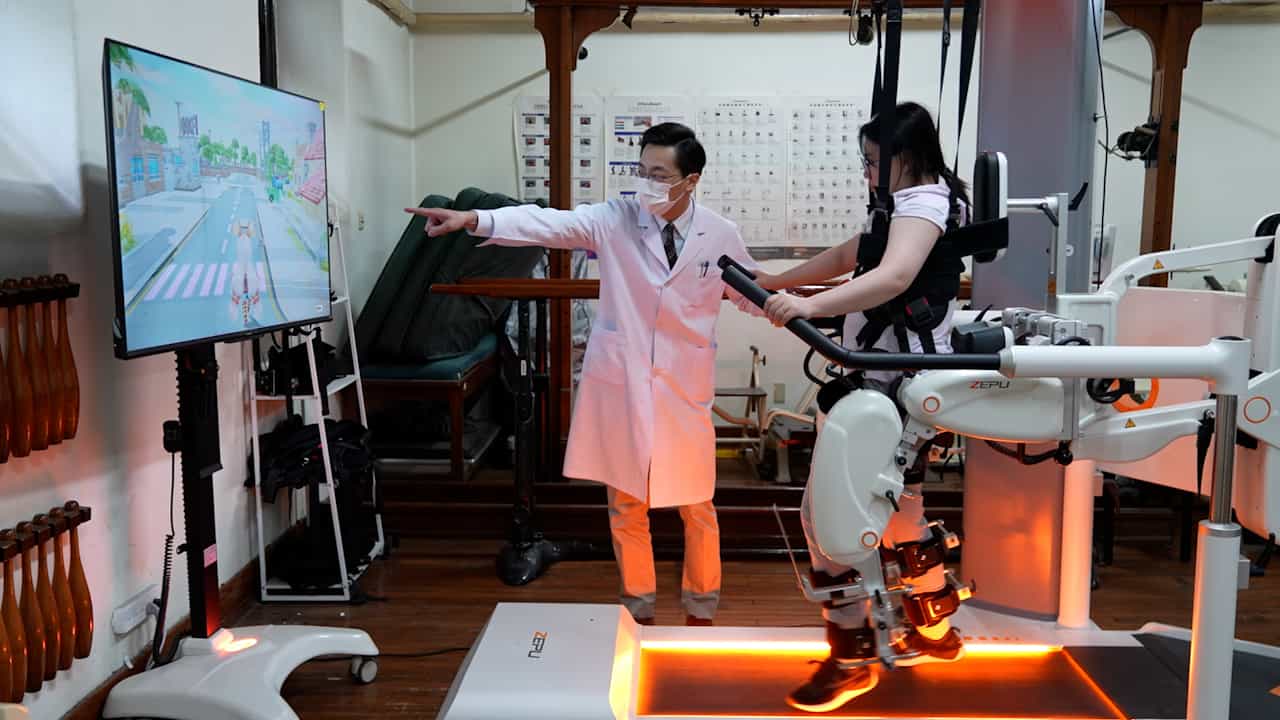

A Rehabilitation Program of Exoskeleton-assisted Body Weight-Supported Treadmill Training with Non-immersive Virtual Reality for Stroke Patients
Published on: May 16, 2025
Factors associated with exercise preferences and perceived barriers in individuals with chronic stroke: a
Humeyra Kiloatar1, Hilal Telli2, Aylin Aydogdu Delibay3
1Department of Physiotherapy and Rehabilitation, Faculty of Health Science, Kutahya Health Sciences University, Kutahya, Türkiye.

Objective:
This study aimed to comprehensively investigate psychophysical factors associated with exercise preferences and perceived exercise barriers in individuals with chronic stroke.
Methods:
This cross-sectional study included 110 participants with chronic stroke. Assessments included the Stroke Exercise Preference Inventory (SEPI), Exercise Benefits/Barriers Scale (EBBS), Tampa Scale for Kinesiophobia (TSK), Falls Efficacy Scale-International (FES-I), Hospital Anxiety and Depression Scale (HADS), Functional Independence Measure (FIM), and PainDETECT Questionnaire (PD-Q).
Results:
SEPI-Exercise preferences showed a weak negative correlation with TSK and FES-I, a moderate negative correlation with HADS-Depression, and a weak positive correlation with FIM (p < .05). SEPI-Barriers and EBBS-Barriers showed strong-to-moderate positive correlations with TSK, FES-I, and HADS-Anxiety, and a moderate negative correlation with FIM (p < .001). In multiple linear regression analyses, HADS-Depression was independentlyassociated withlower SEPI-Exercise Preferences scores (β = -0.440, p < .001; Adjusted R2 = 0.116). In the SEPI-Exercise Barriers Model, TSK (β = 0.383), FES-I (β = 0.374), and HADS-Anxiety (β = 0.300) demonstrated significant positive associations, while HADS-Depression (β = -0.175) showed a small negative association (all p < .05; Adjusted R2 = 0.548). Finally, TSK was significantly and positively associated with EBBS-Barriers (β:0.326; Adjusted R2: 0.358).
Conclusion:
Depression may influence exercise preferences, whereas kinesiophobia, fear of falling, and anxiety may contribute to perceived exercise barriers after stroke. Addressing these psychological factors alongside physical limitations may support long-term exercise adherence.