Related Experiment Video
Updated: Oct 10, 2026
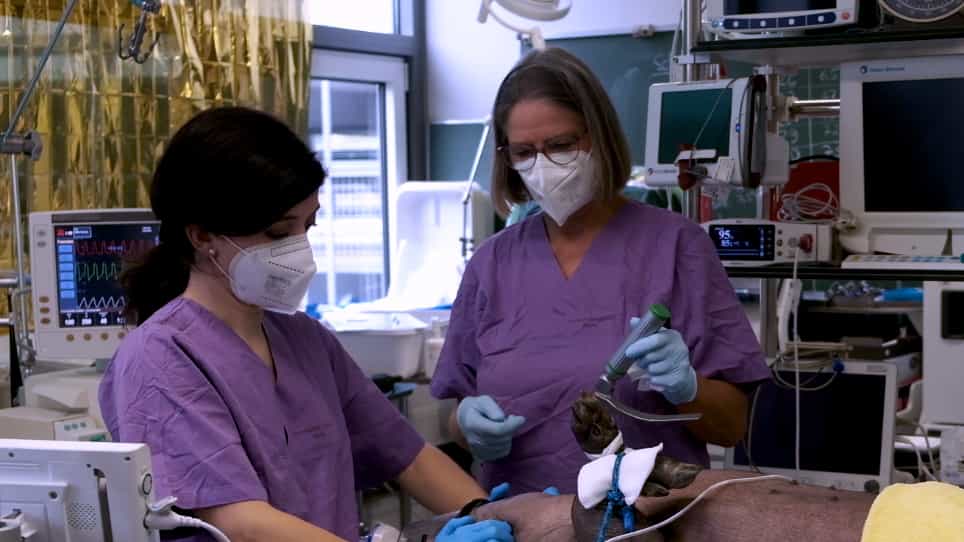

Endotracheal Intubation Using a Flexible Intubation Endoscope as a Standardized Model for Safe Airway Management in Swine
Published on: August 25, 2022
Videolaryngoscopy versus direct laryngoscopy for endotracheal intubation of obese patients: a prospective randomized
P Maciejewski1, T Składzień1, Ł Tabin1
1Department of Intensive Interdisciplinary Care, Collegium Medicum, Jagiellonian University, Cracow, Poland.

Background:
Obese patients present challenging airway conditions, including reduced functional residual capacity and rapid desaturation during apnoea. Videolaryngoscopy improves glottic visualisation, but evidence comparing it with direct laryngoscopy in bariatric patients managed by experienced anaesthesiologists remains limited. We conducted a prospective randomised trial comparing these techniques.
Methods:
256 adult patients (BMI > 35 kg/m²) were randomised to intubation with a standard Macintosh laryngoscope or a hyperangulated videolaryngoscope (INSIGHT iS3-L), with a stylet routinely used in the videolaryngoscopy group. All received a standardised opioid-free anaesthesia protocol. The primary outcome was time to intubation (TOF = 0 to capnographic confirmation). Secondary outcomes included first-attempt success rate, number of intubation attempts, and bougie use.
Results:
Overall intubation success was achieved in all 256 patients; however, 4 patients (3.1%) in the Macintosh group required conversion to videolaryngoscopy as rescue. Median time to intubation was significantly shorter in the Macintosh group (35 [IQR 30-47.5] s vs 46 [IQR 35-62] s; p < 0.001), a difference partly attributable to operator familiarity and unlikely to be clinically relevant given comparable safety outcomes. No significant differences were observed in first-attempt success, intubation attempts, or bougie use. No airway injury or oxygen desaturation below 90% occurred; one prolonged Macintosh-group intubation was associated with peri-intubation bradycardia and hypotension. Neither Mallampati classification nor neck circumference > 43-44 cm reliably predicted intubation difficulty.
Conclusions:
In this single-centre study of selected obese patients managed by experienced anaesthesiologists, direct laryngoscopy achieved shorter intubation times than a hyperangulated videolaryngoscope with comparable safety outcomes; however, the 11-second difference in median times is unlikely to be clinically relevant. The 3.1% conversion rate underscores that videolaryngoscopy must always be immediately available. Videolaryngoscopy remains essential in anticipated difficult airway management.


Related Concept Videos
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.