Related Experiment Video
Updated: Oct 10, 2026
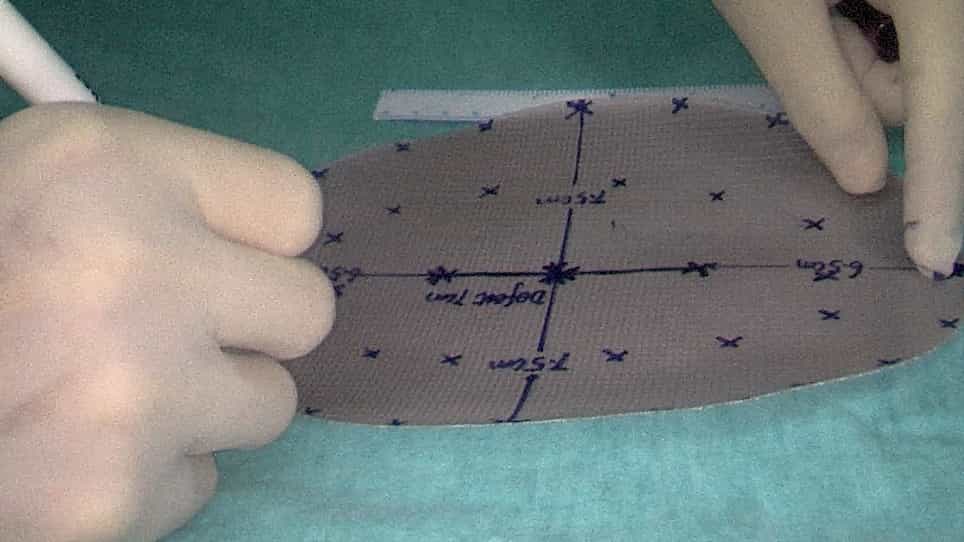

Application of a New Mesh Fixation Method in Laparoscopic Incisional Hernia Repair
Published on: December 23, 2022
Primary defect closure in minimally invasive direct inguinal hernia repair: a propensity-weighted analysis
Claudia Theis1, Victor Andrade Nunes2, Bernardo Fontel Pompeu3
1Division of General Surgery, Department of Surgery, University of North Carolina at Chapel Hill, Chapel Hill, NC, USA. claudia_theis@med.unc.edu.

Background:
The benefit of defect closure during minimally invasive repair of direct inguinal hernias remains uncertain. Prior studies have reported conflicting findings and often lacked adequate control for confounding.
Methods:
This retrospective cohort study included adult patients undergoing elective, unilateral, laparoscopic or robotic repair of direct inguinal hernias with complete 30-day follow-up in the Abdominal Core Health Quality Collaborative registry. Inverse probability of treatment weighting adjusted for age, BMI, ASA class, smoking, anticoagulation, diabetes, hypertension, immunosuppressant use, prior pelvic operation, recurrent hernia, direct hernia size, and prior mesh. The primary outcome was 30-day surgical site occurrence (SSO). Secondary outcomes included 30-day readmission, reoperation, and recurrence. A prespecified robotic subgroup analysis was performed.
Results:
A total of 4,209 patients were included. Closure was associated with lower SSO rate (3.6% vs 6.2%, p = 0.034) but higher 30-day cardiac readmissions (2.2% vs 0.3%, p < 0.001), driven by 3 versus 1 events, while other causes were infrequent and similar between groups. In the robotic subgroup (n = 2,171), the wound benefit lost statistical significance (SSO 3.9% vs 5.1%, p = 0.330), whereas cardiac readmissions remained elevated (2.1% vs 0.3%, p = 0.001). Closure clustered with distinct operative practices, including more frequent use of self-fixating mesh (60% vs 38%, p < 0.001), TAP blocks under direct visualization (46% vs 9.9%, p < 0.001), and shorter operative times (62% vs 51% completed in < 60 min, p = 0.001).
Conclusion:
Direct defect closure was associated with a reduction in early wound complications and higher 30-day cardiac readmissions. Given the very small absolute number of cardiac readmissions (3 vs 1) that are likely unrelated to defect closure, these findings support selective use of direct defect closure, particularly in patients with larger medial defects or higher wound complication risk. Randomized trials with standardized operative protocols are still needed to confirm our findings.
