Related Experiment Video
Updated: Oct 10, 2026
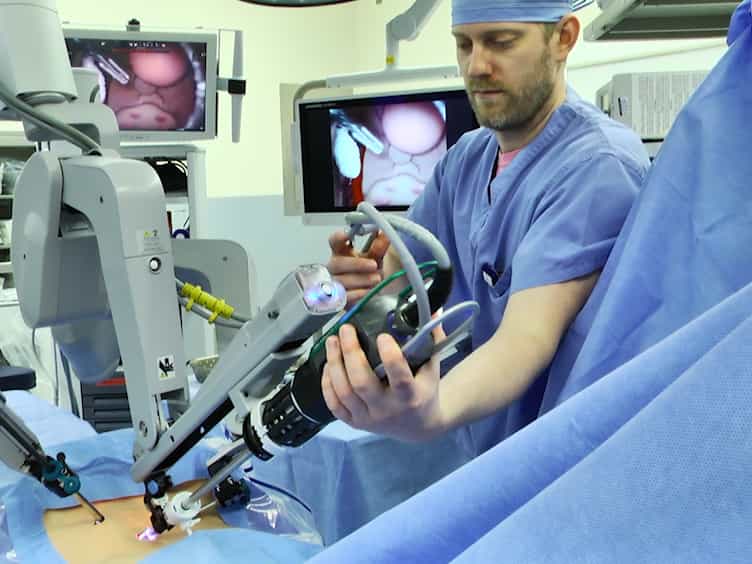

Emergency Undocking in Robotic Surgery: A Simulation Curriculum
Published on: May 20, 2018
Reengineering the Concept of Emergency Care
1Department of Emergency Medicine, University of Virginia, Charlottesville, Virginia, USA.

Abstract:
Emergency departments (EDs) absorb most acute unscheduled care (AUC) in the United States. Routing all of this care through one high-intensity system serves no one well: crowding delays care for time-critical patients; visits that turn on evaluation and coordination, and routine and chronic care defined by longitudinal needs, are delivered episodically and at high cost in a setting built for resuscitation and stabilization; and clinicians trained for emergencies spend much of their time on work the category does not fit. I argue that this is not only a capacity or workflow problem but a conceptual one. In practice, "emergency care" is defined by arrival: crossing the ED threshold, not clinical risk, triggers the legal duties, insurance protections, and workflows attached to the label. This was no one's mistake; routing everything through the one door always open was a rational adaptation to a fragmented system. But the adaptation no longer merely persists; it forecloses alternatives. Using conceptual engineering, I trace how history, regulation, payment, public scripts, and lexical entrenchment stabilize this system, and situate it against the social drivers that make ED-as-default ethically necessary and operationally costly. I then propose an ameliorated concept of emergency care: a risk- and time-sensitive, expert-mediated, priority-conferring subset of AUC, determined by structured triage wherever it occurs. Because a definition changes nothing by itself, I outline a phased implementation pathway, show how it applies across delivery settings, including rural and safety-net systems where the ED should remain the local acute care hub, and describe the workforce implications for emergency medicine. The choice posed to the specialty is whether to keep treating crowding, mismatched care, and clinician dissonance as operational problems to optimize within the ED, or to recognize them as properties of what we mean by emergency care and of the system that enacts it.

Related Concept Videos
 01:30
Methods of Documentation VII: EMR
 01:30
Specialized Care Centers and Settings-II
Rural health centers are specialized care facilities in remote locations with very few medical personnel. The primary care providers who run the centers are mostly Registered Nurse Practitioners. Here, emergency treatment is provided to critically ill or injured patients before they are transferred to the closest hospital. Fortunately, due to advancement in technology, many rural healthcare facilities and professionals have easy access to diagnostic and treatment...
 01:26
Traditional Level Of Health Care System
The preventive healthcare service includes tests for screening. Preventive health care services include identifying and reducing disease risk...
 01:11
Secondary Healthcare System
 01:29
Issues And Trends In Healthcare Delivery System
Cost Containment
Payment for healthcare services has historically promoted adoption of costly and often unnecessary or inefficient...
 01:13
Patient-centered Care