Related Experiment Video
Updated: Oct 11, 2026
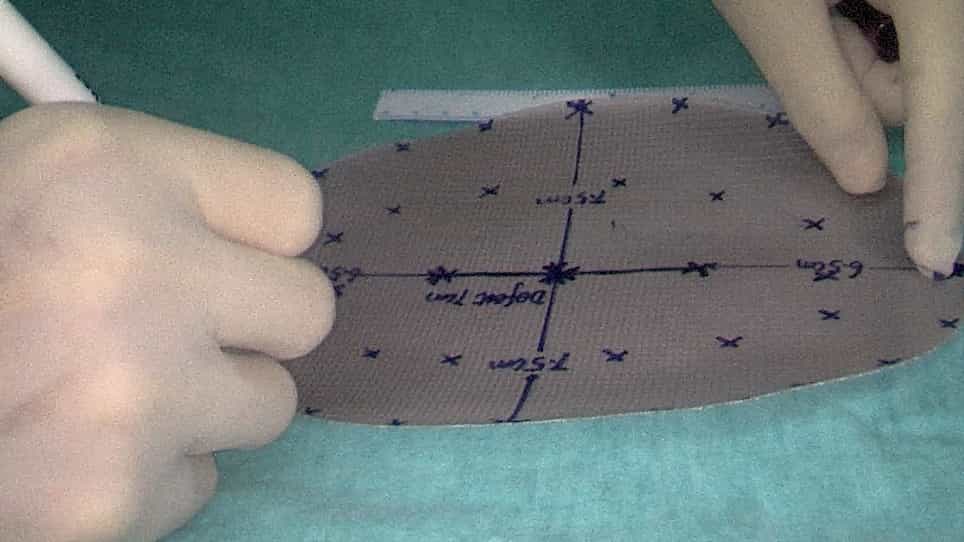

Application of a New Mesh Fixation Method in Laparoscopic Incisional Hernia Repair
Published on: December 23, 2022
Fragility of randomized clinical trials comparing surgical approaches for inguinal hernia repair: a systematic review
Maria Clara Morais1, Denise Padilha Abs de Almeida2, Beatriz Laus Pereira Lima3
1Department of Surgery, Lenox Hill Hospital, New York, NY, USA.

Introduction:
Randomized clinical trials (RCTs) remain the reference standard for estimating causal effects of surgical interventions when appropriately designed and conducted. However, P values alone do not describe how sensitive a dichotomous statistical-significance classification is to small changes in outcome counts. The Fragility Index (FI) and Reverse Fragility Index (RFI) are post hoc descriptive metrics that quantify the number of outcome-status changes required to alter statistical significance. This study aimed to evaluate FI/RFI for inguinal hernia repair (IHR) RCT findings, assess individual complication endpoints, and examine associations with sample size and conflict-of-interest reporting.
Methods:
Embase, PubMed, LILACS, and ClinicalTrials.gov were searched through June 2025 for RCTs comparing open, laparoscopic, or robotic inguinal hernia repair with dichotomous primary outcomes. FI, RFI, and sample-size-adjusted quotients were calculated from reconstructed 2 × 2 tables using two-sided Fisher exact tests. Individual complications and associations with trial characteristics were analyzed.
Results:
Forty-two RCTs comprising 14,505 patients and 44 primary comparisons were included; all eligible comparisons evaluated laparoscopic versus open repair. Twelve comparisons were significant, with a median FI of 4 (IQR, 3-5.25); 4 (33.3%) had an FI of 3 or less. Among 31 nonsignificant comparisons, the median RFI was 5 (IQR, 3.5-6.5). All 4 significant individual-complication results had an FI of 3 or less (median, 1). Significance classification differed between reported and recalculated P values in 4 of 78 extracted comparisons. FI was not significantly correlated with sample size.
Conclusions:
Randomized trials remain central to comparative evidence in inguinal hernia repair. FI and RFI provide complementary post hoc context regarding how many outcome-status changes would alter a dichotomous significance classification and should be interpreted alongside prespecified trial design, effect estimates, confidence intervals, P values, sample size, missing data, and clinical relevance.