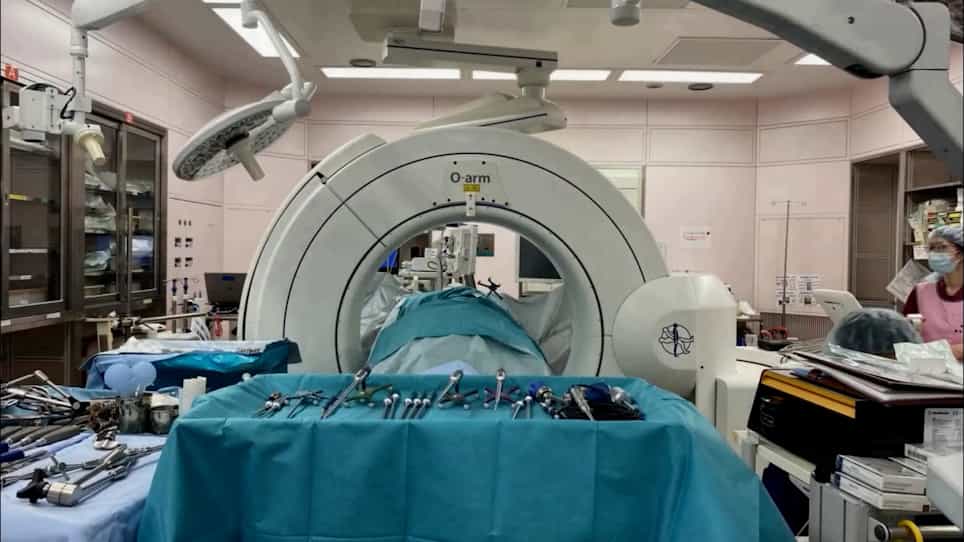
Related Experiment Video
Updated: Oct 11, 2026


Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Achieving "ideal" sagittal alignment does not influence HRQoL outcomes 5 years following PSF for lenke 1 AIS
K Aaron Shaw1,2, Michael P Kelly3, Tracey Bryan3
1Spine Division, Department of Orthopedic Surgery, Children's Mercy Kansas City, Kansas City, MO, USA. Shaw.aaron82@gmail.com.

Introduction:
Previous studies have emphasized the importance of thoracic kyphosis (TK) restoration and sagittal alignment for long-term outcomes following posterior spinal fusion (PSF) for adolescent idiopathic scoliosis (AIS). Although various equations have been introduced to predict the ideal regional alignment of the thoracic or lumbar spine, no study has validated these equations or investigated the influence of achieving these patient-specific ideal regional parameters on patient-reported health-related quality of life (HRQoL) outcomes following PSF for AIS.
Methods:
A retrospective cohort study of a multicenter AIS database identifying patients with PSF with 5-year follow-up was performed. Patients with Lenke 1 curves with complete radiographic records, focusing on sagittal alignment parameters for lumbar lordosis (LL), TK (T2-12), sagittal vertical alignment (SVA), and patient-reported outcomes scores (SRS-22) at preoperative and 5-year follow-up timepoints were included for analysis. "Ideal" TK was calculated using pelvic incidence (PI) and "ideal" lumbar alignment was defined using two criteria. Patients were then subdivided based on whether ideal regional alignment was achieved at 5 years follow-up. SRS-22 total scores were subdivided into quintiles with the lowest 40% of patients (score ≤ 4.3) used to define less optimal outcome (LOO).
Results:
A total of 991 patients were identified, with 192 patients meeting inclusion criteria (mean 14.5 ± 2.1 years, 88.5% female). The mean "ideal" TK was calculated at 37.6 ± 5.7° (range 23.9°-51.8°) with a mean measured preoperative TK of 27.0 ± 11.8°). Following surgery, there was a significant increase in TK (P < 0.001) with 62 patients (32.3%) achieving "ideal" TK (Table 1). Nonetheless, achieving ideal TK demonstrated no significant impact on SRS-22 domain scores. Additionally, there was no association between achieving ideal TK and the development of LOO (33.9 vs 42.3%; P = 0.16), nor were other sagittal radiographic parameters. Preoperative SRS-22 scores primarily impacted 5-year SRS domain scores and change in score from preoperative values.
Conclusion:
In a cohort of patients undergoing PSF for Lenke 1 AIS, the pursuit of ideal region-specific alignment parameters did not influence patient-reported outcome measures 5 years following surgery. While this may indicate that younger patients are unaffected by less than "ideal" sagittal alignment, it is also possible that the current definition of "ideal" needs reconsideration. This may indicate the need for an updated sagittal plane assessment in AIS, searching beyond regional measures of sagittal curvature magnitude to better understand the sagittal plane distribution and shape as it relates to longer term outcomes.