Related Experiment Videos
A Microsimulation of Eligibility for Cardiorenal Combination Treatment and Potential Deaths Averted
Massimo Nardone1,2, Labib Faruque1,2, Lisa Dubrofsky3
1University Health Network, Toronto, Ontario, Canada.

Background:
Clinical guidelines recommend combined use of renin-angiotensin system inhibitors (RASi), sodium-glucose cotransporter-2 inhibitors (SGLT2i), glucagon-like peptide-1 receptor agonists (GLP1RA) and nonsteroidal mineralocorticoid receptor antagonists (nsMRA) to reduce cardiorenal risk. However, eligibility for combination treatment and the potential effects of implementation on preventing mortality remain unclear.
Methods:
We conducted a microsimulation study using data from the National Health and Nutrition Examination Survey (NHANES 2007-2016 and 2017-2020). The model incorporated acute treatment effects of RASi, SGLT2i, GLP1RA, and nsMRA on estimated glomerular filtration rate (eGFR), urine albumin-to-creatinine ratio (UACR), and serum potassium. Eligibility for combination treatment was assessed for each participant according to 73 clinical practice guideline recommendations and inclusion criteria from recently published clinical trials. Primary outcomes included: 1) the percentage of participants eligible for single or combination treatment with RASi, SGLT2i, GLP1RA, and nsMRA, and 2) the projected potential number of annually averted all-cause and cardiovascular deaths.
Results:
Of 8,152 adults, 15% had type 2 diabetes (DM), 14% had chronic kidney disease (CKD) and 5% had DM and CKD (DKD). Among all U.S. adults, 19% were treated with RASi, 1% with SGLT2i, 1% with GLP1RA and none with nsMRA. The dual-therapy associated with the highest eligibility was RASi+SGLT2i, with 15% of the U.S. population eligible (DM subgroup: 70%; CKD subgroup: 50%; DKD subgroup: 84%). The triple-therapy with the highest eligibility was RASi+SGLT2i+GLP1RA, with 11% overall eligibility (DM: 69%; CKD: 33%; DKD: 83%). Eligibility for quadruple-therapy was 4% overall (DM: 22%; CKD: 17%; DKD: 40%). Based on our microsimulation model, fewer individuals with diabetes were eligible for triple-therapy with RASi+SGLT2i+GLP1RA compared to dual-therapy with RASi+SGLT2i, but triple-therapy was projected to prevent 2-fold more potential all-cause and cardiovascular deaths versus dual-therapy.
Conclusions:
Under the assumptions of our microsimulation model, eligibility for combined treatment with cardiorenal protective therapies was prevalent, particularly in adults with type 2 diabetes and/or CKD.
Related Concept Videos
 01:30
Continuous Renal Replacement Therapy
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions
 01:25
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:06
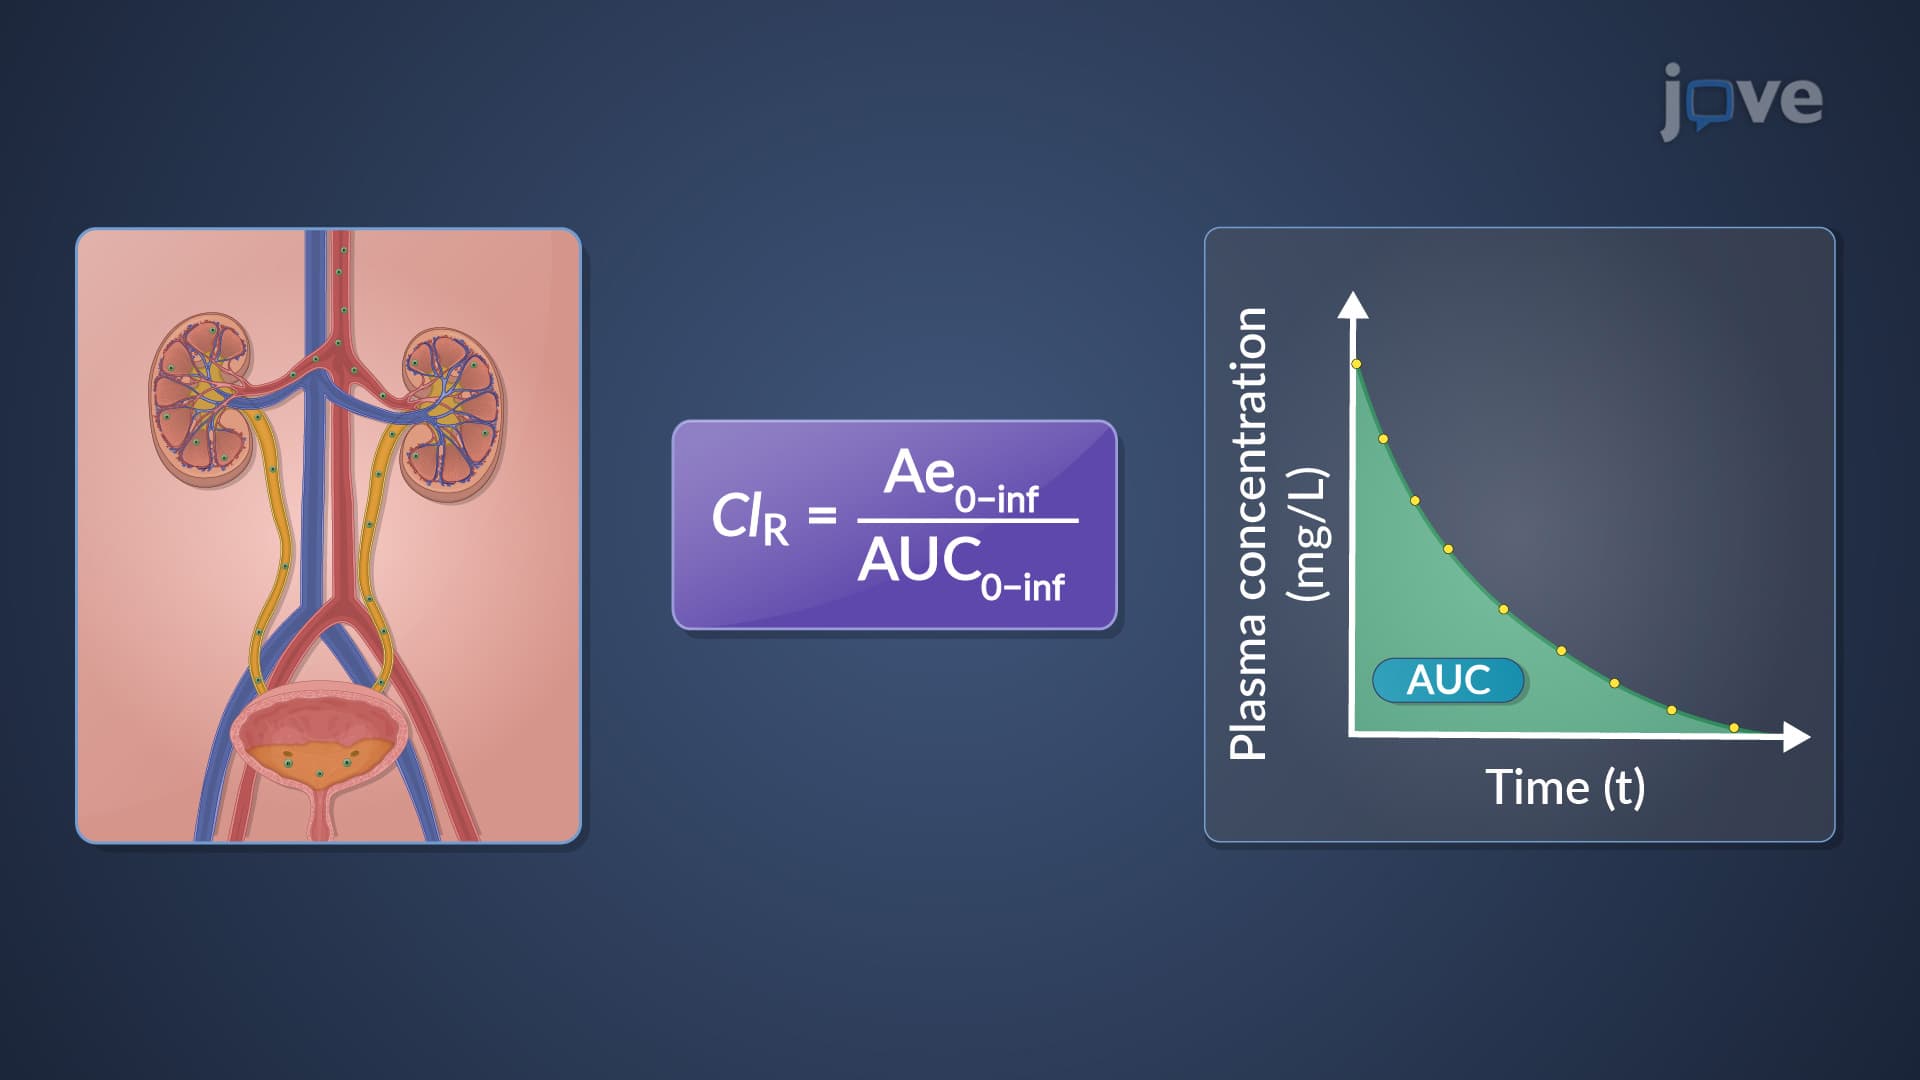
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:30
Heart Failure V: Medical Management