Related Experiment Videos
Infection Risk During Rituximab Therapy in Multiple Sclerosis: Effect of Dosing Interval and Age
Gorm Pihl-Jensen1, Maria Lie Selle2, Jan Harald Aarseth3,4
1Department of Neurology, Akershus University Hospital, Norway.

Background And Objectives:
Rituximab is the most frequently used disease-modifying therapy in multiple sclerosis (MS) in Norway. Extended dosing intervals beyond 6 months may offer the same efficacy, but the impact on infection risk is unclear. We examined how dosing frequency and age affect infection risk in rituximab-treated patients with MS.
Methods:
We conducted a nation-wide observational study linking compulsory Norwegian health registries with the Norwegian MS registry. Registry data captured hospital-treated infections and further infections requiring prescription treatment and/or physician contact with primary practice. Data were analyzed using the Prentice, Williams, and Peterson model with clustering on subject to account for longitudinal design, recurrent rituximab infusions and recurrent infection events while adjusting for relevant explanatory variables. Rituximab interval length was modelled as the number of rituximab infusions within 2 years. Age was grouped into 5-year intervals.
Results:
Among 3,410 patients (13,811 treatment episodes between 2010 and June 2022), 13,774 infections occurred, including 971 hospital-treated events. Compared with 4 infusions over 2 years (6-month intervals), extended dosing was associated with a lower risk of any infection (hazard ratio [HR] 0.90 [95% CI 0.82-0.99]) for 2 infusions; (HR 0.78 [95% CI 0.69-0.88] for 1 infusion). A reduced risk of hospital-treated infections was observed only for 1 infusion per 2 years relative to 4, and this was not robust in sensitivity analyses and not present for the subgroup of infections associated with overnight hospital stay. Patients ≥60 years had a significantly higher risk of hospital-treated infections (HR 1.36 [95% CI 1.07-1.71]).
Discussion:
Extended rituximab intervals are associated with reduced overall infection risk, but the benefit for hospital-treated infections is limited. Age ≥60 years independently increases the risk of hospital-treated infections. These findings support cautious interval extension and careful risk-benefit assessment in older patients.
Related Concept Videos
 01:24
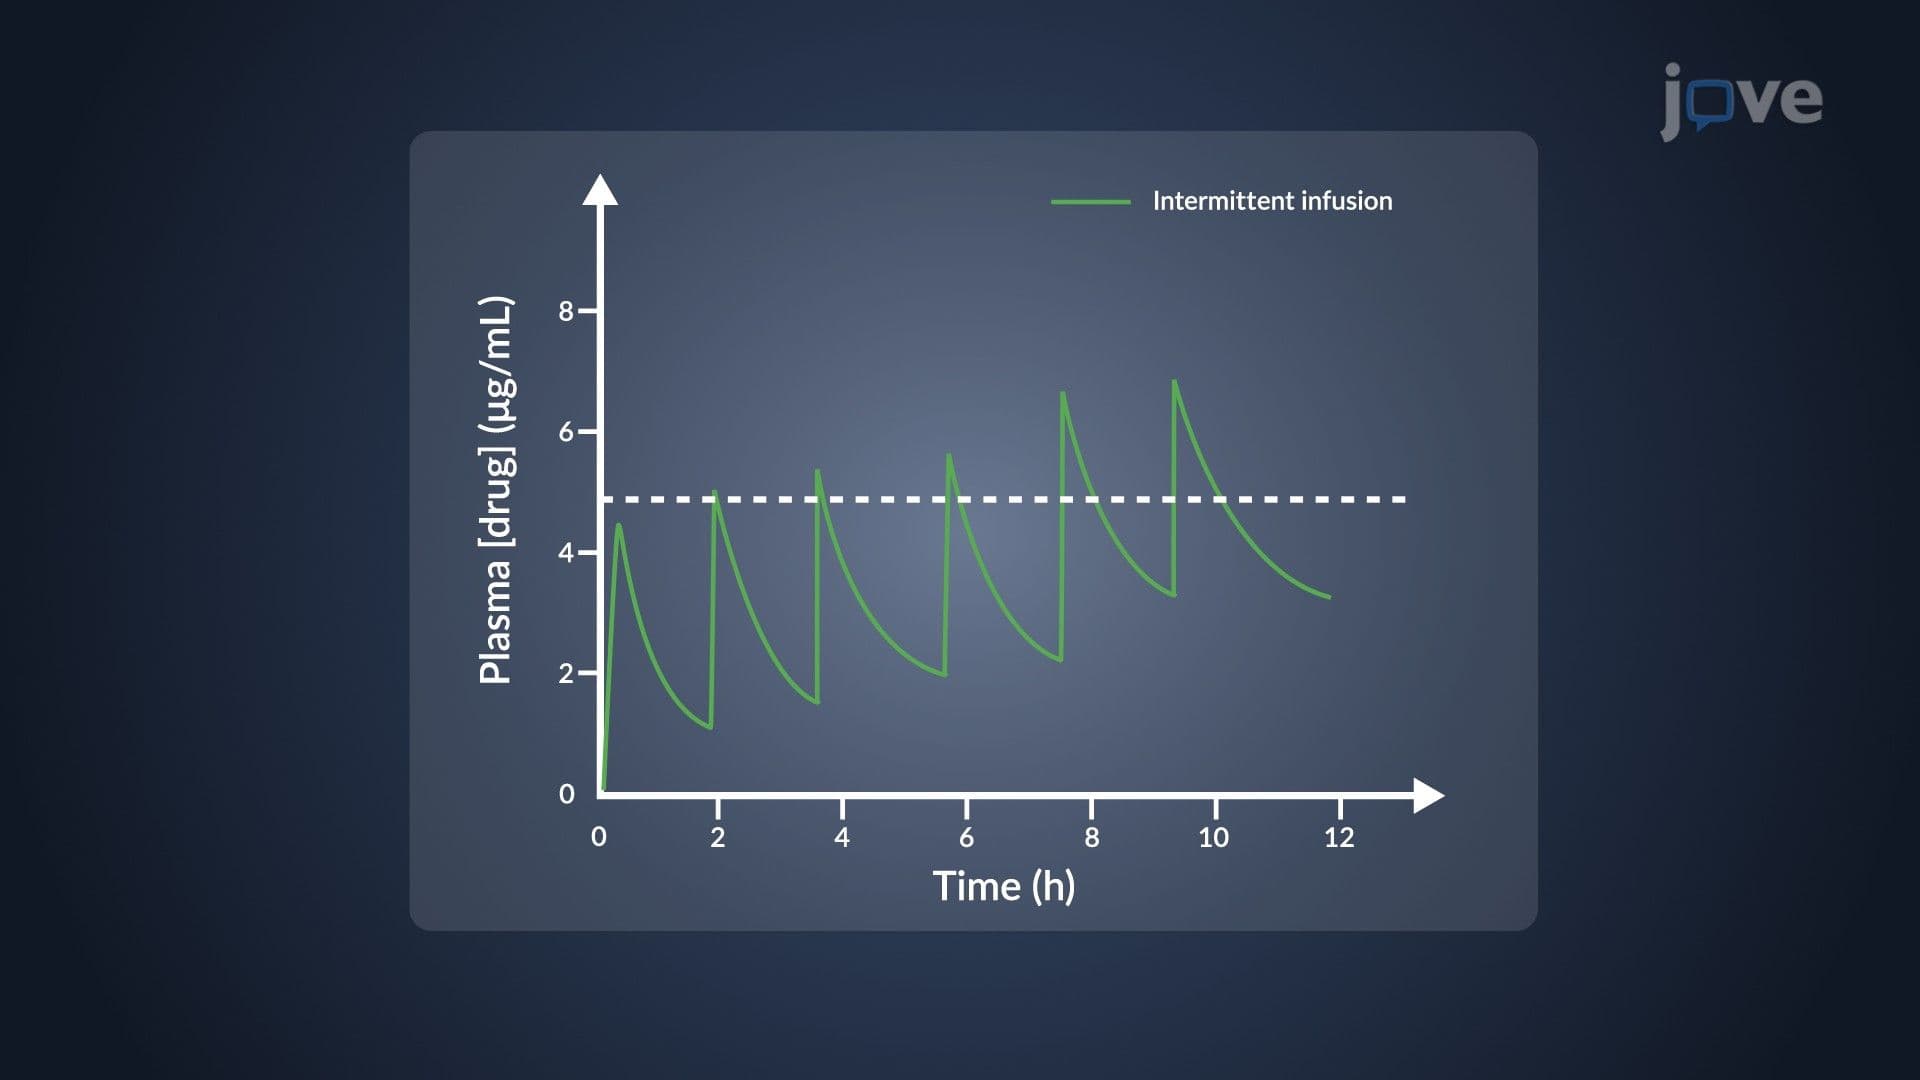
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:19
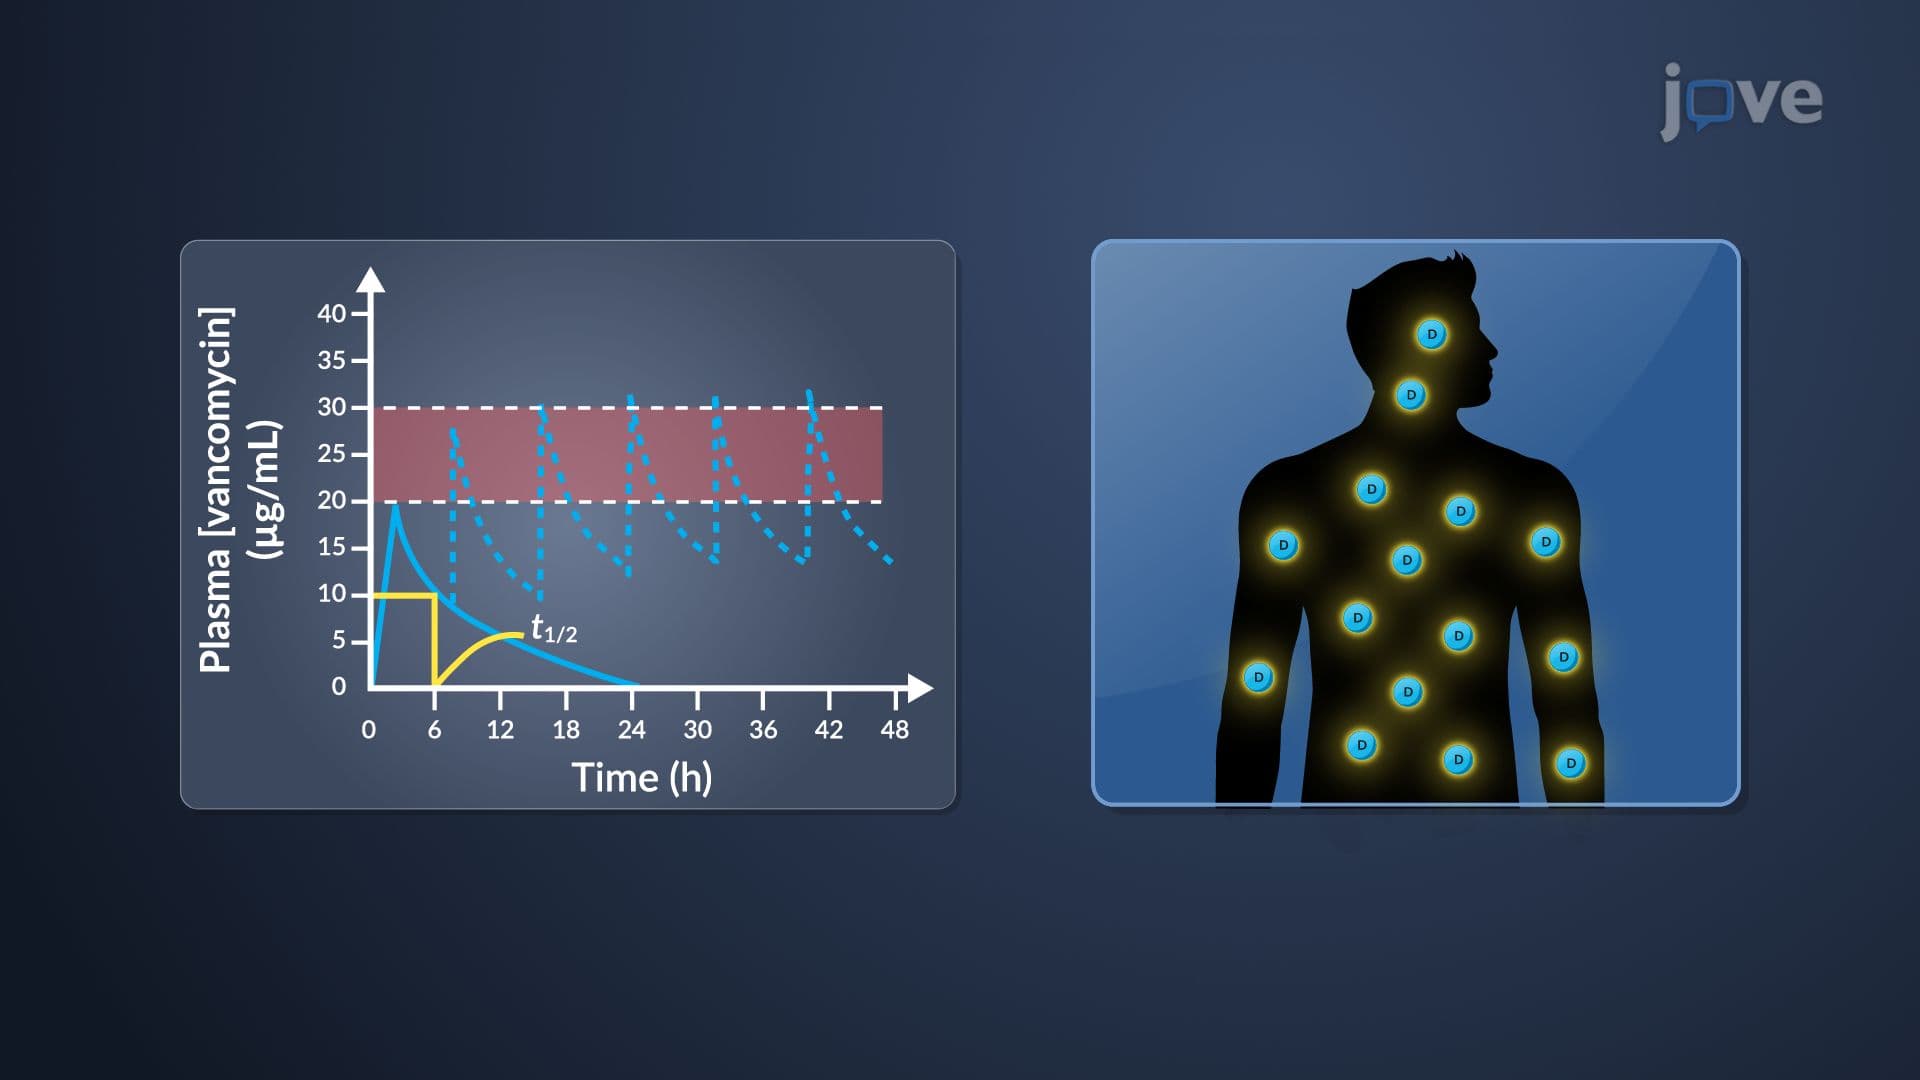
Dosage Interval and Administration Route: Determination Methods
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:15
Drug Dosing: Geriatric Patients
 01:22
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Absorption
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion