Related Experiment Video
Updated: Oct 11, 2026
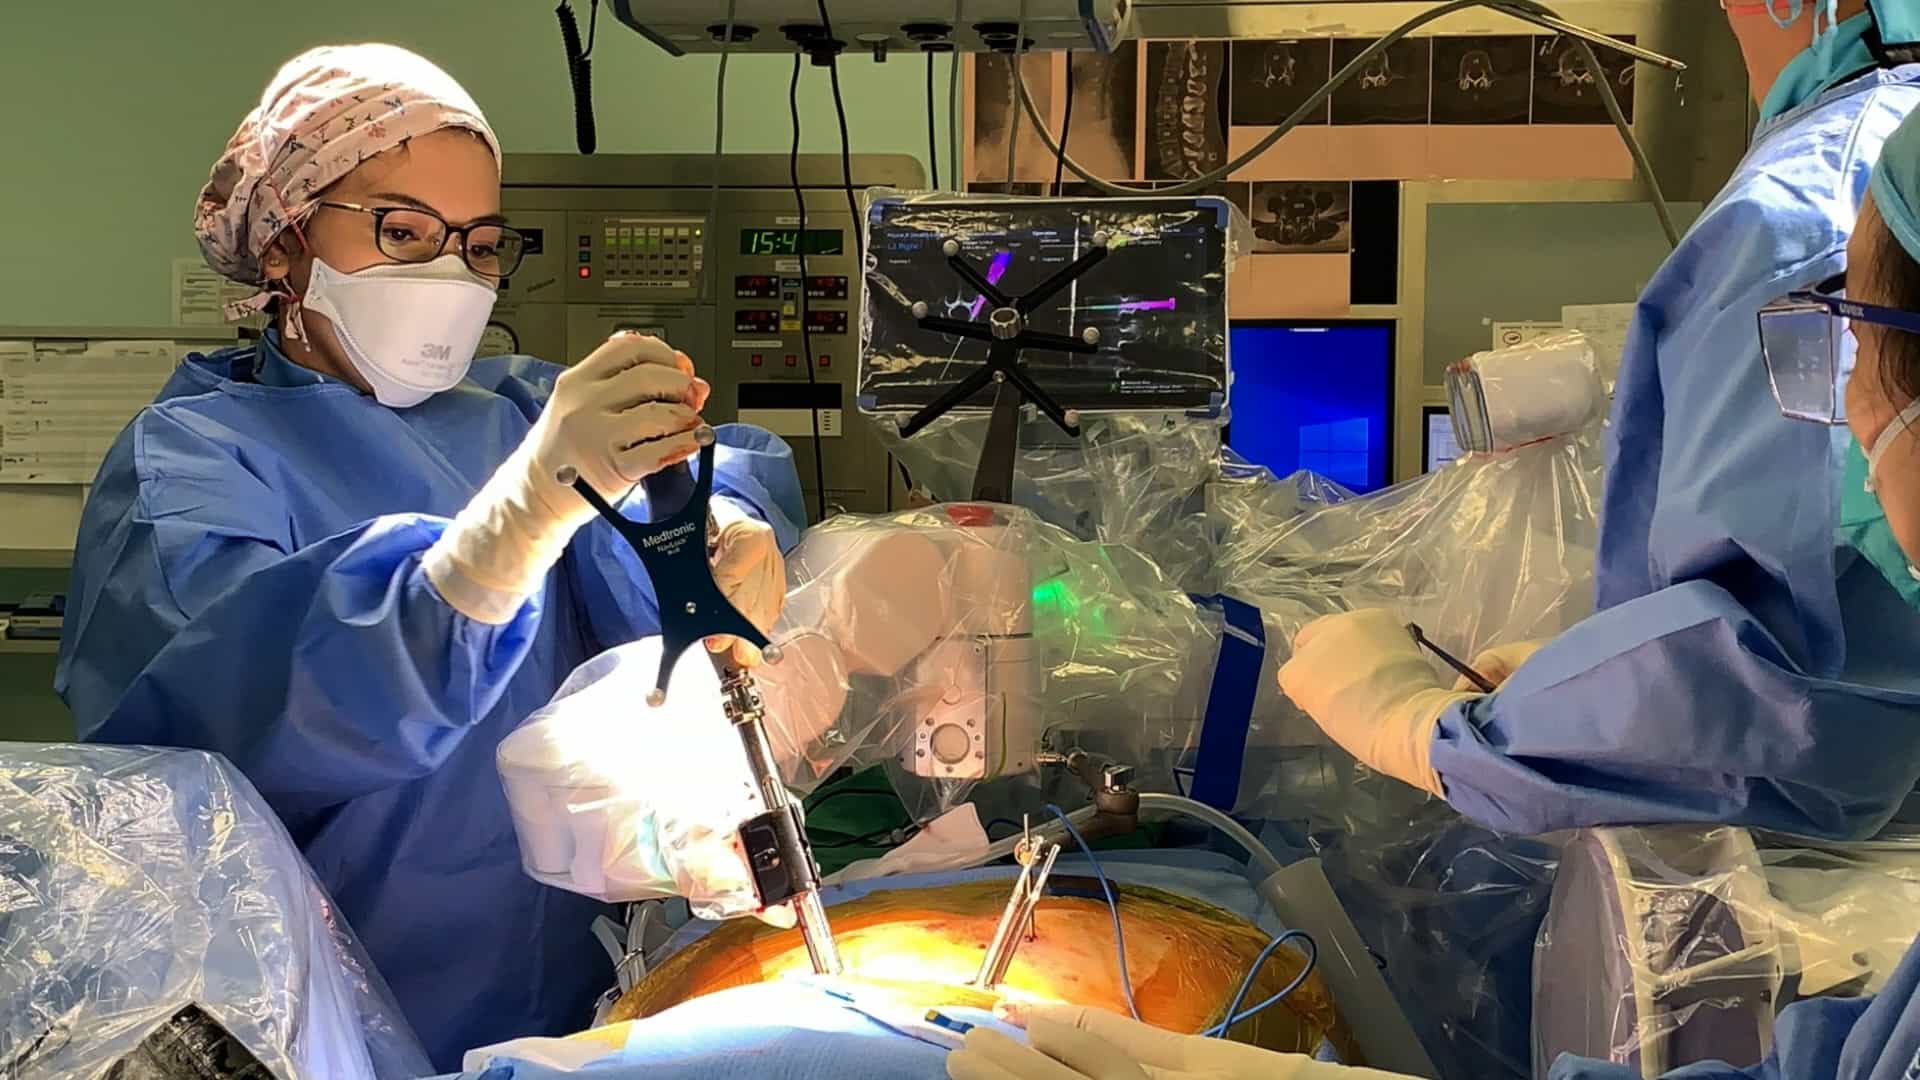

Multilevel Oblique Lumbar Interbody Fusion in Degenerative Lumbar Disc Disease with Instability
Published on: July 25, 2025
Hypermobile cervical disc arthroplasty: clinical and radiological outcomes at minimum 2-year follow-up
Tsung-Hsi Tu1,2, Yi-Hsuan Kuo1,2, Ching-Lan Wu2,3
11Department of Neurosurgery, Neurological Institute, Taipei Veterans General Hospital, Taipei City.

Objective:
Cervical disc arthroplasty (CDA) plays a pivotal role in preserving segmental motion at the index level to mitigate adjacent segment degeneration (ASD) and maintain neck mobility. The long-term results of US Investigational Device Exemption trials spanning a decade have consistently shown positive clinical outcomes and notable motion preservation. However, it remains uncertain whether patients with greater postoperative range of motion (ROM) experience different outcomes compared with those with normal ROM. The aim of this study was to evaluate whether postoperative hypermobility affects clinical outcomes and complication rates after CDA.
Methods:
A retrospective analysis of consecutive patients who underwent single-level CDA at C5-6 with ProDisc-C devices was conducted. Surgical indications included medically refractory cervical radiculopathy and/or myelopathy caused by degenerative disc disease or spondylosis. Patients were categorized based on postoperative segmental ROM as having hypermobility (ROM ≥ 15°) or normal mobility (ROM < 15°). Clinical outcomes were assessed using the visual analog scale (VAS) scores for neck and arm pain, Neck Disability Index (NDI), and modified Japanese Orthopaedic Association (mJOA) scale. Radiological outcomes included heterotopic ossification and ASD. The minimum follow-up was 24 months.
Results:
Of 114 patients (63 female, mean age 48 years) analyzed, 33 (28.9%) were classified as having hypermobility (mean postoperative ROM 17.8° ± 2.1°) and 81 (71.1%) as having normal mobility (mean ROM 9.3° ± 4.0°). The two groups were similar demographically, except for the slightly younger age in the hypermobility group (mean 45.1 ± 9.5 years vs 49.5 ± 10.6 years, p = 0.045). Both groups demonstrated significant improvements in all clinical parameters postoperatively (p < 0.05 for the Nurick grade and mJOA, VAS neck, VAS arm, and NDI scores), with no statistically significant differences observed between groups at the final follow-up. Complication rates were similar, including heterotopic ossification (12.1% vs 19.6%, p = 0.331) and ASD (3.0% vs 12.3%, p = 0.127). No device dislodgement or implant failure occurred in either group.
Conclusions:
Postoperative segmental hypermobility following CDA did not compromise clinical outcomes or increase complication rates. The safety profile of hypermobile segments was comparable with that of discs with normal mobility, with no instances of device failure or dislodgement. These findings support the safety and efficacy of CDA regardless of postoperative ROM, suggesting that values above the typical range do not adversely affect outcomes. These results contribute to the growing body of evidence supporting the effectiveness and safety of CDA across a wide spectrum of postoperative segmental ROMs.
