Related Experiment Video
Updated: Oct 11, 2026
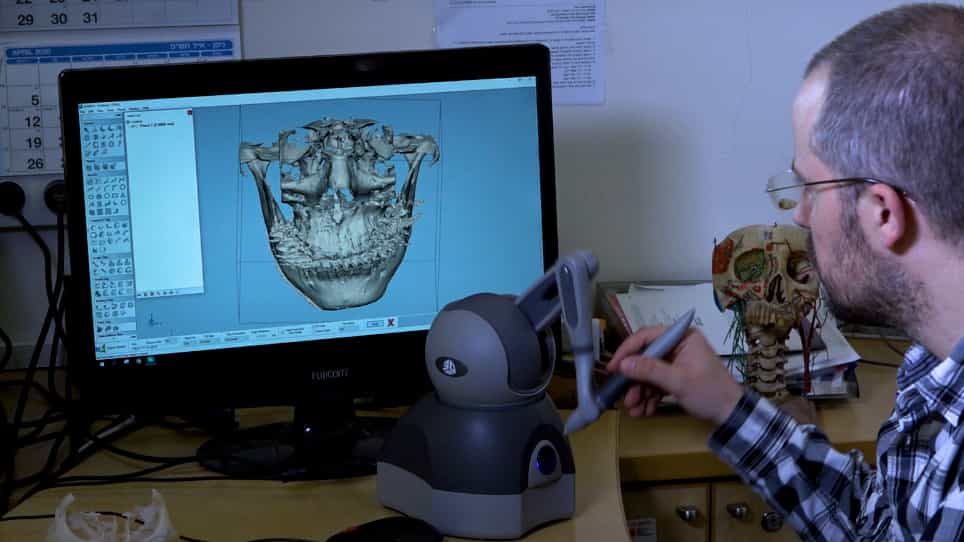

Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
A morphology-based model for treatment allocation in condylar head fractures
A Schmitz1, R Bahlinger1, C Rendenbach1
1Charité - Universitätsmedizin Berlin, Corporate Member of Freie Universität Berlin and Humboldt-Universität zu Berlin, Department of Oral and Maxillofacial Surgery, Augustenburger Platz 1, Berlin, 13353, Germany.

Abstract:
Condylar head fractures (CHFs) represent a heterogeneous injury spectrum, and indications for surgical versus conservative treatment remain inconsistently defined. Clinical decision-making is frequently based on qualitative morphological assessment rather than standardized criteria. This study aimed to develop and internally validate a morphology-based severity framework reflecting routine clinical treatment allocation patterns and to evaluate its ability to predict management strategies in CHFs. In this retrospective cohort study, all consecutive adult patients (≥18 years) with radiologically confirmed CHFs treated between 2018 and 2025 at a tertiary referral center were included. A morphology-based severity score integrating fracture displacement, vertical fragment contact, fragmentation, and trauma energy was defined a priori using three-dimensional imaging (CT or cone-beam CT), with double weighting applied to vertical fragment contact. Inter-rater reliability was assessed in a randomly selected blinded subset of 100 cases using weighted Cohen's kappa statistics and percentage agreement. The primary outcome was treatment allocation (conservative functional management with or without intermaxillary fixation versus operative treatment). Multivariable logistic regression and receiver operating characteristic analyses were performed, with internal validation using bootstrap resampling. Sensitivity analyses excluding trauma energy were additionally conducted. A total of 367 patients were included, of whom 219 (59.7%) were treated conservatively and 148 (40.3%) surgically. Increasing severity was independently associated with a higher likelihood of surgical treatment (OR 1.20 per point, 95% CI 1.10-1.33). The weighted severity model demonstrated acceptable discrimination (AUC 0.74; optimism-corrected AUC 0.73). Inter-rater agreement was 62% for fracture displacement, 83% for vertical fragment contact, and 68% for fragmentation, corresponding to moderate agreement for displacement and fragmentation and substantial agreement for vertical fragment contact. Sensitivity analyses excluding trauma energy demonstrated comparable model performance. The proposed morphology-based severity framework reflects local treatment allocation patterns within a tertiary referral center and may help standardize the description of locally observed fracture-morphology-based allocation patterns. External multicentre validation incorporating functional patient outcomes is required before broader clinical or inter-institutional use can be considered.

