Related Experiment Video
Updated: Oct 11, 2026


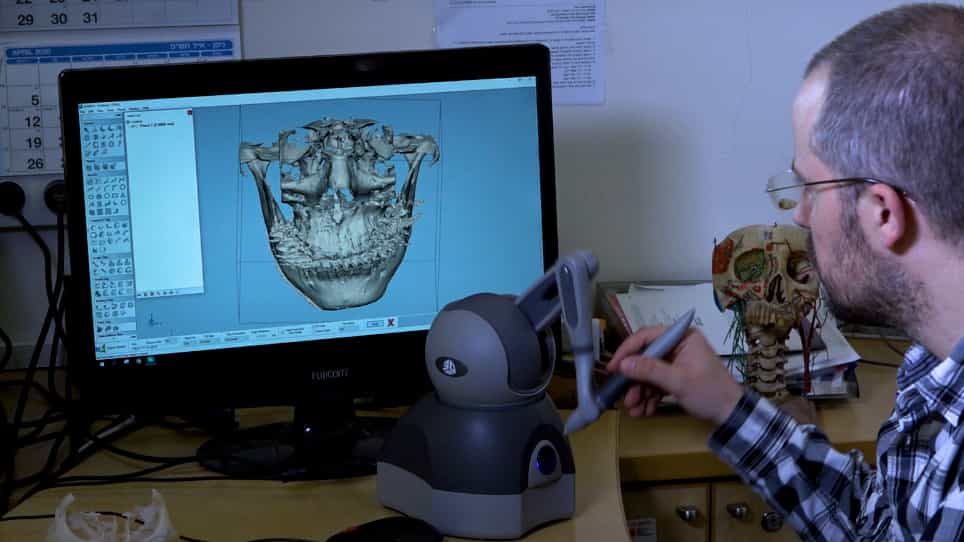
Digital Hybrid Model Preparation for Virtual Planning of Reconstructive Dentoalveolar Surgical Procedures
Published on: August 5, 2021
ACCURACY OF HARD TISSUE PREDICTIONS IN MONO- AND BIMAXILLARY ORTHOGNATHIC SURGERY USING 3D VIRTUAL SURGICAL PLANNING
Sacha André Decho1, Konrad Tolksdorf1, Christoph-Ludwig Hennig2
1Department of Oral and Cranio-Maxillofacial-Surgery/Plastic Surgery, Jena University Hospital, Friedrich Schiller University of Jena, Jena, Germany.

Background:
Three-dimensional virtual planning is an established method in orthognathic surgery. While numerous studies support its accuracy and precision, considerable variability in its extent has been reported.
Aim Of The Study:
This study assessed whether postoperative cephalometric outcomes corresponded to planned values within predefined clinically acceptable limits.
Material And Methods:
This retrospective cohort study included 53 patients with dentofacial deformities who underwent bilateral sagittal split osteotomy with (n=29) or without Le Fort I osteotomy (n=24). The dataset comprised preoperative computed tomography scans of the skull and pre- and postoperative lateral cephalometric radiographs. Initially, two- and three-dimensional preoperative cephalometric analyses were compared to quantify measurement errors. Subsequently, angular parameters planned during three-dimensional virtual surgical planning were compared with those obtained postoperatively via two-dimensional cephalometric analysis. Equivalence was assessed using predefined clinical limits of ±2° with two one-sided tests.
Results:
Preoperatively, no statistically significant angular deviations between 2D and 3D cephalometry were identified (p>0.05). Postoperatively, five out of seven angular parameters met the criterion for equivalence, with mean deviations within ±2°. For MnP-NS and MxP-MnP, mean deviations exceeding 2° were shown (2.054 and 2.015, respectively).
Conclusion:
Virtual surgery planning demonstrated clinically acceptable accuracy for maxillary positioning in midsagittal plane. However, mandibular vertical repositioning did not meet predefined equivalence criteria in the selected angular parameters. For unbiased postoperative evaluation of mandibular positioning, lateral cephalometric radiographs should be obtained after resolution of early confounding factors and represent a cost-effective, low-radiation alternative to three-dimensional imaging for sagittal and vertical assessment.