Related Experiment Video
Updated: Oct 11, 2026

Single-Port Robotic-assisted Transaxillary Breast-conserving Surgery: A Prospective, Single-arm, Non-randomized Phase IIa Clinical Trial
Published on: August 19, 2025
Dual-time-point ICGA for perfusion-guided transaxillary single-port endoscopic gynecomastia surgery: a prospective
Chao Wang1, He Jiang1, Xiaoyue Zhang1
1Department of Breast Surgery, The Second Affiliated Hospital of Shandong First Medical University, Tai'an, 271000, Shandong, China.

Background:
This study evaluated a standardized dual-time-point indocyanine green fluorescence angiography (ICGA) protocol in transaxillary single-port endoscopic surgery for gynecomastia, focusing on early perfusion-related outcomes, perioperative recovery, and patient-reported outcomes.
Methods:
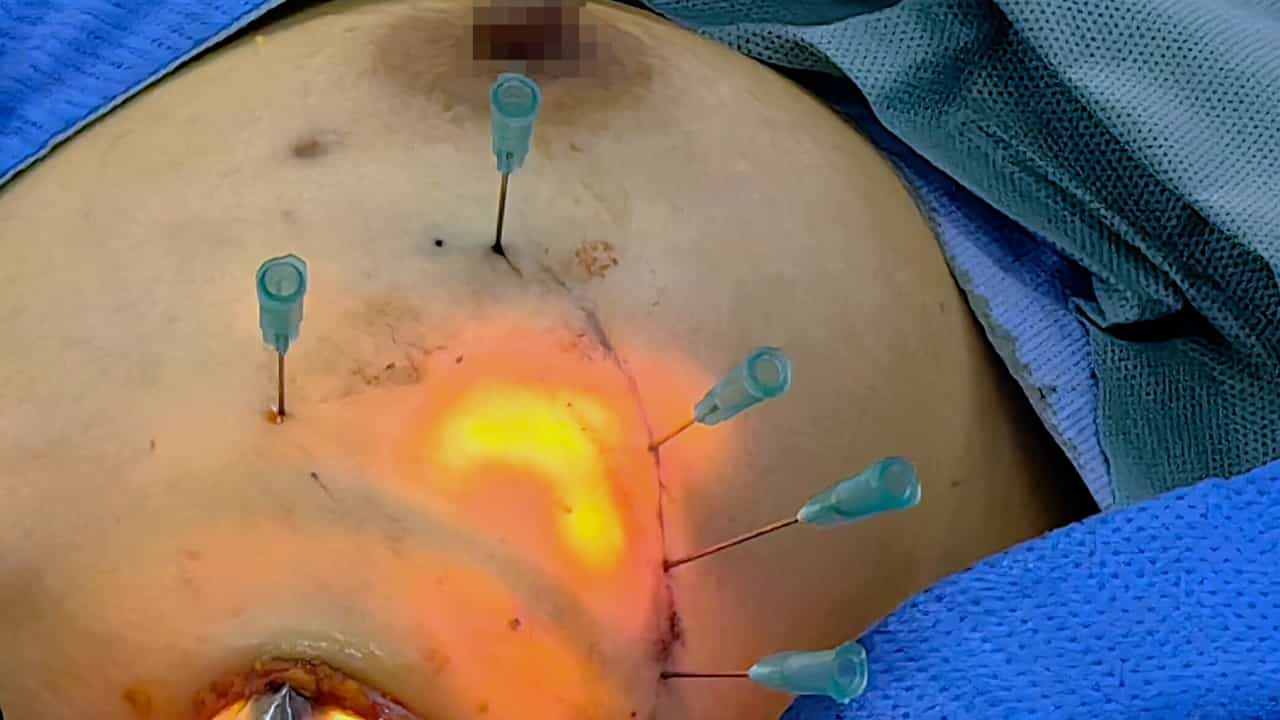
This prospective exploratory comparative cohort study included 88 men undergoing transaxillary single-port endoscopic subcutaneous glandular excision. Forty-three patients received ICGA and 45 did not. In the ICGA group, perfusion was assessed after deep dissection from the pectoralis major fascia and again after skin closure before compression dressing. Perfusion grading guided intraoperative adjustment and postoperative risk-stratified management. The primary outcome was a perfusion-related composite endpoint within 14 postoperative days. Secondary outcomes included perioperative variables, early complications, nipple sensation change, and 6-month BODY-Q scores. An exploratory observation point analysis assessed the association between second ICGA relative perfusion value (RPV) and postoperative day 14 local tissue changes.
Results:
The primary endpoint occurred in 3 of 43 patients (7.0%) in the ICGA group and 12 of 45 patients (26.7%) in the non-ICGA group, corresponding to an absolute risk difference of - 19.7 percentage points (95% confidence interval, - 34.8 to - 3.9) and an odds ratio of 0.21 (95% confidence interval, 0.05 to 0.79; P = 0.022). Perioperative recovery variables did not differ significantly. At 6 months, adjusted satisfaction with chest and nipples was higher in the ICGA group, whereas scar appraisal and psychological function showed no clear between-group differences. Lower second ICGA RPV was associated with postoperative day 14 local residual risk tissue changes, with 26.0% identified as an exploratory warning threshold.
Conclusions:
A standardized dual-time-point ICGA protocol was feasible and was associated with fewer early perfusion-related tissue changes without evident perioperative burden. The 26% RPV value remains an exploratory warning signal requiring external validation.