Related Experiment Video
Updated: Oct 11, 2026


Mouse Model of Surgical Uterine Injury and Subsequent Pregnancy Outcomes
Published on: June 27, 2025
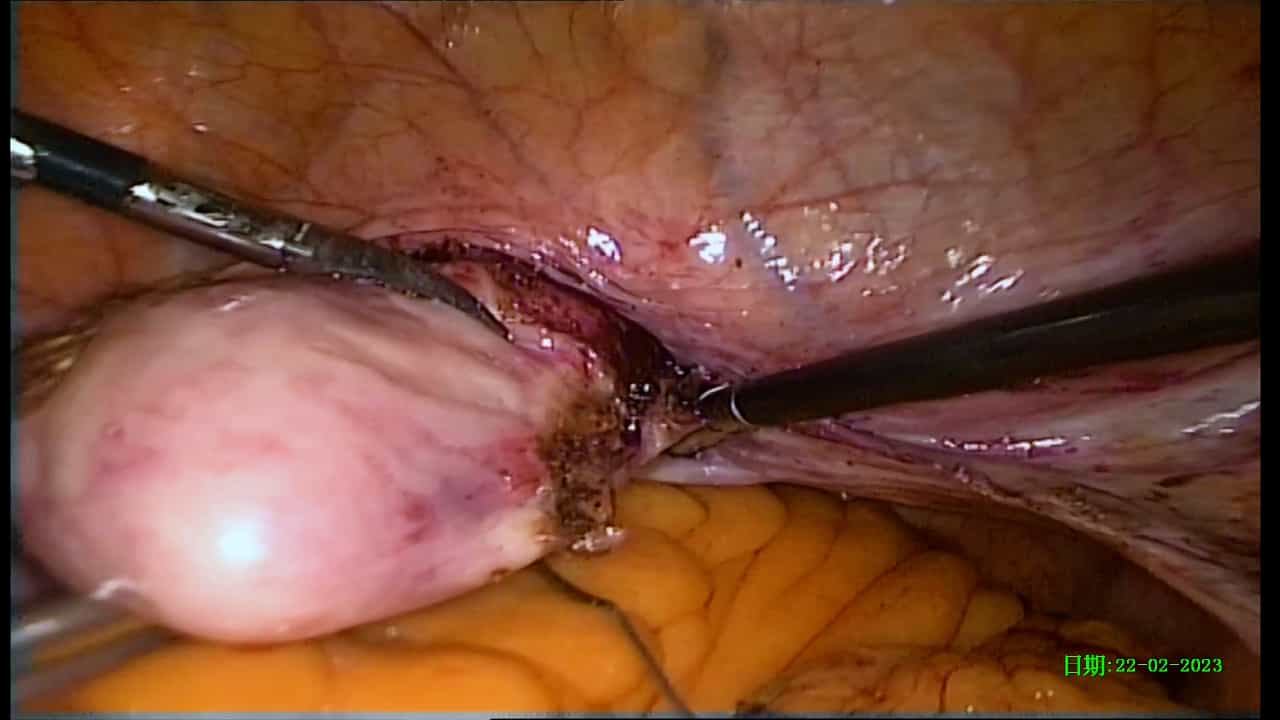
Beyond Hysterectomy: A Five-Year Single-Center Experience With Uterine-Sparing Surgery for Clinically Diagnosed
Emine Ergin Dogu1, Esra Ayanoglu1, Cevdet Dogu1
1Department of Obstetrics and Gynecology, University of Health Sciences Turkey, Sancaktepe Sehit Prof. Dr. Ilhan Varank Training and Research Hospital, Istanbul, Turkey.

Aim:
To describe surgical management and maternal outcomes in placenta accreta spectrum, emphasizing initial uterine-sparing management, secondary intervention, and final uterine preservation.
Methods:
This retrospective cohort included 21 patients managed at a tertiary center between June 2018 and August 2023. Clinical severity was classified exclusively from documented intraoperative findings using the International Federation of Gynecology and Obstetrics clinical classification; histopathological findings were evaluated separately. Management strategies, transfusion requirements, maternal morbidity, secondary interventions, and final uterine status were summarized descriptively. Patients with placental retention in situ were reviewed individually.
Results:
Initial management comprised segmental resection in seven patients, placental-bed hemostatic suturing in six, placental retention in situ in five, and cesarean hysterectomy in three. Uterine-sparing management was undertaken in 18 patients (85.7%). Red blood cell transfusion was administered to 18 patients (85.7%); seven (33.3%) received at least four units, and five (23.8%) required intensive care. Seven patients underwent a secondary intervention. All five patients with placental retention in situ underwent a secondary procedure on postoperative Days 5-68, including three planned relaparotomies; none subsequently underwent hysterectomy. Final uterine preservation was documented in 18 patients (85.7%), and no maternal deaths occurred.
Conclusions:
Uterine-sparing management was followed by final uterine preservation in most patients but was accompanied by substantial transfusion requirements and frequent secondary interventions. Placental retention in situ was followed by further procedures in all five patients. Initial avoidance of hysterectomy and final uterine preservation should be reported separately.