Single-Incision Plus One Robot-Assisted Abdominoperineal Resection Using the Hugo RAS System Through a Planned Stoma Site: A Novel Reduced-Port Robotic Surgery
Related Experiment Video
Updated: Oct 13, 2026
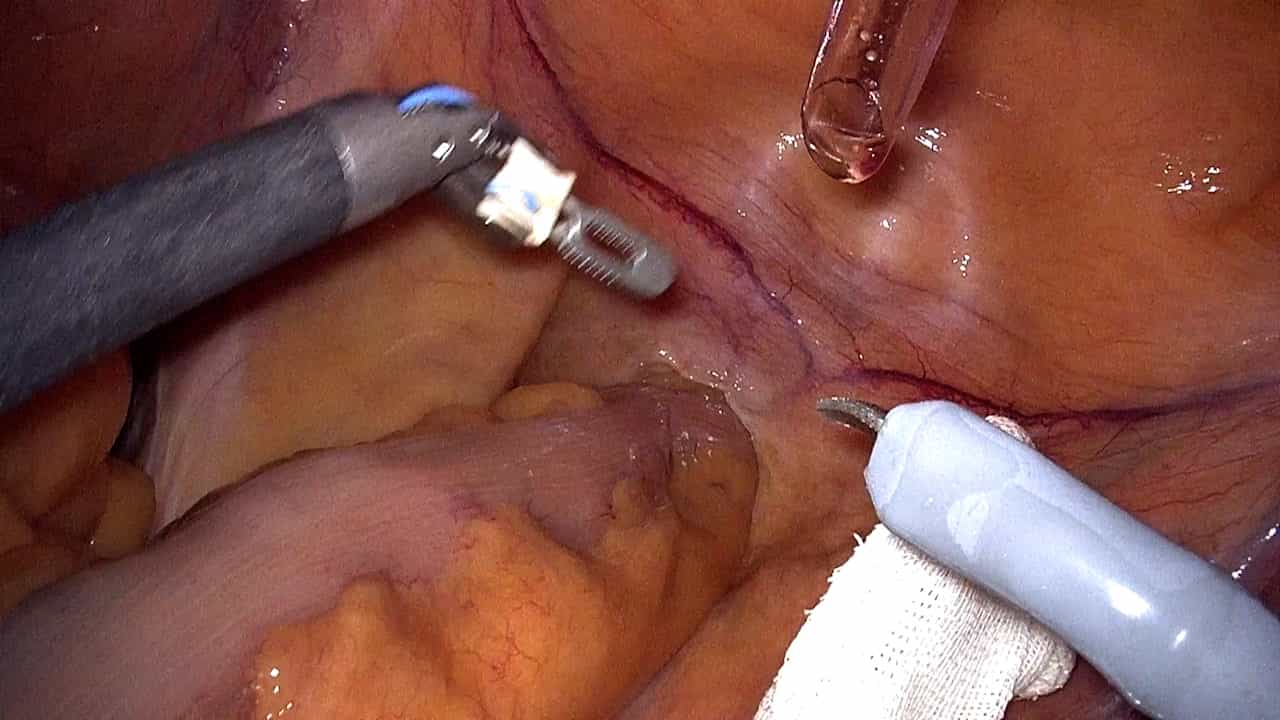
Surgical Robot-Assisted Transanal Specimen Extraction Radical Sigmoidectomy Without an Auxiliary Abdominal Incision
Published on: June 13, 2025
Shotaro Matsuda1, Yoshiro Itatani2, Masahiro Maeda1
1Department of Surgery, Graduate School of Medicine, Kyoto University, Kyoto, Japan.

Background:
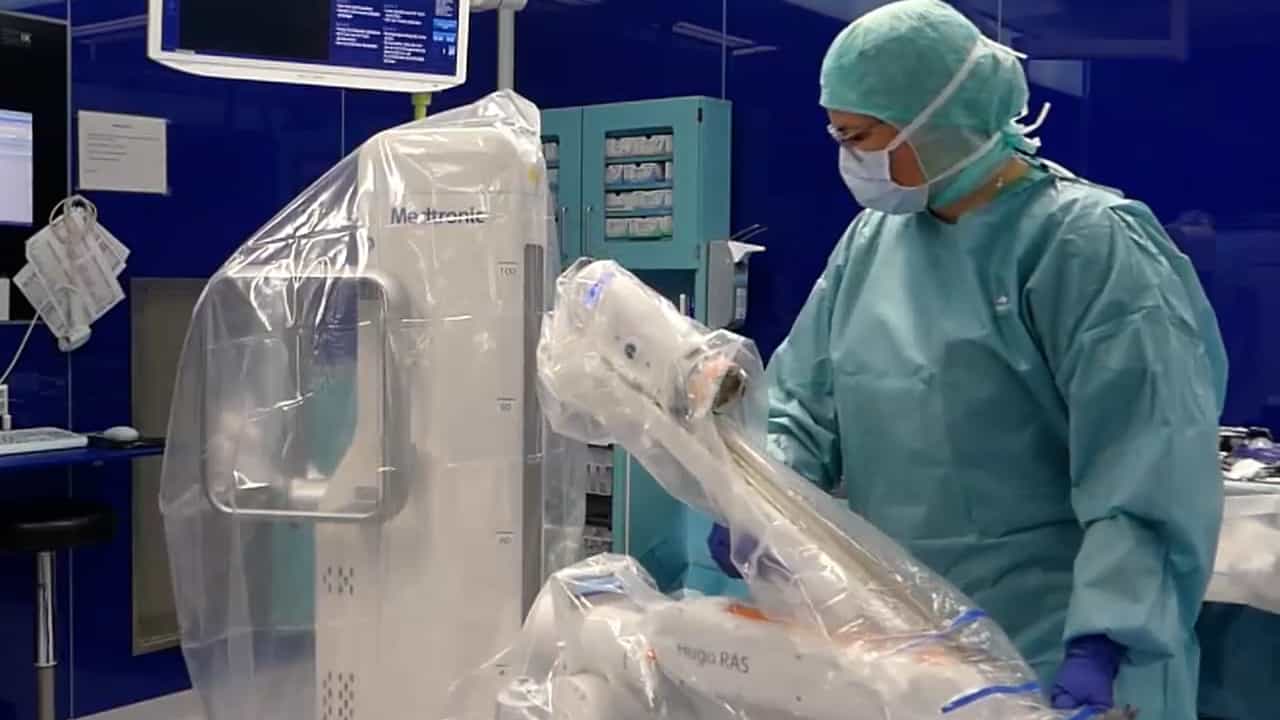
Reduced-port surgery has been developed to minimize abdominal wall trauma while maintaining the benefits of minimally invasive surgery. However, reduced-port robotic rectal surgery remains technically challenging due to interference of external arms. The modular design of the Hugo RAS system (Medtronic, Minneapolis, MN, USA) provides greater flexibility in arm positioning to minimize external arm interference without compromising instrument maneuverability1-4.
Methods:
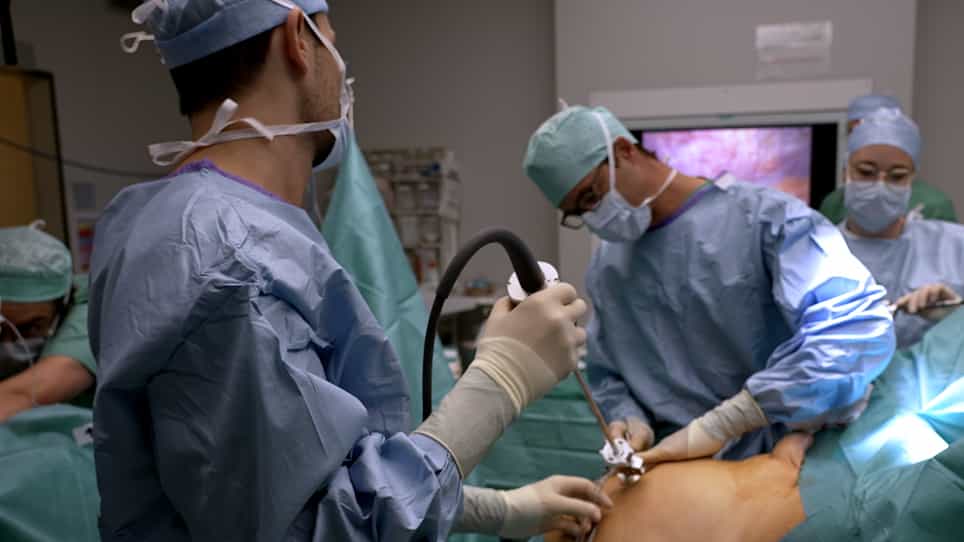
In abdominoperineal resection (APR), the incision for a permanent colostomy is inevitable. We report the first case of completely robot-assisted APR performed using the Hugo RAS system through a planned stoma site. Three robotic trocars were inserted through the planned left lower-quadrant stoma site, and one arm through the right lower quadrant. We call this approach SIPORS, Single-Incision Plus One Robot-assisted Surgery. The procedure is presented in the accompanying video.
Results:
As the first case, a 50-year-old woman with rectal cancer underwent APR after systemic chemotherapy. The console time was 167 min. The procedure was completed without significant robotic arm interference. The postoperative course was uneventful except for transient cystitis. The circumferential and distal resection margins were 3 and 35 mm, respectively. The mesorectal specimen was complete, 25 lymph nodes were harvested, and the pathological stage was pT3N2bM1.
Conclusions:
SIPORS using the Hugo RAS at a planned stoma site was technically feasible and achieved an oncologically acceptable resection in this patient. It may offer improved cosmesis, reduced postoperative pain, fewer wound complications, and a lower risk of trocar-site incisional hernia. Further experience is needed to confirm its reproducibility and clinical benefits.