Related Experiment Video
Updated: Oct 13, 2026

Chronic Thromboembolic Pulmonary Hypertension and Assessment of Right Ventricular Function in the Piglet
Published on: November 4, 2015
Hydatid pulmonary arterial embolization from an intracardiac cyst mimicking pulmonary thromboembolism: A case report
Abdulhay Tannari1, Mohamad Alrajab2, Wael Mahmood3
1Department of Internal Medicine, Pulmonology Division, Idlib University Hospital, Idlib, Syria.

Background:
Cystic echinococcosis most commonly affects the liver and lungs. Cardiac involvement is uncommon, and embolization to the pulmonary arteries is exceptionally rare. Such presentations may closely mimic pulmonary embolism, leading to diagnostic delay.
Case Presentation:
A 14-year-old boy from an endemic rural region presented with progressive dyspnea, intermittent chest pain, recurrent hemoptysis, and severe resting hypoxemia, with an oxygen saturation of 85% on room air. CT pulmonary angiography demonstrated extensive bilateral pulmonary arterial filling defects with cystic morphology, associated arterial dilatation, and representative attenuation values of approximately -5 HU. Despite the extensive vascular obstruction, D-dimer was only mildly elevated at 0.83 mg/L FEU (reference range, 0-0.5 mg/L FEU), compared with 0.41 mg/L FEU during a clinically stable period. Transthoracic echocardiography identified an approximately 22 × 22 mm right-sided intracardiac cyst adjacent to the tricuspid valve, and Echinococcus IgG ELISA was positive at 32 U/L (positive threshold, >11 U/L). The patient underwent median sternotomy with cardiopulmonary bypass, intracardiac cyst excision, and bilateral pulmonary arteriotomy, with removal of 18 large pulmonary arterial cystic structures. Follow-up CT pulmonary angiography at 6 months demonstrated marked regression of the intravascular disease burden, with small residual distal lesions. However, repeat CT approximately 12 months after surgery demonstrated an approximately 15-20% visually estimated increase in bilateral pulmonary arterial cystic burden, with new proximal pulmonary arterial cystic lesions, consistent with interval radiological progression. This progression was documented after discontinuation of albendazole, although a causal relationship could not be established.
Conclusion:
Pulmonary arterial hydatid embolization should be considered when presumed pulmonary thromboembolism is accompanied by discordant laboratory and imaging findings, particularly in endemic regions. In this patient, extensive bilateral fluid-attenuation intravascular lesions, only mildly elevated D-dimer despite severe obstruction, and a concomitant intracardiac cyst supported a non-thrombotic embolic process. Combined surgical and antiparasitic treatment resulted in marked initial radiological improvement; however, subsequent progression of residual pulmonary arterial disease highlights the need for prolonged radiological surveillance and careful reassessment of the duration of antiparasitic therapy.
Related Concept Videos
 01:29
Pulmonary Embolism I: Introduction
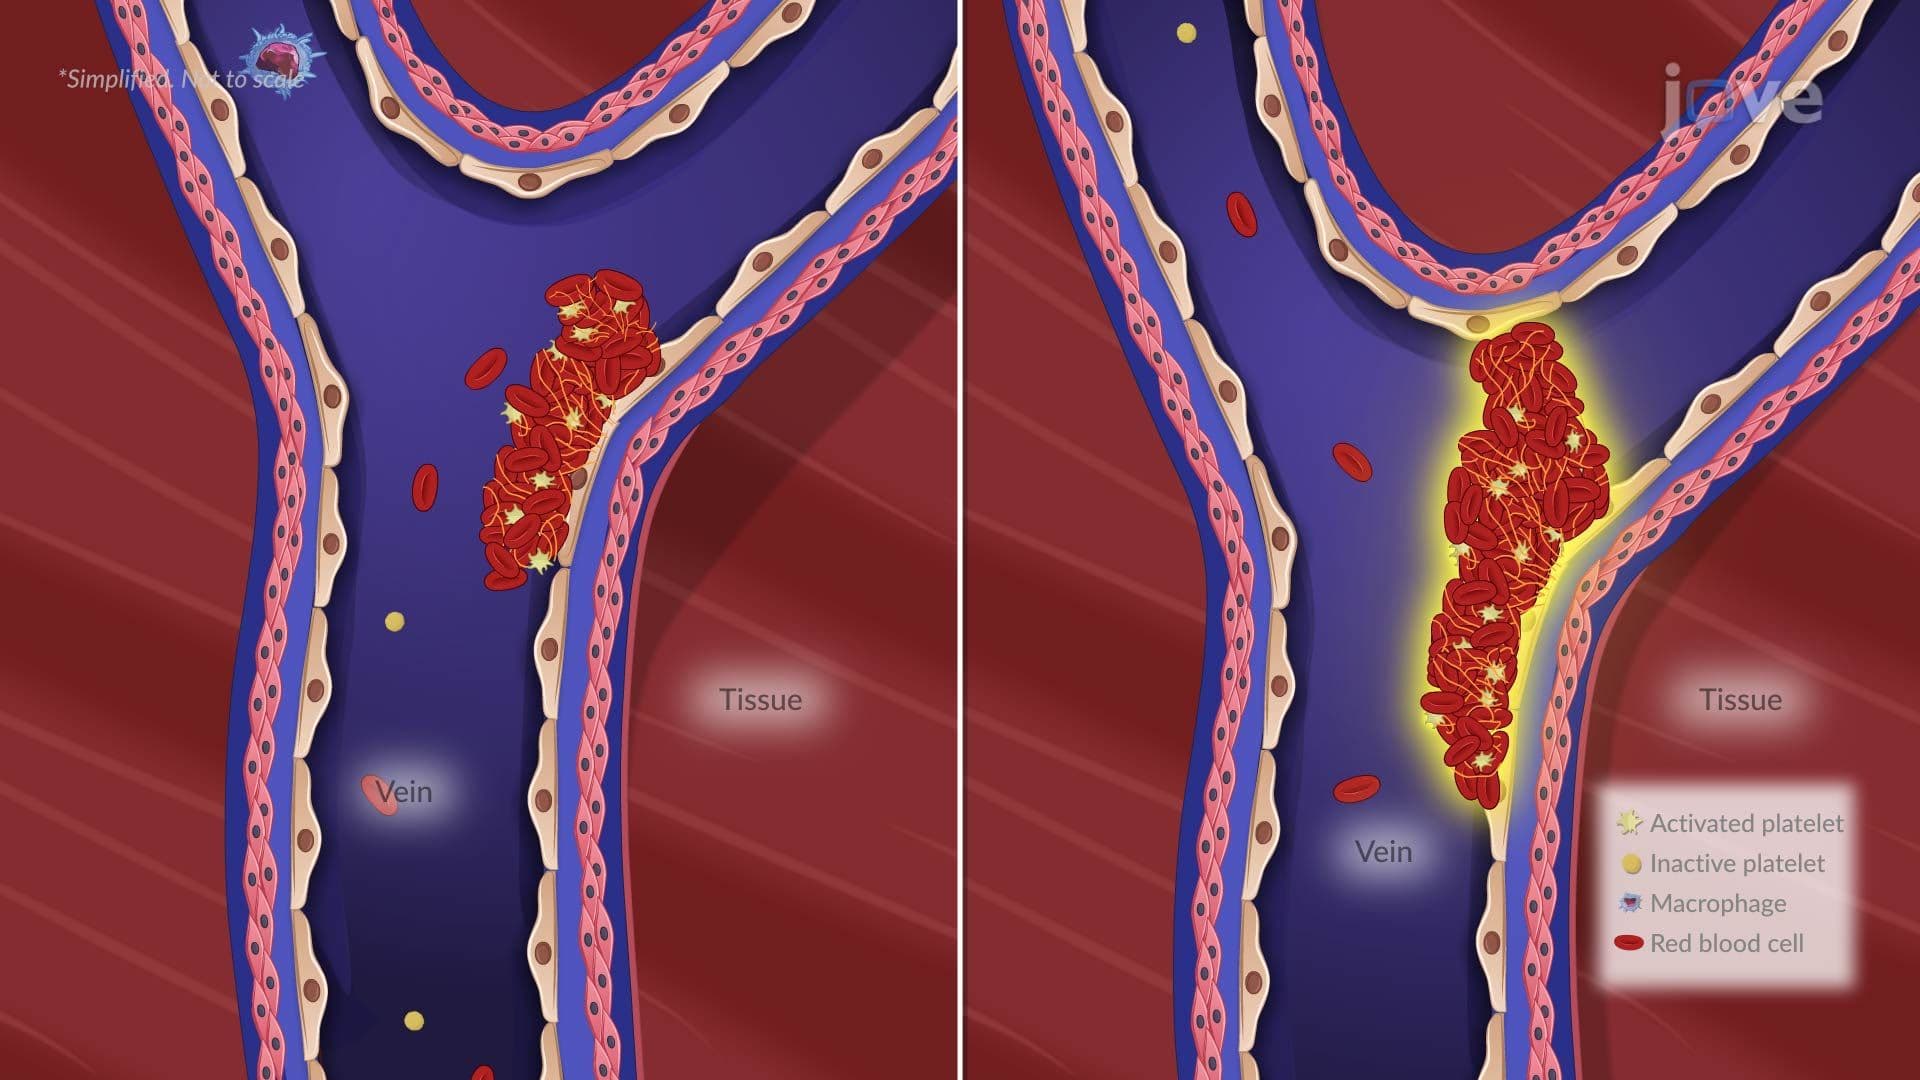 01:19
Pulmonary Embolism I: Introduction
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:27
Pulmonary Embolism III: Nursing Management
 01:21
Cardiac Catheterization II: Right Heart Catheterization
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy