Related Experiment Video
Updated: Oct 13, 2026
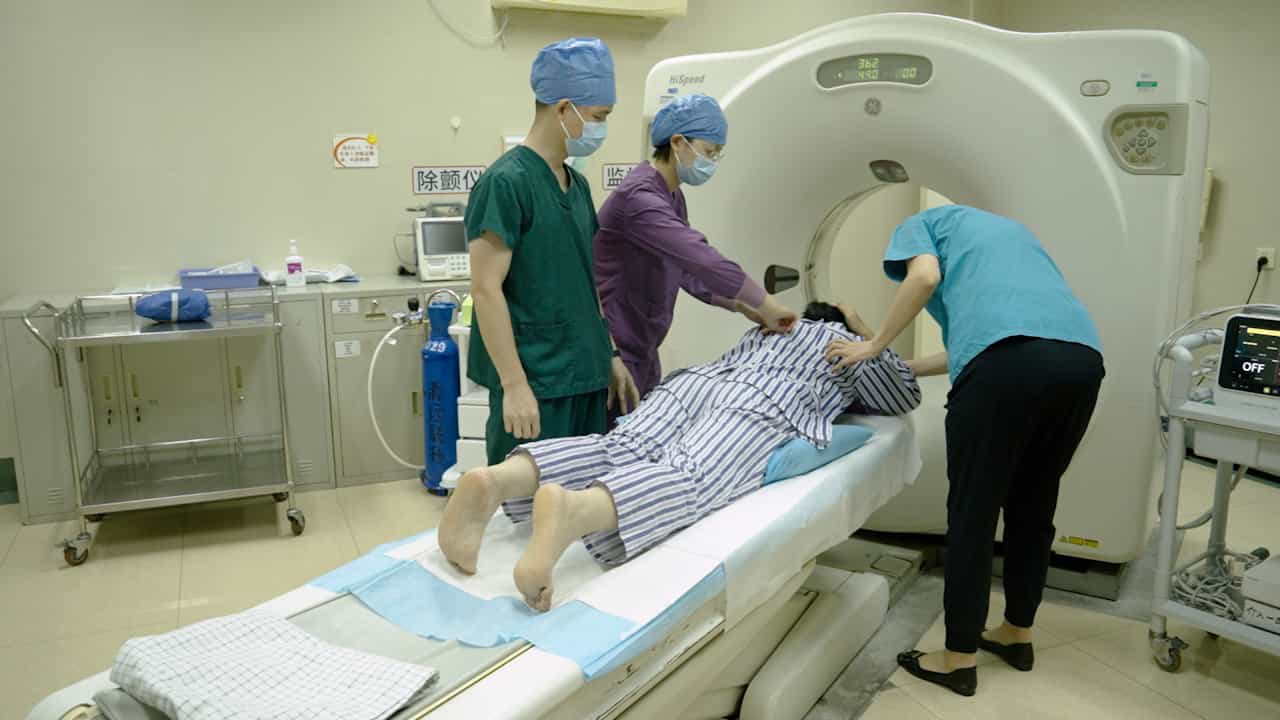

Improved Home Blood Pressure Control by CT-guided Ozone-mediated Renal Denervation for Patients with Resistant Hypertension
Published on: June 6, 2025
Debating targets for systolic blood pressure lowering in CKD
Evangelia Dounousi1, Panagiotis I Georgianos2, Rajiv Agarwal3
1Department of Nephrology, Faculty of Medicine, School of Health Sciences, University of Ioannina, Ioannina, Greece.

Abstract:
For several decades, there was no clinical-trial evidence to demonstrate that intensive blood pressure (BP)-lowering is a therapeutic strategy that prolongs survival and reduces the cardiorenal risk of patients with chronic kidney disease (CKD). In 2015, the landscape changed after the publication of the SPRINT (Systolic Blood Pressure Intervention Trial). Compared with a standard (<140 mmHg) systolic BP (SBP), an impressive cardiovascular and survival benefit was observed with an intensive (<120 mmHg) SBP target in non-diabetic patients with hypertension and high cardiovascular risk provoking premature termination of SPRINT. In 2017, a prespecified subgroup analysis of SPRINT showed that the benefit of intensive BP-lowering was similar in patients with or without CKD. As expected, this landmark trial has substantially influenced the BP target recommendations from the guidelines released thereafter. In 2021, the KDIGO guideline made a breakthrough with the adoption of the intensive SBP target of SPRINT for the management of hypertension in CKD. However, other major medical panels, like ESC, ERA, NICE, ACC and AHA have been reluctant to follow the same approach and the optimal BP goal in CKD continues to be debated. In this article, we provide evidence defending and opposing the position that the SBP target in CKD should be <120 mmHg. We conclude with a consensus and suggestions for the successful implementation of this intensive SBP target in daily clinical practice.
Related Concept Videos
 01:18
Hypertension and Regulation of Blood Pressure
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:28
Hypertension IV: Drug Therapy and Lifestyle Modifications
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:28
Hypertension I: Introduction