Prospective results of locally delivered low-cost mesh inguinal hernia repair in a low resource setting
Anthony Abbot Kamara1,2, Foday Daddy Mansaray1, Daniel Lavalie1
1Partners in Health, Koidu Government Hospital, Kono District Sierra Leone, Koidu Town, Sierra Leone.

Purpose:
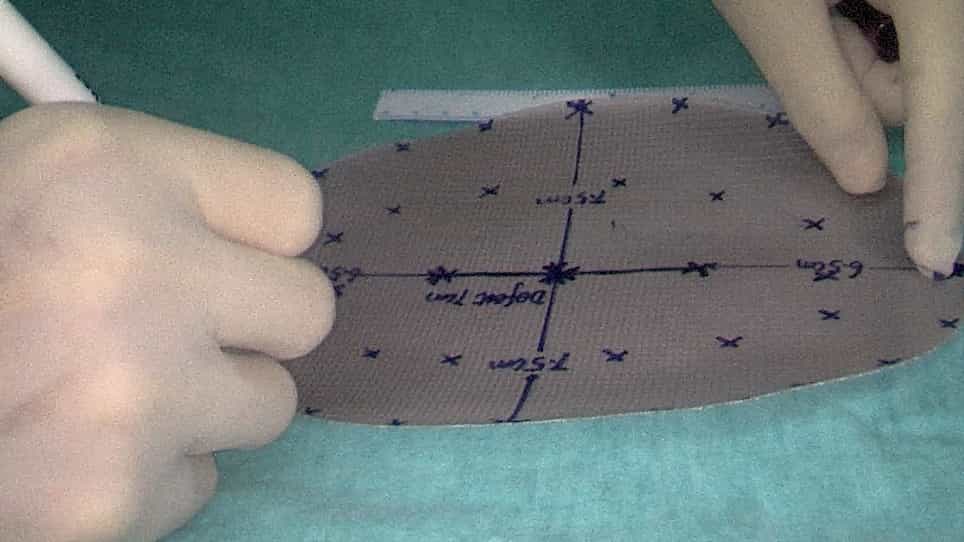
To assess patient outcomes after locally processed ultra-low-cost hernia mesh placement became routine practice in a government hospital in one of the world's poorest countries.
Methods:
Observational study with comprehensive prospective data collection via electronic registry from June 2023 to January 2026. Interrogation of database after 2.5 years assessed demographics, hernia types and complexity, short term complications and outcomes at 2 years.
Results:
Between 01.06.2023 and 01.06.2025, 121 inguinal hernia repairs were repaired with mesh. 76% of inguinal hernias were primary and 24% were recurrent or re-recurrent. No Surgical Site Infection was seen after primary inguinal hernia repair. A 10% superficial wound infection rate was seen after repair of recurrent and re-recurrent inguinal hernias. No mesh infections occurred. Heavy use of prophylactic antibiotics was observed but reduced during the study period. This is a report of the first two years of an on-going service and patients are at varying time points post-surgery. 108 repairs (89%) were > one year post-surgery and one-year FU is documented for 108 repairs (100%). No hernia recurrences identified to date 0% 95% CI [0, 3.35]. 66 repairs were > 2 years post-surgery and 2-year FU is documented for 58 repairs (88%). No hernia recurrences identified to date 0% (95% CL: 0%, 6.16%).
Conclusion:
Robust, prospective outcome monitoring is feasible in low-income-countries, even outside of the clinical trial situation. Structured training and local implementation have produced good early hernia outcomes.